Related Experiment Video
Updated: Apr 15, 2026
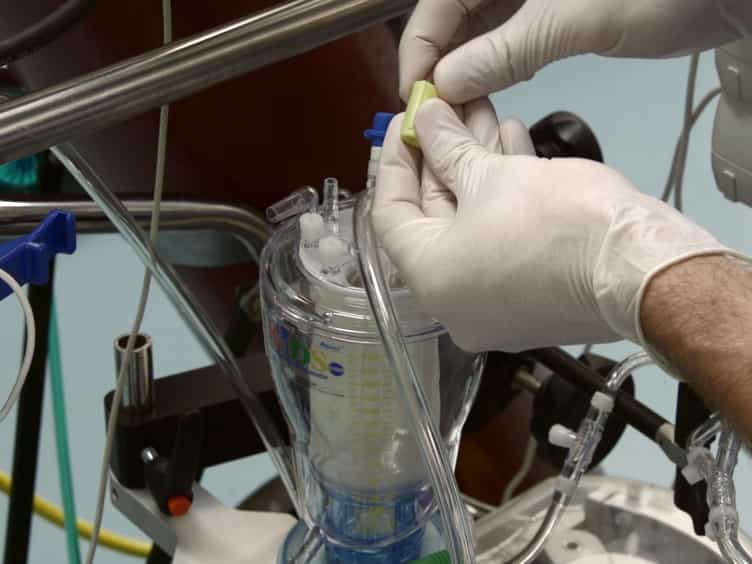
Normothermic Ex Vivo Kidney Perfusion for the Preservation of Kidney Grafts prior to Transplantation
Published on: July 15, 2015
Impact of Kidney Disease on Survival in Neonatal Extracorporeal Life Support
Aaron Wightman1, Miranda C Bradford, Jordan Symons
11Division of Nephrology, Department of Pediatrics, University of Wisconsin School of Medicine and Public Health, Madison, WI. 2Children's Core for Biomedical Statistics, Center for Clinical and Translational Research, Seattle Children's Research Institute, Seattle, WA. 3Division of Nephrology, Department of Pediatrics, University of Washington School of Medicine, Seattle, WA. 4Division of Nephrology, Seattle Children's Hospital, Seattle, WA. 5Division of Pediatric Critical Care, Department of Pediatrics, University of Washington School of Medicine, Seattle, WA. 6Division of Critical Care, Seattle Children's Hospital, Seattle, WA.

Objective:
To investigate the prevalence and survival to discharge of neonates with kidney disease who received extracorporeal life support.
Design:
We analyzed the Extracorporeal Life Support Organization international registry of neonates (< 30 d old) who received extracorporeal life support from 1989 to 2012. We used International Classification of Diseases and Related Health Problems, 9th Revision, Clinical Modification, codes to identify neonates with kidney disease at time of cannulation for extracorporeal life support.
Setting:
Participating Extracorporeal Life Support Organization centers.
Patients:
All neonates who received extracorporeal life support at an Extracorporeal Life Support Organization center from 1989 to 2012.
Interventions:
We performed bivariate logistic regression to estimate associations between survival and covariates. We used unadjusted and adjusted logistic regression to compare survival to discharge between neonates with and without kidney disease. Odds ratios were estimated separately for three groups based on extracorporeal life support indication: pulmonary indication without congenital diaphragmatic hernia, pulmonary indication with congenital diaphragmatic hernia, and cardiac indication. Adjusted models included covariates identified as significant in bivariate models for each group.
Measurements And Main Results:
The primary outcome measure was survival to discharge from hospitalization. Of the 28,755 neonates who received extracorporeal life support, 405 had kidney disease (extracorporeal life support indication: 210 pulmonary indication without congenital diaphragmatic hernia, 65 pulmonary indication with congenital diaphragmatic hernia, and 130 cardiac indication). Survival was lower in neonates with kidney disease than those without (49% vs 82% pulmonary indication without congenital diaphragmatic hernia, 25% vs 51% pulmonary indication with congenital diaphragmatic hernia, 21% vs 41% cardiac indication). Kidney disease was associated with reduced survival in adjusted models (95% CI for odds ratio 0.31-0.59 pulmonary indication without congenital diaphragmatic hernia, 0.27-0.89 pulmonary indication with congenital diaphragmatic hernia, 0.31-0.77 cardiac indication).
Conclusions:
Neonates with kidney disease who receive extracorporeal life support have poorer survival to discharge compared with other neonates who receive extracorporeal life support, suggesting that kidney disease should be considered when making extracorporeal life support initiation decisions.
Related Concept Videos
 01:22
Acute Kidney Injury I: Introduction
 01:29
Acute Kidney Injury II: Pathophysiology
 01:30
Acute Kidney Injury IV: Diagnostic Studies and Prevention
 01:28
Kidney Transplant I: Introduction
 01:29
Acute Kidney Injury III: Clinical Manifestations
 01:26
Extracorporeal Removal of Drugs: Continuous Renal Replacement Therapy