Related Experiment Video
Updated: Apr 15, 2026
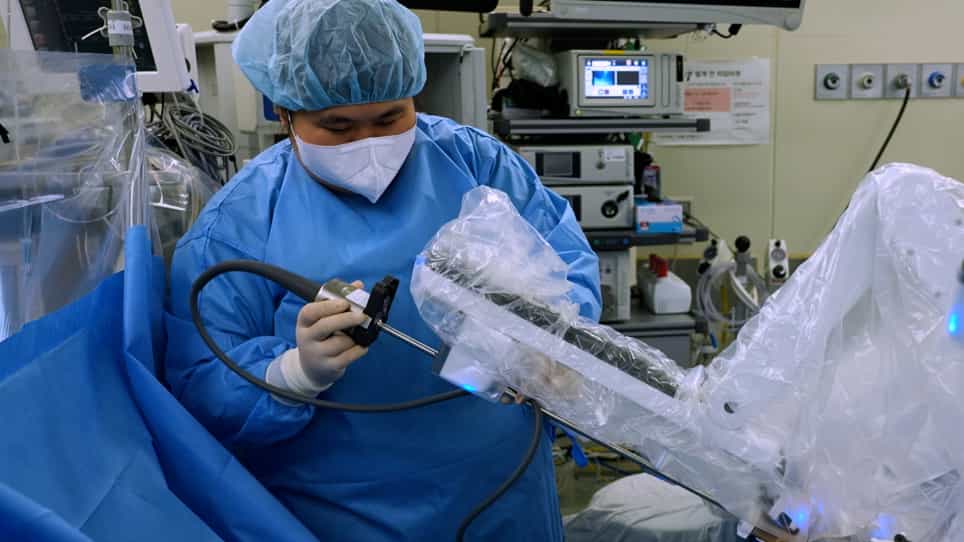

Robot-Assisted Kidney Transplantation
Published on: July 19, 2021
Objective pain assessment after ureteral reimplantation: comparison of open versus robotic approach
M Harel1, K W Herbst2, R Silvis2
1University of Connecticut Health Center, 263 Farmington Avenue, Farmington, CT, 06030, USA; Connecticut Children's Medical Center, 282 Washington Street, Hartford, CT, 06106, USA.

Insights
Robotic ureteral reimplantation in children showed lower narcotic use and less severe pain compared to open surgery. Further research with larger sample sizes is needed to confirm these findings.
Area of Science:
- Pediatric Surgery
- Urology
- Minimally Invasive Surgery
Background:
- Open ureteral reimplantation is standard for vesicoureteral reflux (VUR).
- Minimally invasive techniques may reduce pain and recovery time.
- Previous studies on pain comparison between open and minimally invasive surgery are inconclusive.
Purpose of the Study:
- To compare postoperative pain in children undergoing open versus robotic ureteral reimplantation.
- Utilized age-appropriate, validated pain assessment scales for accurate measurement.
Main Methods:
- Prospective cohort study of VUR surgery patients (July 2010-February 2013).
- Excluded patients receiving endoscopic treatment or caudal/epidural anesthesia.
- Assessed pain scores and narcotic doses on postoperative day 1.
Main Results:
- Robotic surgery (23 patients) showed lower narcotic requirements than open surgery (11 patients) (P < 0.05).
- No statistically significant difference in subjective pain scores (P = 0.12).
- Significantly higher percentage of robotic patients experienced mild/no pain (57%) vs. open (27%), and lower severe pain (9% vs. 45%).
Conclusions:
- Robotic ureteral reimplantation associated with reduced narcotic needs and lower perceived pain intensity.
- Validated pain scores and narcotic requirements offer a more accurate pain assessment than indirect measures.
- Larger sample sizes are required to strengthen statistical significance and subgroup analyses.
Introduction:
While open ureteral reimplantation is the gold standard of surgical intervention for vesicoureteral reflux (VUR), minimally invasive approaches offer the potential benefits of decreased postoperative pain, improved cosmesis, and shorter hospital stay and convalescence. Studies comparing open and minimally invasive surgery with respect to postoperative pain in children have been inconclusive.
Objective:
We sought to compare postoperative pain in children undergoing open versus robotic ureteral reimplantation by using age-appropriate, validated pain assessment scales.
Methods:
A prospective cohort of all patients enrolled in an Institutional Review Board-approved VUR surgery registry between July 2010 and February 2013 was analyzed. Patients who underwent endoscopic treatment or who received caudal or epidural anesthesia were excluded. Age-appropriate, validated pain scales ranging from 0 to 10 were utilized for pain assessment. Pain scores and narcotic doses administered on the first postoperative day were analyzed.
Results:
Of the 34 subjects included, 11 underwent open intravesical reimplantation, while 23 patients underwent robotic extravesical reimplantation. Table 1 displays patient characteristics and results of pain assessment. Robotic surgery was associated with lower narcotic requirement compared to open surgery (P < 0.05). The difference in pain scores between the two cohorts approached, but did not reach, statistical significance (P = 0.12). However, the percentage of patients with mild or no pain (57% robotic, 27% open) versus severe pain (9% robotic, 45% open) was notably different between the two cohorts.
Discussion:
Previous studies addressing the effect of surgical modality on pediatric postoperative pain are limited by their reliance on narcotic administration as an indirect surrogate for measuring pain. In the present study, postoperative pain was assessed with narcotic requirements and consistently collected validated pain scores, which more accurately reflect a patient's perceived pain. Although there was no significant difference in subjective pain scores between patients undergoing open versus robotic reimplantation, the percentage of patients with mild or no pain (57% robotic, 27% open) versus severe pain (9% robotic, 45% open) was notably different between the two cohorts. This study was limited by a lack of randomization as well as small sample size, which did not allow for age sub-group analysis or small differences to be statistically significant.
Conclusions:
In the present study, robotic ureteral reimplantation was associated with lower narcotic requirement compared to open surgery, and lower intensity of postoperative pain according to a direct pain assessment tool. Larger sample sizes are necessary to strengthen statistical comparisons.

Related Concept Videos
 01:26
Kidney Transplant II: Surgical Procedure
 01:28
Urologic Endoscopic Procedure: Cystoscopic Examination