Related Experiment Video
Updated: Apr 14, 2026
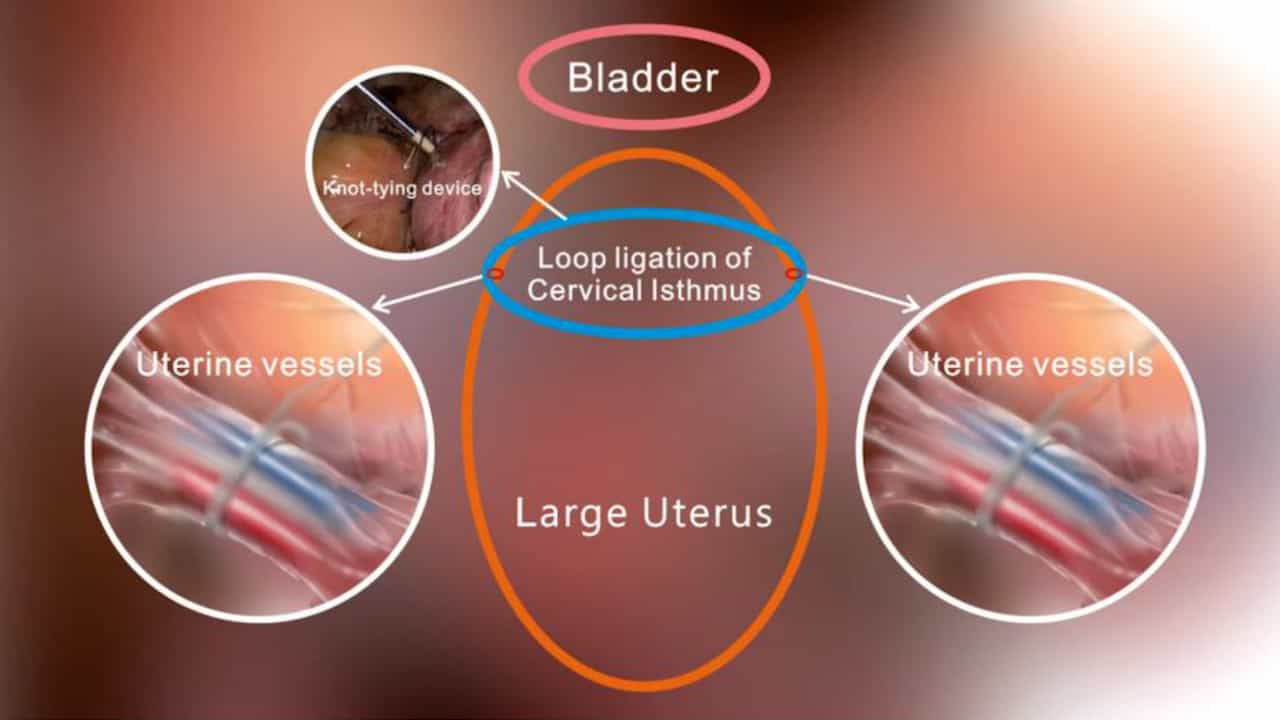

Laparoscopic Extracorporeal Knot-Tying for Uterine Vessel Occlusion during Hysterectomy with Cervical Cerclage in Large Uteri
Published on: September 12, 2025
Laparoscopic and vaginal approaches to hysterectomy in the obese
Giorgio Bogani1, Antonella Cromi1, Maurizio Serati1
1Department of Obstetrics and Gynecology, University of Insubria, Del Ponte Hospital, Varese, Italy.

Objective:
The aim of the study was to compare surgery-related outcomes between laparoscopic (LH) and vaginal (VH) hysterectomy, performed for benign uterine disease (other than pelvic organs prolapse) in obese women.
Study Design:
Data of consecutive obese (BMI≥30) patients undergoing LH and VH, between 2000 and 2013, were compared using a propensity-matched analysis. One hundred propensity-matched patient pairs (200 patients) undergoing LH (n=100) and VH (n=100) represented the study group.
Results:
Baseline demographic characteristics were similar between groups. Patients undergoing LH experienced similar operative time (87.5 (25-360) vs. 85 (25-240)min; p=0.28), slightly lower blood loss (100 (10-3200) vs. 150 (10-800)ml; p=0.006) and shorter length of hospital stay (1 (1-5) vs. 2 (1-5) days; p<0.001) than women undergoing VH. There was no statistically significant difference between LH and VH in complication rate (3% for VH vs. 10% for LH; OR: 3.4; 95%CI: 0.95-13.5; p=0.08). At multivariable analysis complication rates increased as BMI increase (OR: 1.01 (1.00-1.02) for 1-unit increase in BMI; p=0.05). Independently, LH correlated with reduced hospital stay (OR: 0.63 (95%CI: 0.49-0.82); p=0.001) and complication rates (OR: 0.91 (95%CI: 0.85-0.97); p=0.01).
Conclusions:
In obese women affected by benign uterine disease LH and VH should not be denied on the basis of the mere BMI, per se. In this setting, LH upholds effectiveness of VH, improving postoperative outcomes. However, complication rate increases as BMI increase, regardless surgical route.

