Repeat resective surgery in complex pediatric refractory epilepsy: lessons learned
Related Experiment Video
Updated: Apr 14, 2026
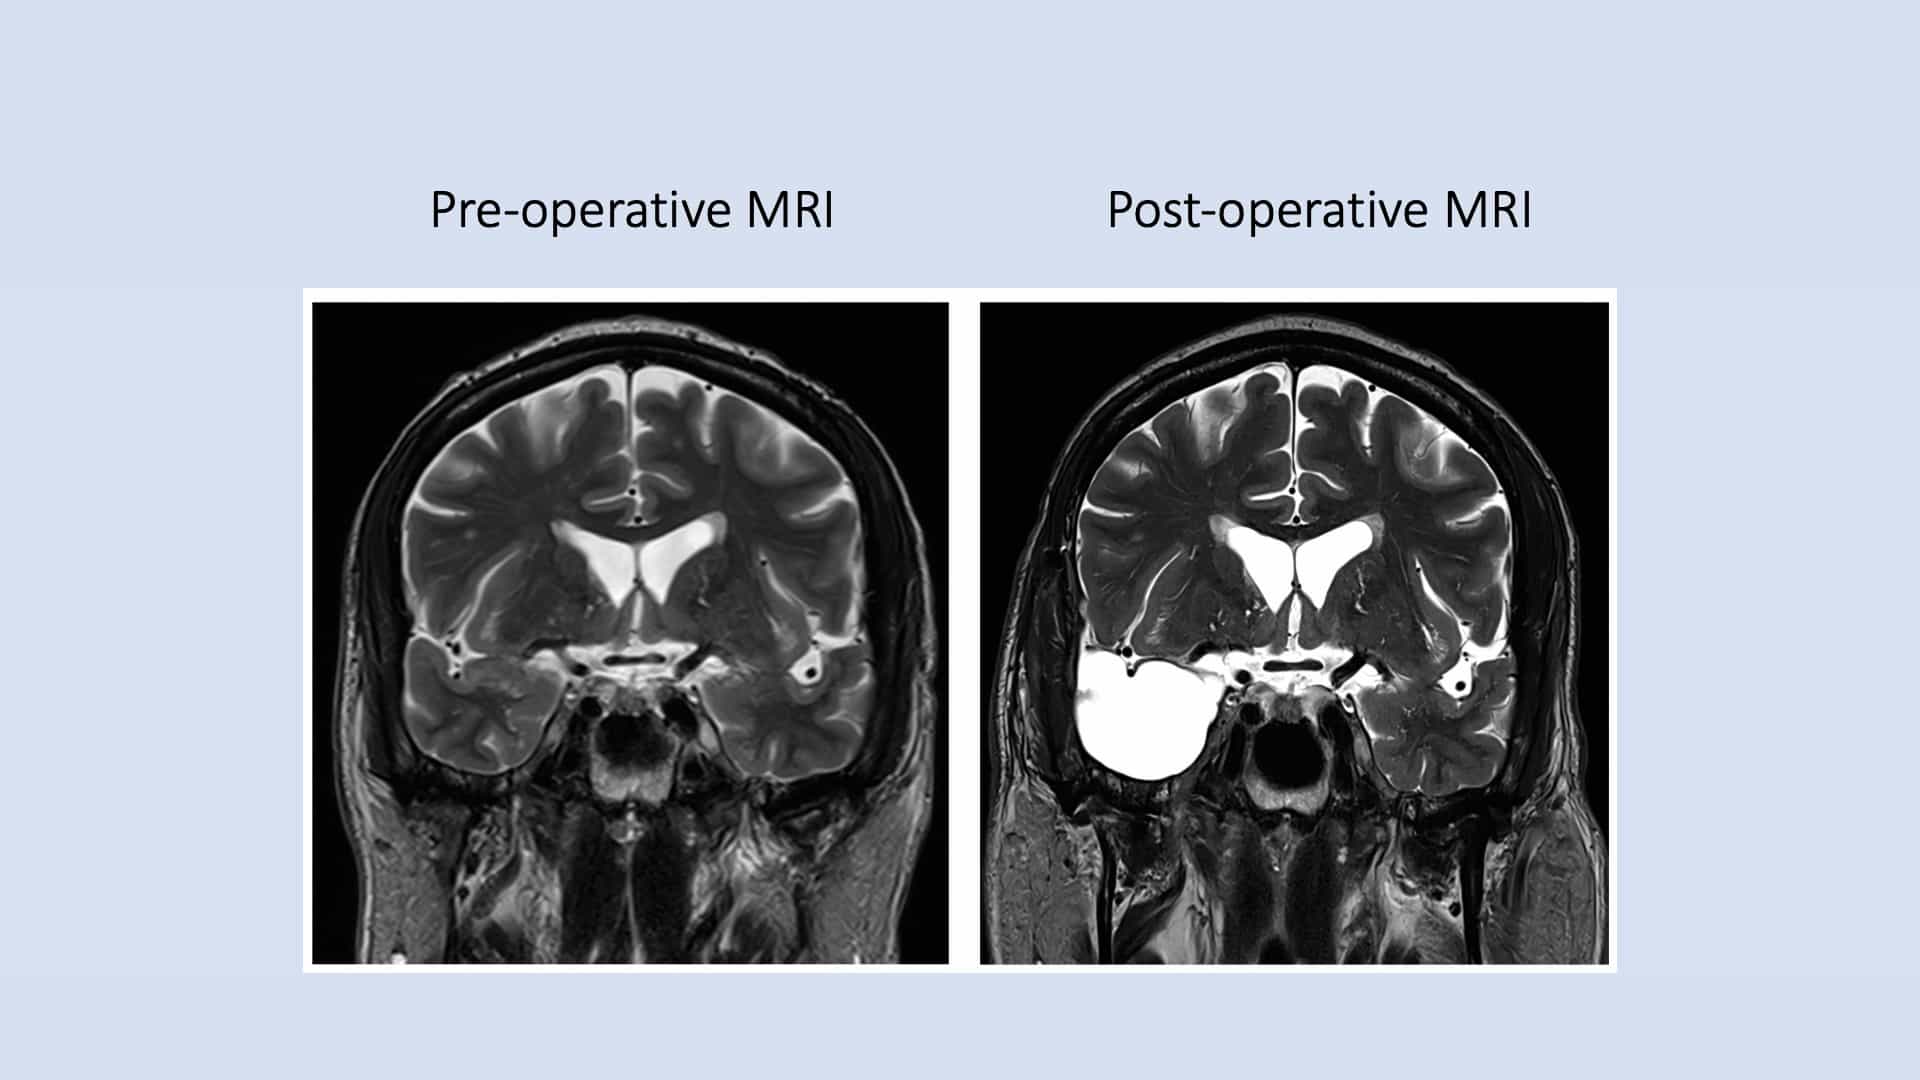
Anteromesial Temporal Lobectomy for Medically Intractable Temporal Lobe Epilepsy: An Operative Study
Published on: August 15, 2025
Regina S Bower1, Elaine C Wirrell2, Laurence J Eckel3
1Departments of 1 Neurosurgery.

Abstract:
OBJECT Resection can sometimes offer the best chance of meaningful seizure reduction in children with medically intractable epilepsy. However, when surgery fails to achieve the desired outcome, reoperation may be an option. The authors sought to investigate outcomes following resective reoperation in pediatric patients with refractory epilepsy, excluding tumoral epilepsies. Differences in preoperative workup between surgeries are analyzed to identify factors influencing outcomes and complications in this complex group. METHODS Medical records were reviewed for all pediatric patients undergoing a repeat resective surgery for refractory epilepsy at the authors' institution between 2005 and 2012. Tumor and vascular etiologies were excluded. Preoperative evaluation and outcomes were analyzed for each surgery and compared. RESULTS Ten patients met all inclusion criteria. The median age at seizure onset was 4.5 months. Preoperative MRI revealed no lesion in 30%. Nonspecific gliosis and cortical dysplasia were the most common pathologies. The majority of preoperative workups included MRI, video-electroencephalography (EEG), and SISCOM. Intracranial EEG was performed for 60% for the first presurgical evaluation and 70% for the second evaluation. The goal of surgery was palliative in 4 patients with widespread cortical dysplasia. The final Engel outcome was Class I in 50%. The rate of favorable outcome (Engel Class I-II) was 70%. The complication rate for the initial surgery was 10%. However, the rate increased to 50% with the second surgery, and 3 of these 5 complications were pseudomeningoceles requiring shunt placement (2 of the 3 patients underwent hemispherotomy). CONCLUSIONS Resective reoperation for pediatric refractory epilepsy has a high rate of favorable outcome and should be considered in appropriate candidates, even as a palliative measure. Intracranial EEG monitoring should be considered on initial workup in cases where the results of imaging or EEG studies are ambiguous or conflicting. Epilepsy secondary to cortical dysplasia, especially if the dysplasia is not seen clearly on MRI, can be difficult to cure surgically. Therefore, in these cases, as large a resection as can be safely accomplished should be done, particularly when the goal is palliative. The rate of complications, particularly pseudomeningocele ultimately requiring shunt placement, is much higher following reoperation, and patients should be counseled accordingly.
More Related Videos
 09:57
Author Spotlight: Advancing Pediatric Epilepsy Surgery in Children Through Novel Biomarkers and Enhanced Localization
Published on: September 20, 2024
 05:54
Stereo-Electro-Encephalo-Graphy SEEG With Robotic Assistance in the Presurgical Evaluation of Medical Refractory Epilepsy: A Technical Note
Published on: June 13, 2016
Related Concept Videos
 01:24
Epilepsy and Seizures: Overview
Various factors can trigger epilepsy, including genetic factors, brain damage, metabolic causes, and unknown etiology. Diagnosis of epilepsy involves electroencephalography (EEG), which...
 01:30
Psychosurgery
Historical Development of Psychosurgery
In the 1930s, Portuguese neurologist Antonio Egas Moniz introduced a surgical procedure designed...