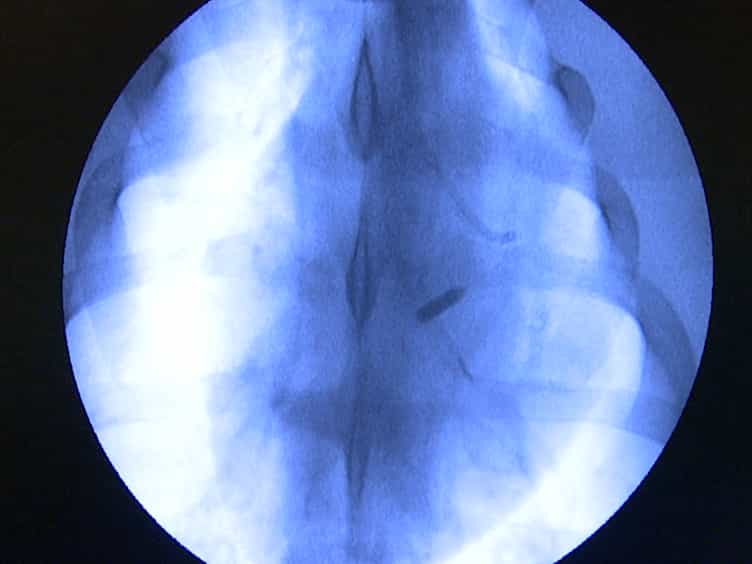
Delayed clopidogrel transit during myocardial infarction evident on angiography
Related Experiment Video
Updated: Apr 13, 2026

Myocardial Infarction and Functional Outcome Assessment in Pigs
Published on: April 25, 2014
Joanna Ghobrial1, C Michael Gibson, Duane S Pinto
1Interventional Cardiology Section, 1 Deaconess Road, Palmer 415, Boston, MA 02215 USA. dpinto@bidmc.harvard.edu.

Insights
Delayed absorption of oral clopidogrel, an antiplatelet medication, was visualized in a patient with non-ST segment elevation myocardial infarction (NSTEMI). This finding suggests gastrointestinal transit time may impact treatment effectiveness.
Area of Science:
- Cardiology
- Pharmacology
Background:
- Non-ST segment elevation myocardial infarction (NSTEMI) requires prompt antiplatelet therapy.
- Clopidogrel, a P2Y12 inhibitor, is a common oral antiplatelet agent, but its activation is dependent on hepatic and gastrointestinal metabolism.
- Optimal platelet inhibition with oral clopidogrel typically requires at least 2 hours for maximal effect.
Observation:
- A patient diagnosed with NSTEMI received an oral loading dose of 600 mg clopidogrel.
- Angiography performed 1.5 hours post-administration revealed intact clopidogrel tablets in the stomach.
- This directly visualized delayed gastric emptying, suggesting poor drug absorption.
Findings:
- Oral clopidogrel loading dose was not adequately absorbed in a timely manner.
- Intact drug tablets in the stomach indicate a significant delay in gastrointestinal transit.
- Potential for suboptimal antiplatelet effect due to delayed absorption.
Implications:
- Delayed gastrointestinal transit can be a significant factor limiting the efficacy of oral antiplatelet agents like clopidogrel.
- This case highlights the need to consider factors beyond metabolic pathways affecting drug absorption.
- Further investigation into the impact of gastrointestinal transit time on antiplatelet therapy is warranted.
Abstract:
We describe the case of a patient with non-ST segment elevation myocardial infarction (NSTEMI) where a limitation of oral clopidogrel loading prior to percutaneous coronary intervention (PCI) was directly visualized on angiography. Clopidogrel is a thienopyridine antiplatelet agent used in acute coronary syndromes. It reduces platelet aggregation via inhibition of the P2Y12 receptor. Clopidogrel is an inactive metabolite that is metabolized into the active metabolite by the cytochrome P450 isoenzymes located mostly in the liver and partly in the gastrointestinal system. As such, it requires at least 2 hours to reach maximal effect. A 63-year-old female went to an outside facility where she was diagnosed with NSTEMI and underwent angiography. She was administered 324 mg of aspirin and 600 mg of clopidogrel, and was transferred to our facility. Upon arrival, approximately 1.5 hours after the oral loading dose, the clopidogrel tablets were visualized intact in the stomach during angiography, implying a very low likelihood of adequate absorption or antiplatelet effect. This observation raises the concern that delayed gastrointestinal transit, apart from other metabolic derangements, may be a factor in achieving optimal platelet inhibition using oral agents.
More Related Videos
 05:26
Postconditioning with Lactate-enriched Blood for Cardioprotection in ST-segment Elevation Myocardial Infarction
Published on: May 28, 2019
 10:01
Improvement of a Closed Chest Porcine Myocardial Infarction Model by Standardization of Tissue and Blood Sampling Procedures
Published on: March 12, 2018
Related Concept Videos
 01:30
Acute Coronary Syndrome III: Diagnostic Studies
 01:28
Acute Coronary Syndrome IV: Interprofessional Care
 01:30
Acute Coronary Syndrome I: Introduction
 01:19
Acute Coronary Syndrome II: Pathophysiology and Clinical Manifestations