Related Experiment Video
Updated: Apr 12, 2026

Diffusion Tensor Magnetic Resonance Imaging in Chronic Spinal Cord Compression
Published on: May 7, 2019
Detection of hand and leg motor tract injury using novel diffusion tensor MRI tractography in children with central
Jeong-Won Jeong1, Jessica Lee2, David O Kamson3
1Translational Imaging Laboratory, Children's Hospital of Michigan, Detroit, MI, USA; Carman and Ann Adams Department of Pediatrics, School of Medicine, Wayne State University, Detroit, MI, USA; Department of Neurology, School of Medicine, Wayne State University, Detroit, MI, USA.

Purpose:
To examine whether an objective segmenation of corticospinal tract (CST) associated with hand and leg movements can be used to detect central motor weakness in the corresponding extremities in a pediatric population.
Material And Methods:
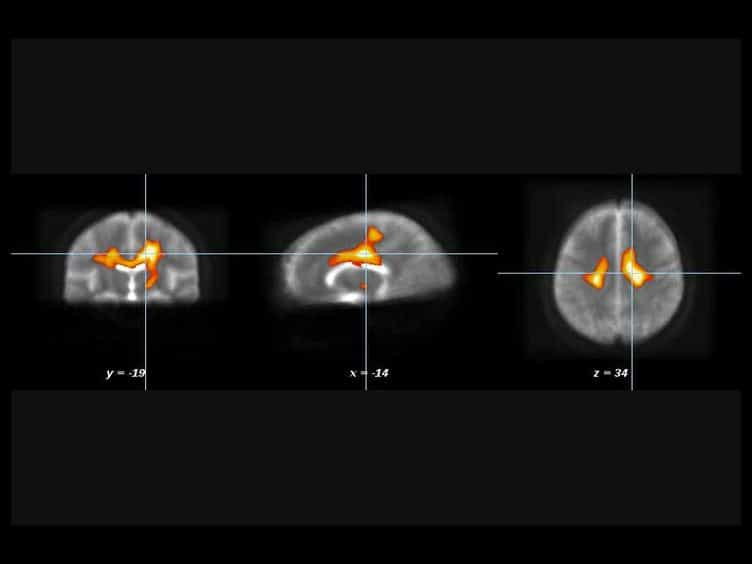
This retrospective study included diffusion tensor imaging (DTI) of 25 children with central paresis affecting at least one limb (age: 9.0±4.2years, 15 boys, 5/13/7 children with left/right/both hemispheric lesions including ischemia, cyst, and gliosis), as well as 42 pediatric control subjects with no motor dysfunction (age: 9.0±5.5years, 21 boys, 31 healthy/11 non-lesional epilepsy children). Leg- and hand-related CST pathways were segmented using DTI-maximum a posteriori (DTI-MAP) classification. The resulting CST volumes were then divided by total supratentorial white matter volume, resulting in a marker called "normalized streamline volume ratio (NSVR)" to quantify the degree of axonal loss in separate CST pathways associated with leg and hand motor functions. A receiver operating characteristic curve was applied to measure the accuracy of this marker to identify extremities with motor weakness.
Results:
NSVR values of hand/leg CST selectively achieved the following values of accuracy/sensitivity/specificity: 0.84/0.84/0.57, 0.82/0.81/0.55, 0.78/0.75/0.55, 0.79/0.81/0.54 at a cut-off of 0.03/0.03/0.03/0.02 for right hand CST, left hand CST, right leg CST, and left leg CST, respectively. Motor weakness of hand and leg was most likely present at the cut-off values of hand and leg NSVR (i.e., 0.029/0.028/0.025/0.020 for left-hand/right-hand/left-leg/right-leg). The control group showed a moderate age-related increase in absolute CST volumes and a biphasic age-related variation of the normalized CST volumes, which were lacking in the paretic children.
Conclusions:
This study demonstrates that DTI-MAP classification may provide a new imaging tool to quantify axonal loss in children with central motor dysfunction. Using this technique, we found that early-life brain lesions affect the maturational trajectory of the primary motor pathway which may be used as an effective marker to facilitate evidence-based treatment of paretic children.