Related Experiment Video
Updated: Apr 12, 2026

A Retrospective Study on Endoscopic Surgery for the Treatment of Paravertebral Abscess in Spinal Tuberculosis Patients
Published on: October 25, 2024
Late onset of progressive neurological deficits in severe angular kyphosis related to tuberculosis spondylitis
1Department of Orthopaedic Surgery, Seoul St. Mary's Hospital, College of Medicine, The Catholic University of Korea, 222 Banpodae-ro, Seocho-Gu, Seoul, 137-701, Korea. kyh@catholic.ac.kr.

Purpose:
To investigate the causes of late-onset, progressive neurological deficits in patients with severe angular kyphosis caused by spondylitis secondary to tuberculosis (TB spondylitis).
Methods:
From 2000 to 2011, 36 patients with severe angular kyphosis secondary to TB spondylitis (TB kyphosis) were enrolled in the study. All patients had late-onset, progressive neurological deficits. The causes of these deficits were classified with respect to the level of the causative lesion. Group A (n = 25, 69.4%) comprised patients whose neurological deficits resulted from the kyphosis itself. Patients in group B (n = 11, 30.6%) had developed neurological symptoms related to a lesion cephalad or caudal from the kyphosis. Surgical intervention was performed in 23 patients; 13 patients were treated conservatively. Clinical outcomes were evaluated using the American Spinal Injury Association (ASIA) impairment scale.
Results:
The late onset of neurological deficits was attributed to cord compression, pure cord distraction, stenosis, and instability above or below the level of the angular kyphosis. An improvement of the neurological symptoms at the cord level after surgical intervention, as indicated by a change from a non-ambulatory (ASIA impairment scale A/C) to an ambulatory (ASIA D/E) status, occurred in four of nine (44.4%) surgically treated patients. However, only 2 of 10 (20.0%) patients treated conservatively showed cord level improvement, as assessed using the ASIA impairment scale.
Conclusions:
In their evaluation of paraplegic patients, spine surgeons should consider the many potential causes of late-onset neurological deficits in TB spondylitis to avoid performing unnecessary surgery. A simpler procedure may yield equivalent results.
Related Concept Videos
 01:31
Pulmonary Tuberculosis III
The first classification is based on the development of the disease, and it includes the following categories:
 01:29
Pulmonary Tuberculosis I
Causative Organism
The primary infectious agent causing tuberculosis is Mycobacterium tuberculosis, a slow-growing, acid-fast, aerobic rod that exhibits sensitivity to heat and ultraviolet light. Instances of Mycobacterium bovis and Mycobacterium avium contributing to the development of TB infection are rare.
Mode of...
 01:28
Pulmonary Tuberculosis V
Latent tuberculosis infection occurs when TB bacteria are present in a person's body, but are not causing illness or symptoms. It is not contagious, and preventive treatment is crucial to avoid the...
 01:28
Pulmonary Tuberculosis II
Here is a detailed explanation of its pathophysiology:
Transmission: The process begins when a person inhales droplet nuclei containing M. tuberculosis. These are typically released into the air when an individual with pulmonary or...
 01:16
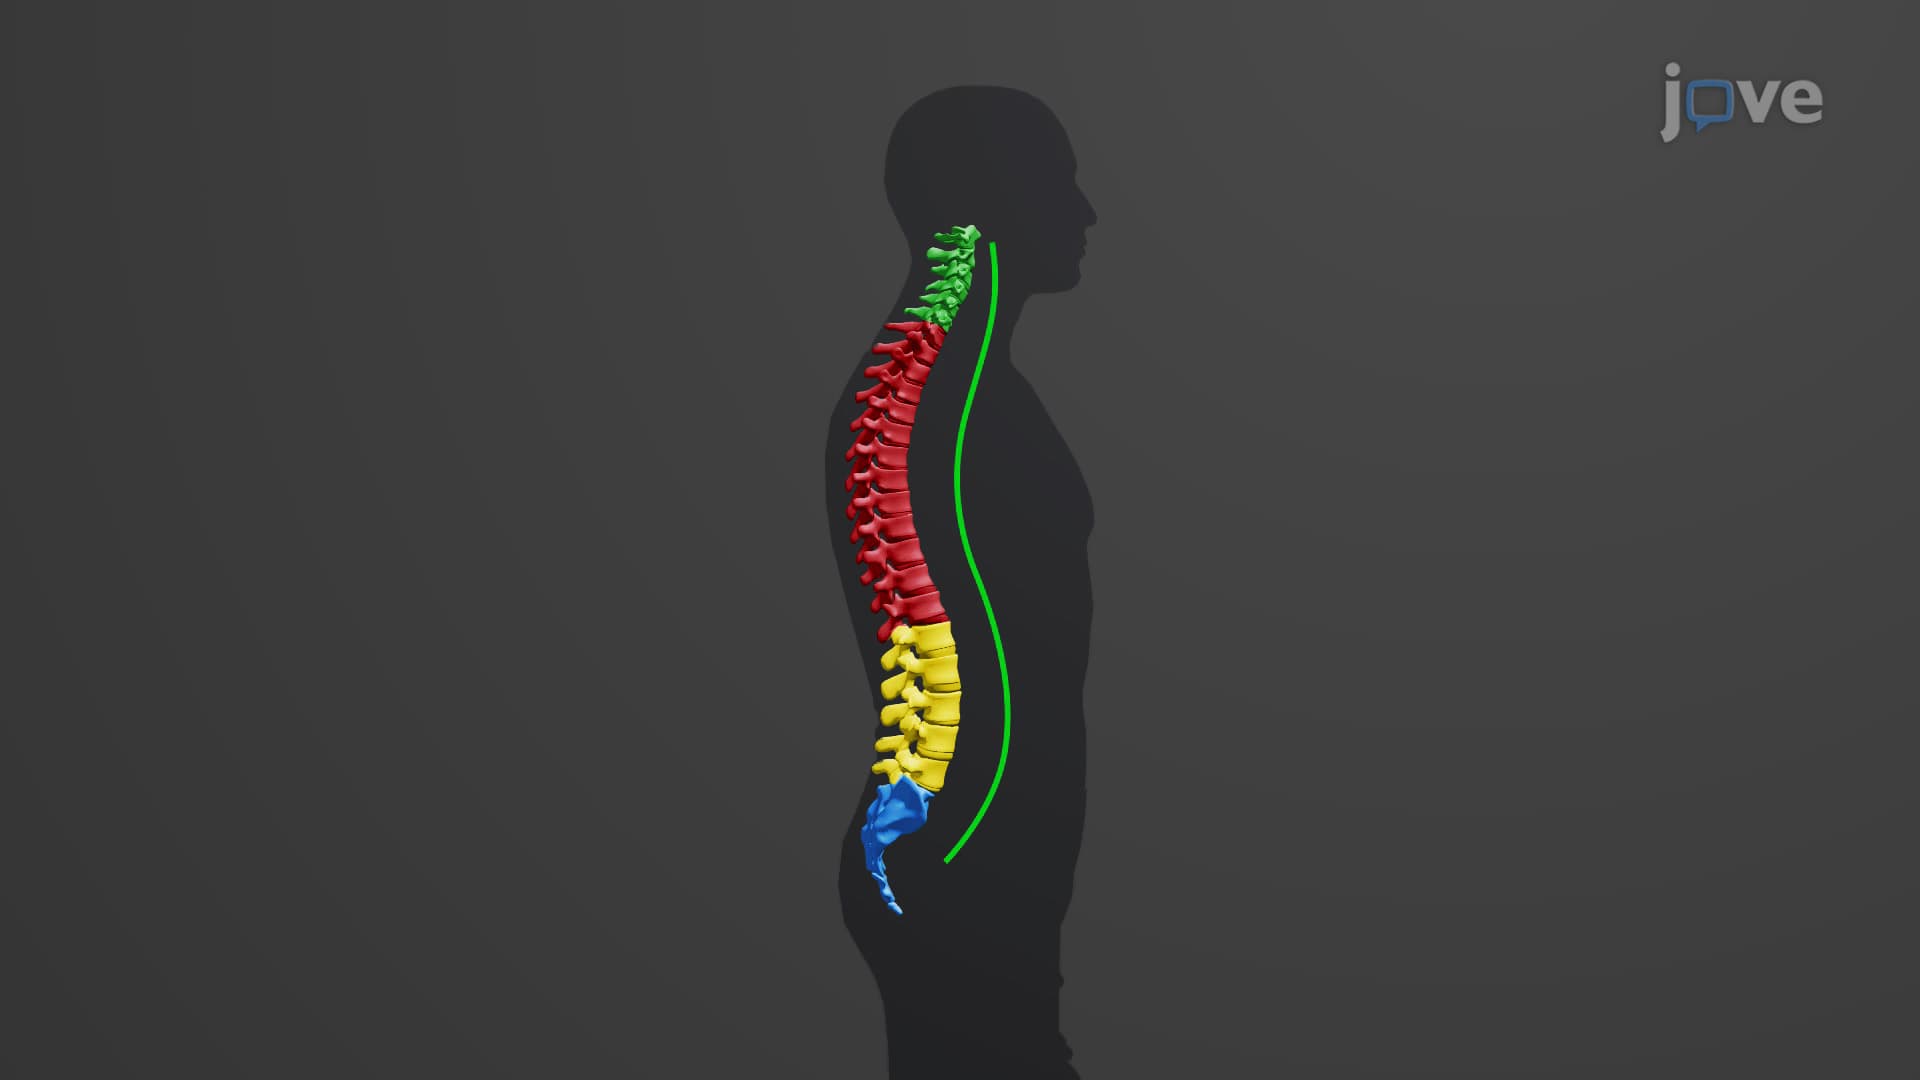
Vertebral Column: Regions and Curvature
Regions of the Vertebral Column
In an adult, the spine is subdivided into five regions: the cervical, the thoracic, the lumbar, the sacral, and the coccygeal region. The spine initially develops as a series of 33 vertebrae; after 20 years of age, the nine bones in the sacral region, five sacral, and four coccygeal bones fuse to form...