Related Experiment Video
Updated: Apr 12, 2026
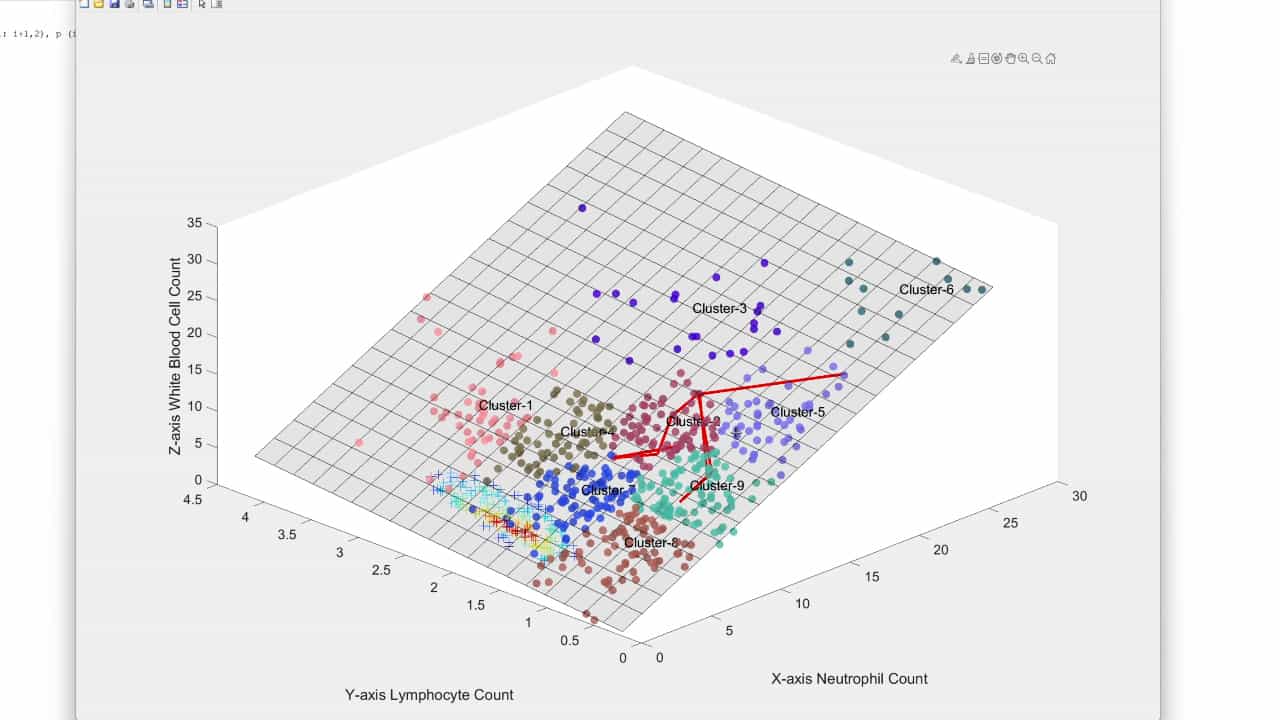

A Data-Driven Approach to Quantifying Immune States in Sepsis
Published on: February 7, 2025
Physician documentation of sepsis syndrome is associated with more aggressive treatment
Lisa R Stoneking1, John P Winkler2, Lawrence A DeLuca1
1The University of Arizona College of Medicine, Department of Emergency Medicine, Tucson, Arizona.

Introduction:
Timely recognition and treatment of sepsis improves survival. The objective is to examine the association between recognition of sepsis and timeliness of treatments.
Methods:
We identified a retrospective cohort of emergency department (ED) patients with positive blood cultures from May 2007 to January 2009, and reviewed vital signs, imaging, laboratory data, and physician/nursing charts. Patients who met systemic inflammatory response syndrome (SIRS) criteria and had evidence of infection available to the treating clinician at the time of the encounter were classified as having sepsis. Patients were dichotomized as RECOGNIZED if sepsis was explicitly articulated in the patient record or if a sepsis order set was launched, or as UNRECOGNIZED if neither of these two criteria were met. We used median regression to compare time to antibiotic administration and total volume of fluid resuscitation between groups, controlling for age, sex, and sepsis severity.
Results:
SIRS criteria were present in 228/315 (72.4%) cases. Our record review identified sepsis syndromes in 214 (67.9%) cases of which 118 (55.1%) had sepsis, 64 (29.9%) had severe sepsis, and 32 (15.0%) had septic shock. The treating team contemplated sepsis (RECOGNIZED) in 123 (57.6%) patients. Compared to the UNRECOGNIZED group, the RECOGNIZED group had a higher use of antibiotics in the ED (91.9 vs.75.8%, p=0.002), more patients aged 60 years or older (56.9 vs. 33.0%, p=0.001), and more severe cases (septic shock: 18.7 vs. 9.9%, severe sepsis: 39.0 vs.17.6%, sepsis: 42.3 vs.72.5%; p<0.001). The median time to antibiotic (minutes) was lower in the RECOGNIZED (142) versus UNRECOGNIZED (229) group, with an adjusted median difference of -74 minutes (95% CI [-128 to -19]). The median total volume of fluid resuscitation (mL) was higher in the RECOGNIZED (1,600 mL) compared to the UNRECOGNIZED (1,000 mL) group. However, the adjusted median difference was not statistically significant: 262 mL (95% CI [ -171 to 694 mL]).
Conclusion:
Patients whose emergency physicians articulated sepsis syndrome in their documentation or who launched the sepsis order set received antibiotics sooner and received more total volume of fluid. Age <60 and absence of fever are factors associated with lack of recognition of sepsis cases.
Related Concept Videos
 01:26
Guidelines for Nursing Documentation II
Timely documentation is crucial to ensure continuity of care for patients. Any delays in recording or reporting medical information can result in medical errors and even adverse patient outcomes. From medication administration to diagnostic test results, every detail must be accurately and promptly documented to provide the best possible care for patients.
 01:06
Legal Guidelines for Documentation
 01:29
Documentation in Long-Term and Home Healthcare Setting
Long-Term Care Facilities
 01:30
Guidelines for Nursing Documentation I
Factual:
The following points emphasize the significance of upholding accurate and unbiased documentation in healthcare.
 01:28
Acute Pyelonephritis II: Diagnostic Studies and Management
 01:15
Methods of Documentation VI: Case Management Model
For example, a patient with a chronic...