Related Experiment Video
Updated: Apr 12, 2026
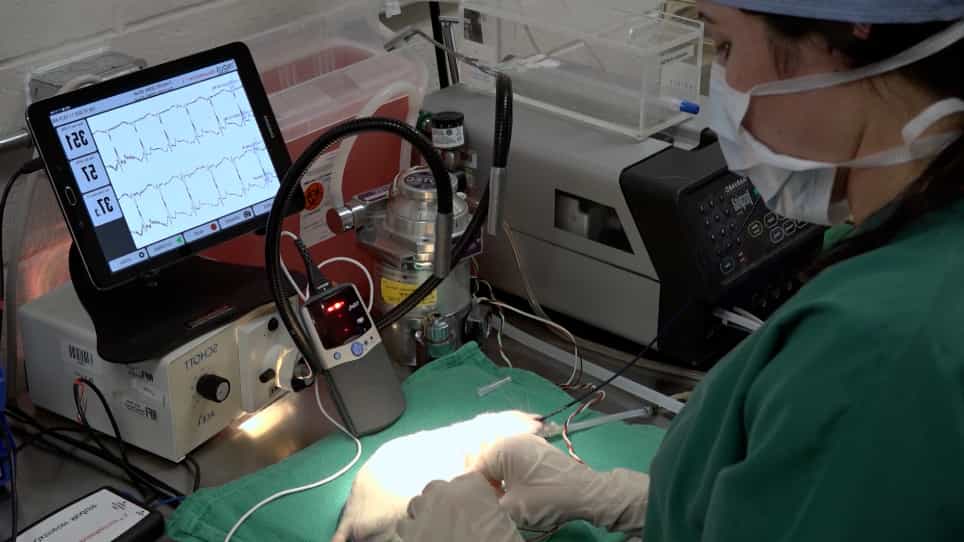

An Image Guided Transapical Mitral Valve Leaflet Puncture Model of Controlled Volume Overload from Mitral Regurgitation in the Rat
Published on: May 19, 2020
Geometric perturbations in multiheaded papillary tip positions associated with acute ovine ischemic mitral
Tomasz A Timek1, David T Lai2, Wolfgang Bothe2
1Meijer Heart and Vascular Institute at Spectrum Health, Grand Rapids, Mich.

Background:
Novel surgical approaches are focusing on the "ventricular disease" of ischemic mitral regurgitation (IMR), to correct altered papillary muscle (PM) tip positions (apical displacement) and ameliorate leaflet tethering. Due to the anatomic complexity of the subvalvular apparatus, however, the precise geometric perturbations of the multiheaded PM tips associated with IMR remain uncharacterized.
Methods:
In 6 adult sheep, we implanted 3 markers on each PM. To specifically identify distinct PM tips, 1 marker was placed on the PM origin of the dominant chord to the anterior, posterior, and commissural leaflets. Nine markers were placed on the edge of the posterior mitral leaflet, and 5 on the edge of the anterior mitral leaflet. Eight markers were sewn around the mitral annulus. Animals were studied immediately postoperatively, with biplane videofluoroscopy and transesophageal echocardiography, before and during acute snare occlusion of the proximal left circumflex coronary artery, to induce IMR. Papillary muscle tip and leaflet edge geometry was expressed as the orthogonal distance of each respective marker to the least-squares mitral annulus plane at end-systole. In addition, the distance from each PM tip marker to the mitral annulus "saddle horn" was calculated.
Results:
Acute left circumflex occlusion significantly increased mitral regurgitation from a baseline of 0.7 ± 0.3 to 2.5 ± 0.5 (P < .05). The IMR was associated with posterior leaflet restriction near the central leaflet edge, with simultaneous prolapse of both leaflets near the posterior commissure. No apical displacement of PM tips was observed during IMR, although the posterior PM moved farther away from the midseptal annulus.
Conclusions:
During acute ischemia, no apical displacement of any PM tip was observed. Posterior PM movement away from the annular saddle horn, and toward the annulus, was associated with IMR and leaflet prolapse near the posterior commissure, and with restriction near the valve center. These data may help guide development of surgical interventions aimed at PM repositioning.
More Related Videos
 11:50
High-frequency High-resolution Echocardiography: First Evidence on Non-invasive Repeated Measure of Myocardial Strain, Contractility, and Mitral Regurgitation in the Ischemia-reperfused Murine Heart
Published on: July 9, 2010
 06:56
Author Spotlight: Advancing Cardiac Procedure Testing Prior to Embarking on Large Animal Studies
Published on: August 25, 2023
Related Concept Videos
 01:20
Mitral Regurgitation I: Introduction
 01:27
Mitral Valve Prolapse I: Introduction
 01:25
Mitral Regurgitation III: Medical Management
 01:28
Mitral Regurgitation IV: Nursing Management
 01:23
Mitral Regurgitation II: Clinical Features and Diagnostic Tests
 01:15
Aortic Regurgitation I: Introduction