Related Experiment Video
Updated: Apr 9, 2026


Laparoscopic Common Bile Duct Exploration Followed by Primary Suture Using a Modified Bile Duct Incision
Published on: May 2, 2025
Surgeons, ERCP, and laparoscopic common bile duct exploration: do we need a standard approach for common bile duct
Rebeccah B Baucom1, Irene D Feurer2,3, Julia S Shelton2
1Department of Surgery, Vanderbilt University Medical Center, D-5203 MCN, VUMC, 1161 Medical Center Drive, Nashville, TN, 37232, USA. rebeccah.baucom@vanderbilt.edu.

Background:
Variation exists in the management of choledocholithiasis (CDL). This study evaluated associations between demographic and practice-related characteristics and CDL management.
Methods:
A 22-item, web-based survey was administered to US general surgeons. Respondents were classified into metropolitan or nonmetropolitan groups by zip code. Univariate tests and multivariable logistic regression were used to determine factors associated with CDL management preferences.
Results:
The survey was sent to 32,932 surgeons; 9902 performed laparoscopic cholecystectomy within the last year; 750 of 771 respondents had a valid US zip code and were included in the analysis. Mean practice time was 18 ± 10 years, 87% were male, and 83% practiced in a metropolitan area. For preoperatively known CDL, 86% chose preoperative endoscopic retrograde cholangiopancreatography (ERCP). Those in metropolitan areas were more likely to select preoperative ERCP than those in nonmetropolitan areas (88 vs. 79%, p < 0.001). For CDL discovered intraoperatively, 30% selected laparoscopic common bile duct exploration (LCBDE) as their preferred method of management with no difference between metropolitan and nonmetropolitan areas (30 vs. 26%, p = 0.335). The top reasons for not performing LCBDE were: having a reliable ERCP proceduralist available, lack of equipment, and lack of comfort performing LCBDE. Factors associated with preoperative ERCP were: metropolitan status, selective intraoperative cholangiography (IOC), and availability of a reliable ERCP proceduralist. Those who perform selective IOC were 70% less likely to prefer LCBDE (OR 0.32, 95% CI 0.18-0.57, p < 0.001). Those with a reliable ERCP proceduralist available were 90% less likely to prefer LCBDE (OR 0.10, 95% CI 0.04-0.26, p < 0.001).
Conclusions:
The majority of respondents preferred ERCP for the management of CDL. Having a reliable ERCP proceduralist available, use of selective IOC, and metropolitan status were independently associated with preoperative ERCP. Postoperative ERCP was preferred for managing intraoperatively discovered CDL. Many surgeons are uncomfortable performing LCBDE, and increased training may be needed.
More Related Videos
 07:36
Laparoscopic Common Bile Duct Exploration in Patients with a Previous History of Biliary Tract Surgery
Published on: February 10, 2023
 04:02
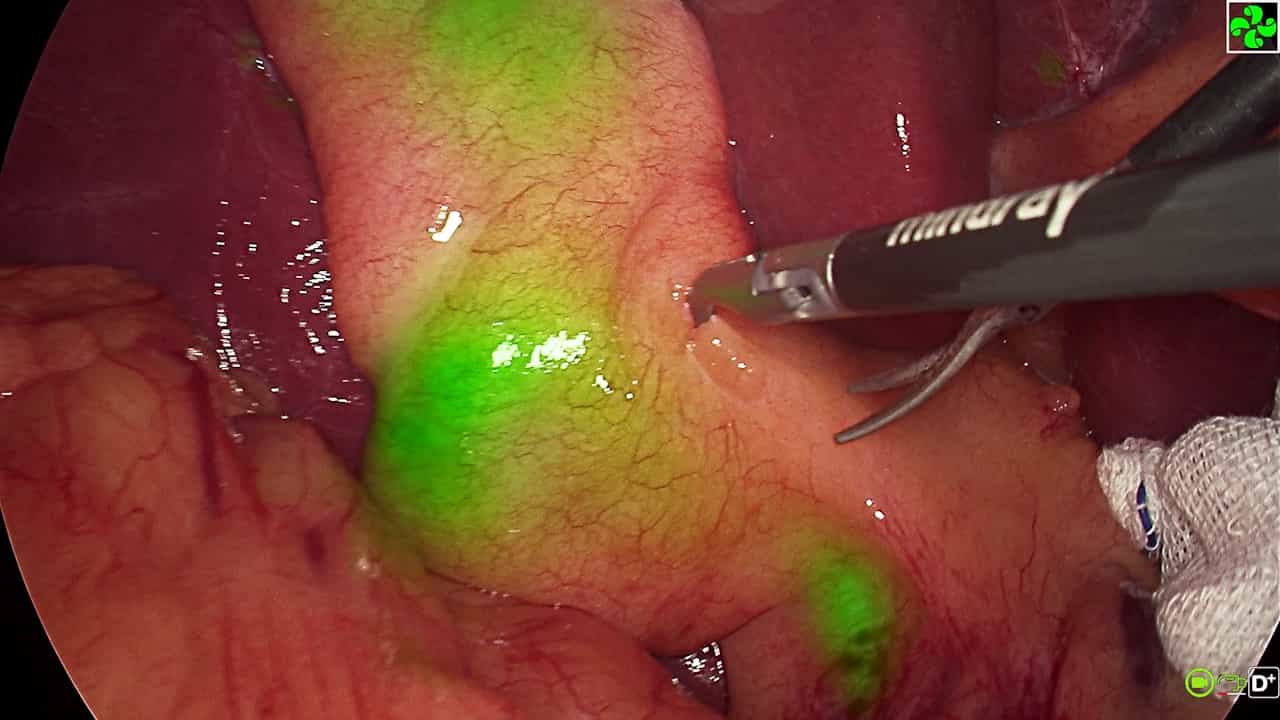
Laparoscopic Cholecystectomy with Indocyanine Green Fluorescence: Choledochoscopic Stone Extraction and Primary Duct Suture
Published on: November 25, 2025
