Related Experiment Video
Updated: Apr 7, 2026

Author Spotlight: Unveiling the Connection Between Sleep Disorders and Cognitive Symptoms in Depression
Published on: April 26, 2024
Cognitive Behavioral Therapy for Insomnia Comorbid With Psychiatric and Medical Conditions: A Meta-analysis
Jade Q Wu1, Erica R Appleman1, Robert D Salazar1
1Department of Psychological and Brain Sciences, Boston University, Boston, Massachusetts.

Importance:
Cognitive behavioral therapy for insomnia (CBT-I) is the most prominent nonpharmacologic treatment for insomnia disorders. Although meta-analyses have examined primary insomnia, less is known about the comparative efficacy of CBT-I on comorbid insomnia.
Objective:
To examine the efficacy of CBT-I for insomnia comorbid with psychiatric and/or medical conditions for (1) remission from insomnia; (2) self-reported sleep efficiency, sleep onset latency, wake after sleep onset, total sleep time, and subjective sleep quality; and (3) comorbid symptoms.
Data Sources:
A systematic search was conducted on June 2, 2014, through PubMed, PsycINFO, the Cochrane Library, and manual searches. Search terms included (1) CBT-I or CBT or cognitive behavioral [and its variations] or behavioral therapy [and its variations] or behavioral sleep medicine or stimulus control or sleep restriction or relaxation therapy or relaxation training or progressive muscle relaxation or paradoxical intention; and (2) insomnia or sleep disturbance.
Study Selection:
Studies were included if they were randomized clinical trials with at least one CBT-I arm and had an adult population meeting diagnostic criteria for insomnia as well as a concomitant condition. Inclusion in final analyses (37 studies) was based on consensus between 3 authors' independent screenings.
Data Extraction And Synthesis:
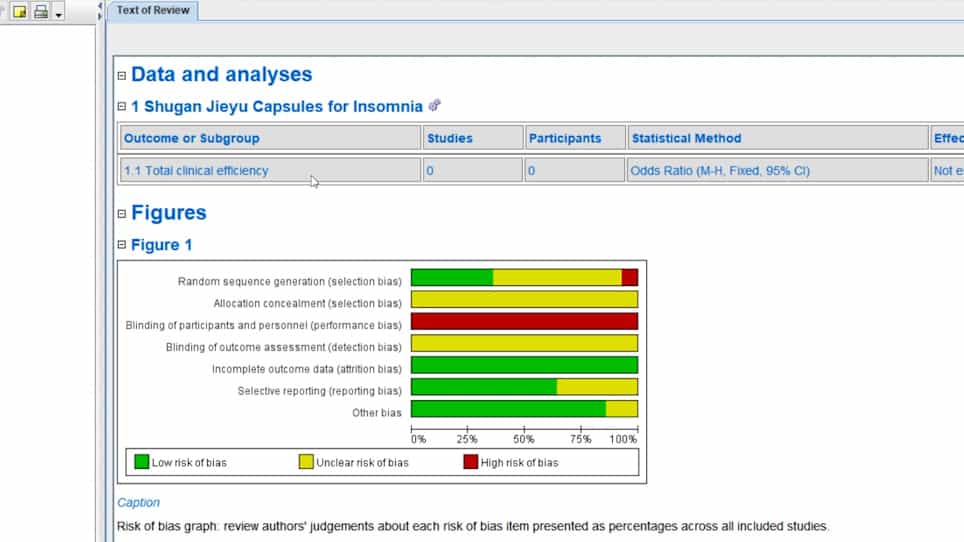
Data were independently extracted by 2 authors and pooled using a random-effects model. Study quality was independently evaluated by 2 authors using the Cochrane risk of bias assessment tool.
Main Outcomes And Measures:
A priori main outcomes (ie, clinical sleep and comorbid outcomes) were derived from sleep diary and other self-report measures.
Results:
At posttreatment evaluation, 36.0% of patients who received CBT-I were in remission from insomnia compared with 16.9% of those in control or comparison conditions (pooled odds ratio, 3.28; 95% CI, 2.30-4.68; P < .001). Pretreatment and posttreatment controlled effect sizes were medium to large for most sleep parameters (sleep efficiency: Hedges g = 0.91 [95% CI, 0.74 to 1.08]; sleep onset latency: Hedges g = 0.80 [95% CI, 0.60 to 1.00]; wake after sleep onset: Hedges g = 0.68; sleep quality: Hedges g = 0.84; all P < .001), except total sleep time. Comorbid outcomes yielded a small effect size (Hedges g = 0.39 [95% CI, 0.60-0.98]; P < .001); improvements were greater in psychiatric than in medical populations (Hedges g = 0.20 [95% CI, 0.09-0.30]; χ2 test for interaction = 12.30; P < .001).
Conclusions And Relevance:
Cognitive behavioral therapy for insomnia is efficacious for improving insomnia symptoms and sleep parameters for patients with comorbid insomnia. A small to medium positive effect was found across comorbid outcomes, with larger effects on psychiatric conditions compared with medical conditions. Large-scale studies with more rigorous designs to reduce detection and performance bias are needed to improve the quality of the evidence.