Related Experiment Video
Updated: Apr 6, 2026
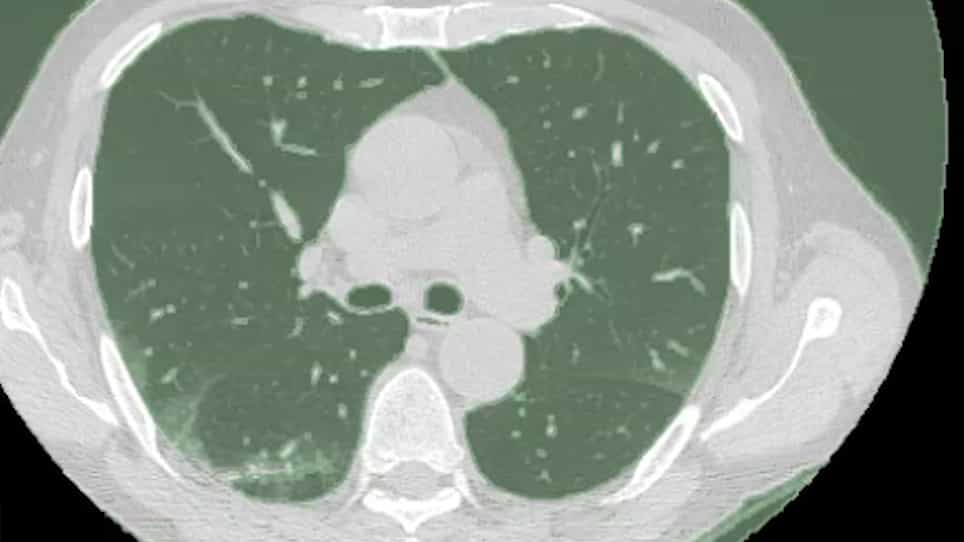

Lung CT Segmentation to Identify Consolidations and Ground Glass Areas for Quantitative Assesment of SARS-CoV Pneumonia
Published on: December 19, 2020
Using Standardized Interpretation of Chest Radiographs to Identify Adults with Bacterial Pneumonia--Guatemala,
Jonathan M Wortham1, Jennifer Gray2, Jennifer Verani1
1Centers for Disease Control and Prevention, Atlanta, Georgia, United States of America.

Background:
Bacterial pneumonia is a leading cause of illness and death worldwide, but quantifying its burden is difficult due to insensitive diagnostics. Although World Health Organization (WHO) protocol standardizes pediatric chest radiograph (CXR) interpretation for epidemiologic studies of bacterial pneumonia, its validity in adults is unknown.
Methods:
Patients (age ≥ 15 years) admitted with respiratory infections to two Guatemalan hospitals between November 2007 and March 2012 had urine and nasopharyngeal/oropharyngeal (NP/OP) swabs collected; blood cultures and CXR were also performed at physician clinical discretion. 'Any bacterial infection' was defined as a positive urine pneumococcal antigen test, isolation of a bacterial pneumonia pathogen from blood culture, or detection of an atypical bacterial pathogen by polymerase chain reaction (PCR) of nasopharyngeal/oropharyngeal (NP/OP) specimens. 'Viral infection' was defined as detection of viral pathogens by PCR of NP/OP specimens. CXRs were interpreted according to the WHO protocol as having 'endpoint consolidation', 'other infiltrate', or 'normal' findings. We examined associations between bacterial and viral infections and endpoint consolidation.
Findings:
Urine antigen and/or blood culture results were available for 721 patients with CXR interpretations; of these, 385 (53%) had endpoint consolidation and 253 (35%) had other infiltrate. Any bacterial infection was detected in 119 (17%) patients, including 106 (89%) pneumococcal infections. Any bacterial infection (Diagnostic Odds Ratio [DOR] = 2.9; 95% confidence Interval (CI): 1.3-7.9) and pneumococcal infection (DOR = 3.4; 95% CI: 1.5-10.0) were associated with 'endpoint consolidation', but not 'other infiltrate' (DOR = 1.7; 95% CI: 0.7-4.9, and 1.7; 95% CI: 0.7-4.9 respectively). Viral infection was not significantly associated with 'endpoint consolidation', 'other infiltrate,' or 'normal' findings.
Interpretation:
'Endpoint consolidation' was associated with 'any bacterial infection,' specifically pneumococcal infection. Therefore, endpoint consolidation may be a useful surrogate for studies measuring the impact of interventions, such as conjugate vaccines, against bacterial pneumonia.
More Related Videos
 03:22
Author Spotlight: Advancing Pathogen Detection and Disease Assessment in Real-Time Using M-ROSE
Published on: March 1, 2024
 09:17
A Robust Pneumonia Model in Immunocompetent Rodents to Evaluate Antibacterial Efficacy against S. pneumoniae, H. influenzae, K. pneumoniae, P. aeruginosa or A. baumannii
Published on: January 2, 2017
Related Concept Videos
 01:30
Pneumonia III: Complications and Assessment
 01:26
Pulmonary Tuberculosis IV
Several diagnostic approaches are used to detect TB. The conventional method is the Tuberculin Skin Test (TST), also known as the Mantoux test. However, this method has...
 01:31
Pulmonary Tuberculosis III
The first classification is based on the development of the disease, and it includes the following categories:
 01:28
Pulmonary Tuberculosis II
Here is a detailed explanation of its pathophysiology:
Transmission: The process begins when a person inhales droplet nuclei containing M. tuberculosis. These are typically released into the air when an individual with pulmonary or...
 01:14
Atypical Pneumonia
 01:29
Pulmonary Tuberculosis I
Causative Organism
The primary infectious agent causing tuberculosis is Mycobacterium tuberculosis, a slow-growing, acid-fast, aerobic rod that exhibits sensitivity to heat and ultraviolet light. Instances of Mycobacterium bovis and Mycobacterium avium contributing to the development of TB infection are rare.
Mode of...