Triggering secondary to an untreated partially-cut flexor tendon
Related Experiment Video
Updated: Aug 17, 2026

07:32
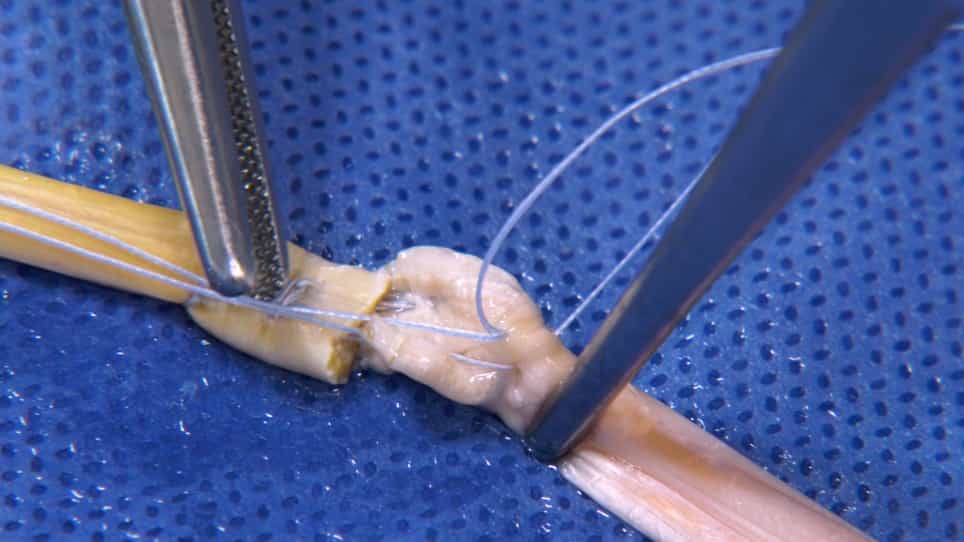
Murine Flexor Tendon Injury and Repair Surgery
Published on: September 19, 2016
1Louisville Hand Surgery, Kentucky.
Journal of Hand Surgery (Edinburgh, Scotland)
|November 1, 1989

Abstract:
A case is reported where a flap cut of the radial slip of the flexor digitorum superficialis triggered on the proximal border of the A2 pulley within a healed intact tendon sheath. Shaving the flap resolved the problem. This illustrates another post-traumatic mechanical cause of triggering after partial division of flexor tendons.

Related Concept Videos
 01:28
Disorders of the Skeletal Muscle
The clinical conditions affecting the skeletal muscle tissue are broadly categorized as musculoskeletal and neuromuscular disorders.
Musculoskeletal disorders
Musculoskeletal disorders involve injuries and conditions affecting the skeletal muscles and associated connective tissues. These disorders can arise from acute biomechanical stresses or chronic overuse and can occur across different age groups. Common injuries include sprains, fractures, and muscular strains, often resulting from...
 01:16
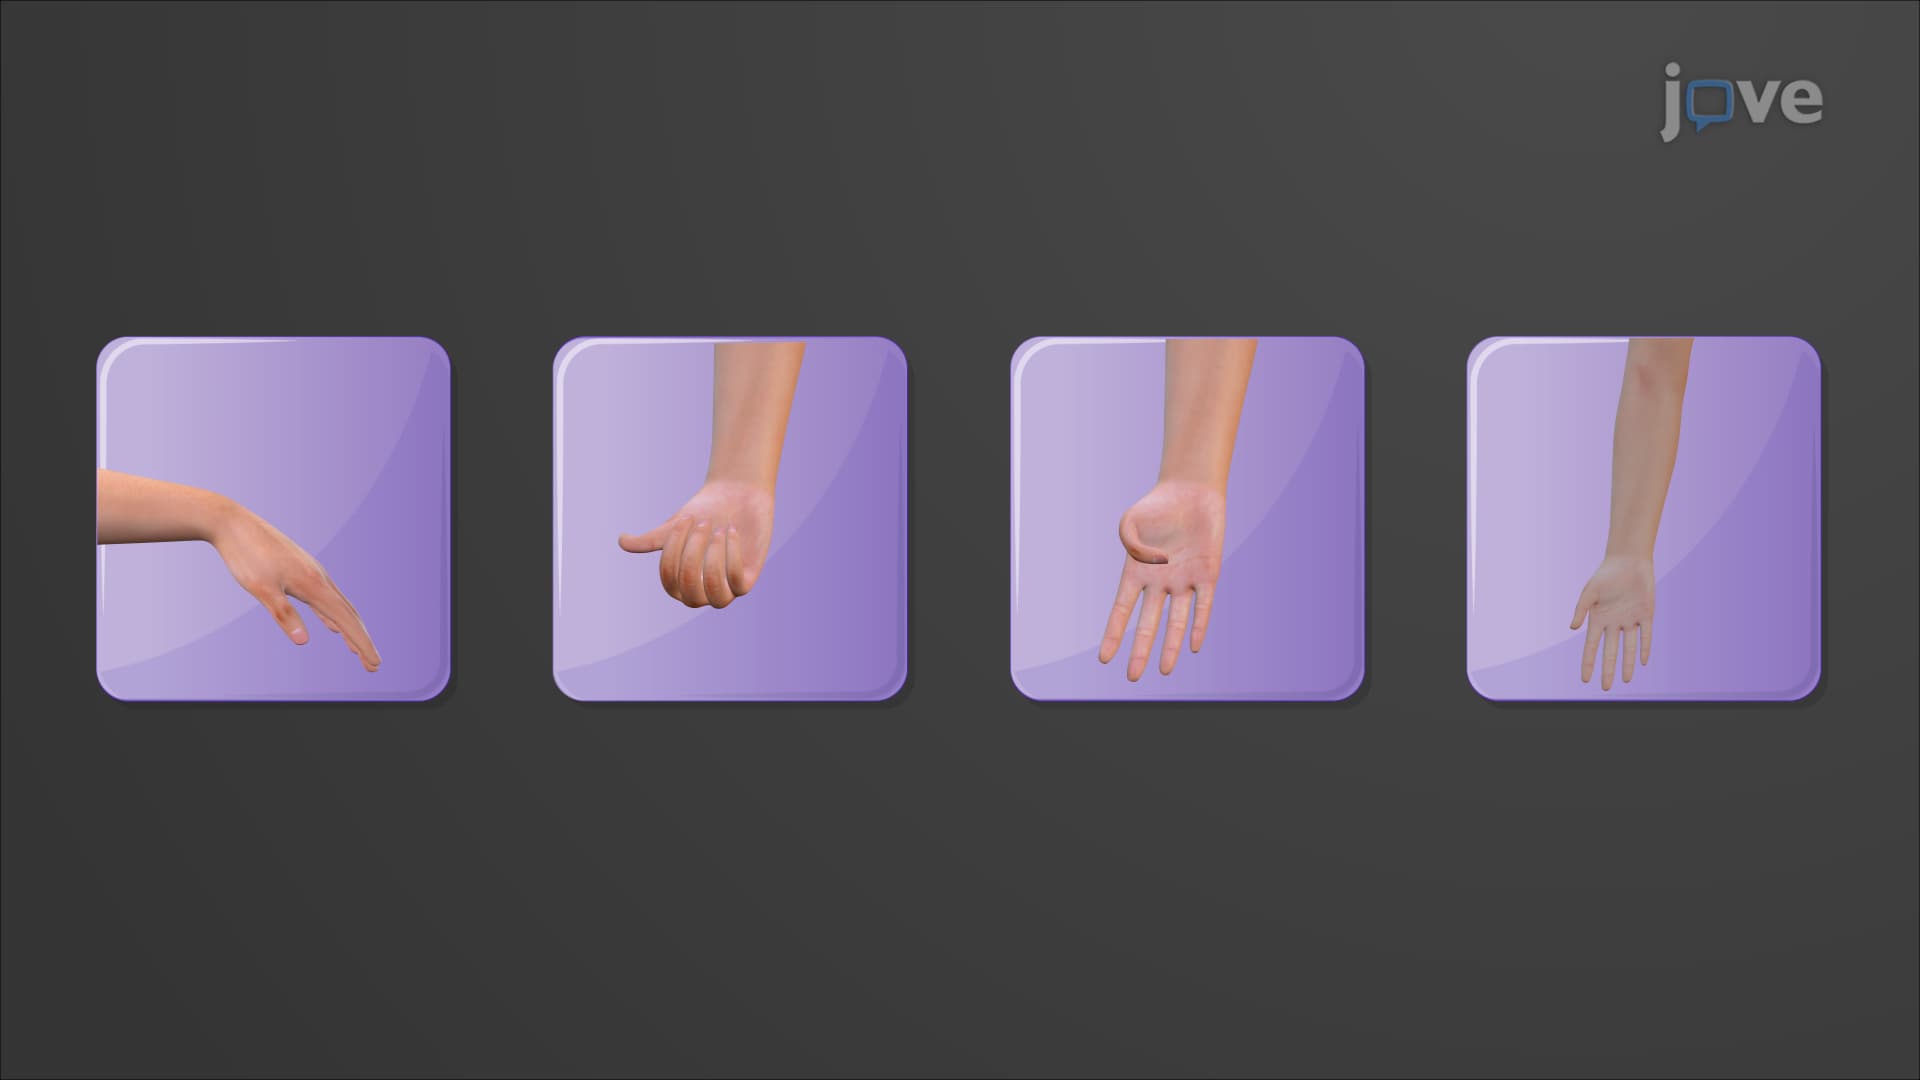
Muscles of the Forearm that Move the Hand and Fingers
The muscles of the forearm that move the wrist, hand, and digits are numerous and diverse. They can be classified into two groups based on their location and function — the anterior and posterior compartment muscles.
Anterior Compartment
The anterior compartment muscles originate from the humerus. They primarily function as flexors and are also known as flexor muscles. They typically insert on the carpals, metacarpals, and phalanges. The superficial layer includes the flexor carpi radialis,...
Anterior Compartment
The anterior compartment muscles originate from the humerus. They primarily function as flexors and are also known as flexor muscles. They typically insert on the carpals, metacarpals, and phalanges. The superficial layer includes the flexor carpi radialis,...
 01:29
Tetanus
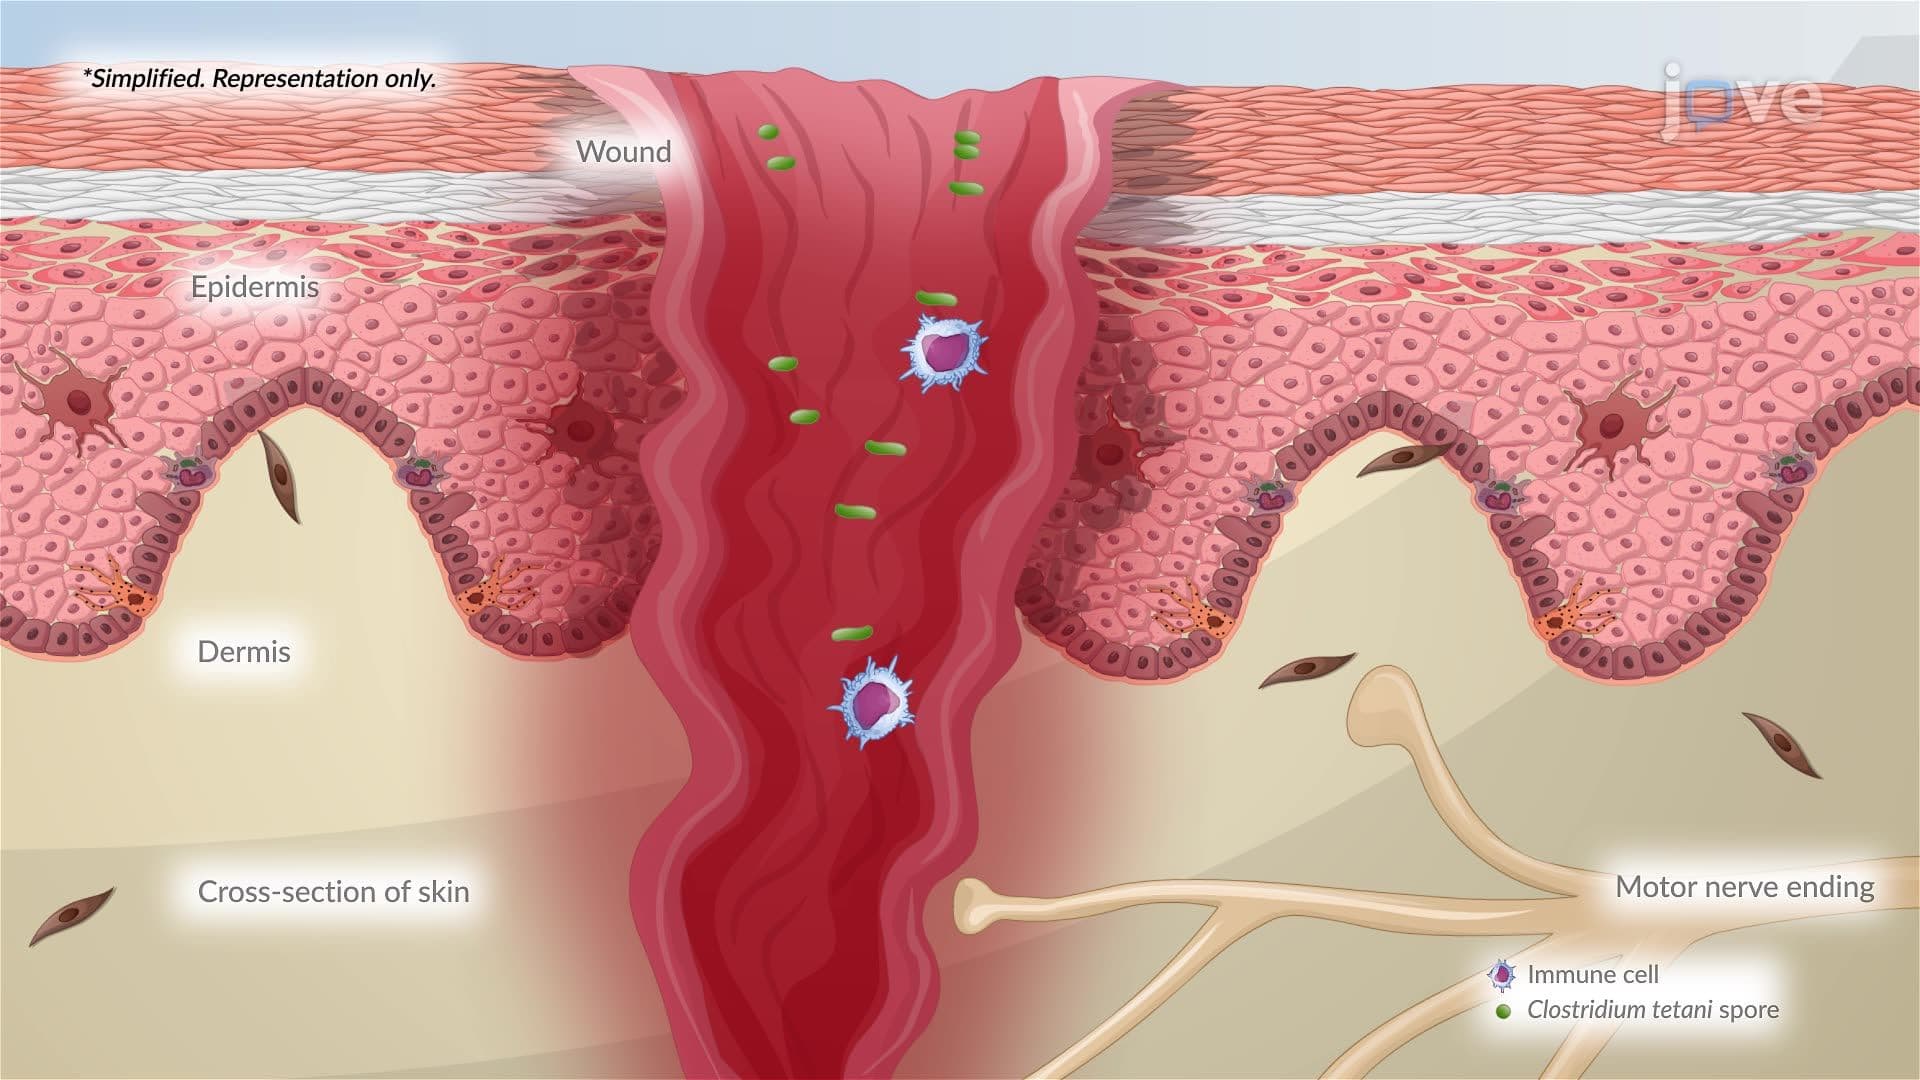
Tetanus is a life-threatening neurological disorder characterized by persistent muscle contractions and spastic paralysis. It is caused by Clostridium tetani, a motile, Gram-positive, rod-shaped, obligate anaerobe. These bacteria produce terminal endospores, giving them a distinctive “lollipop” or “tennis-racket” appearance. They thrive in anaerobic environments, such as those found in deep puncture wounds.Once introduced into the body, the spores germinate into vegetative cells. These cells...
 01:24
Healing II: Complications
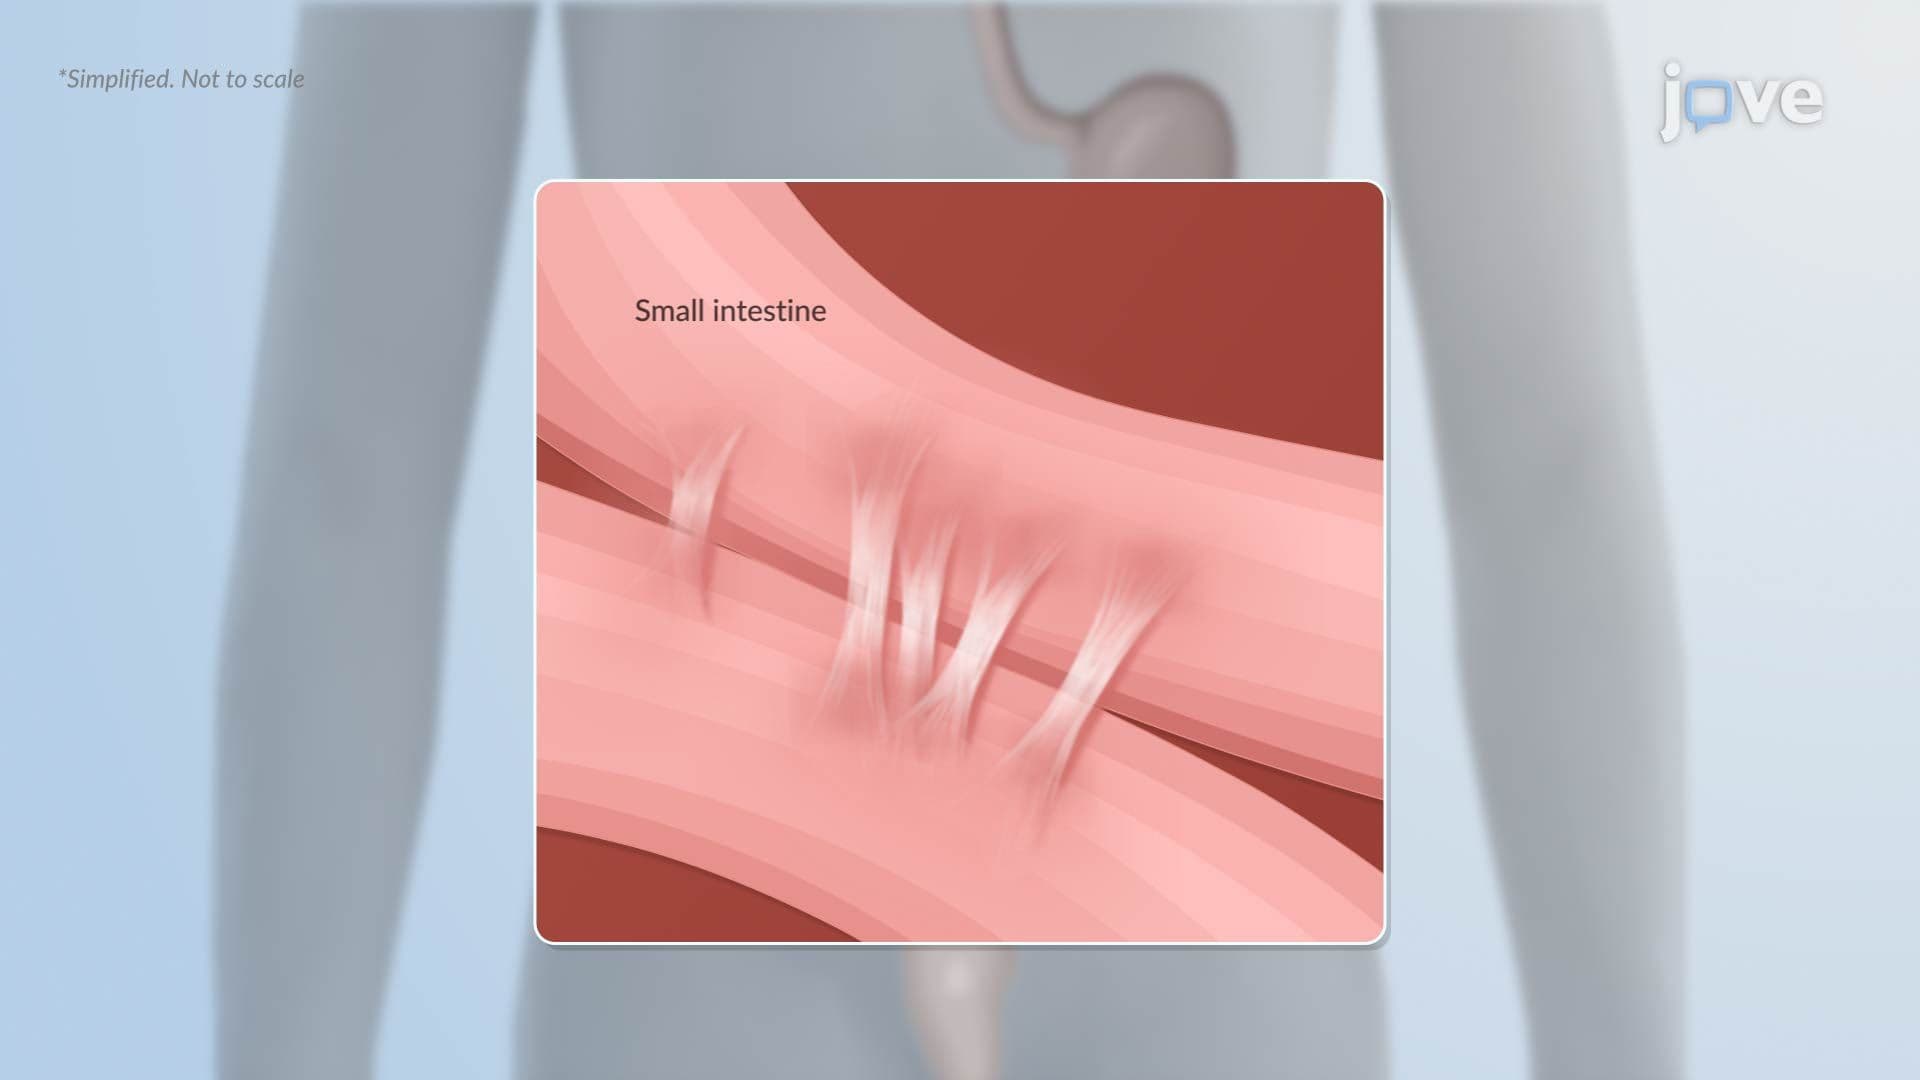
Complications during healing arise when tissue repair is altered by local or systemic factors. These changes involve abnormal collagen deposition, altered biomechanics, and reduced vascular supply, impairing restoration of normal structure and function.Loss of FunctionScar tissue differs significantly from the original tissue it replaces. In the skin, fibrosis lacks adnexal structures such as hair follicles, sebaceous glands, and sweat glands. Their absence reduces tactile sensitivity, impairs...
 01:14
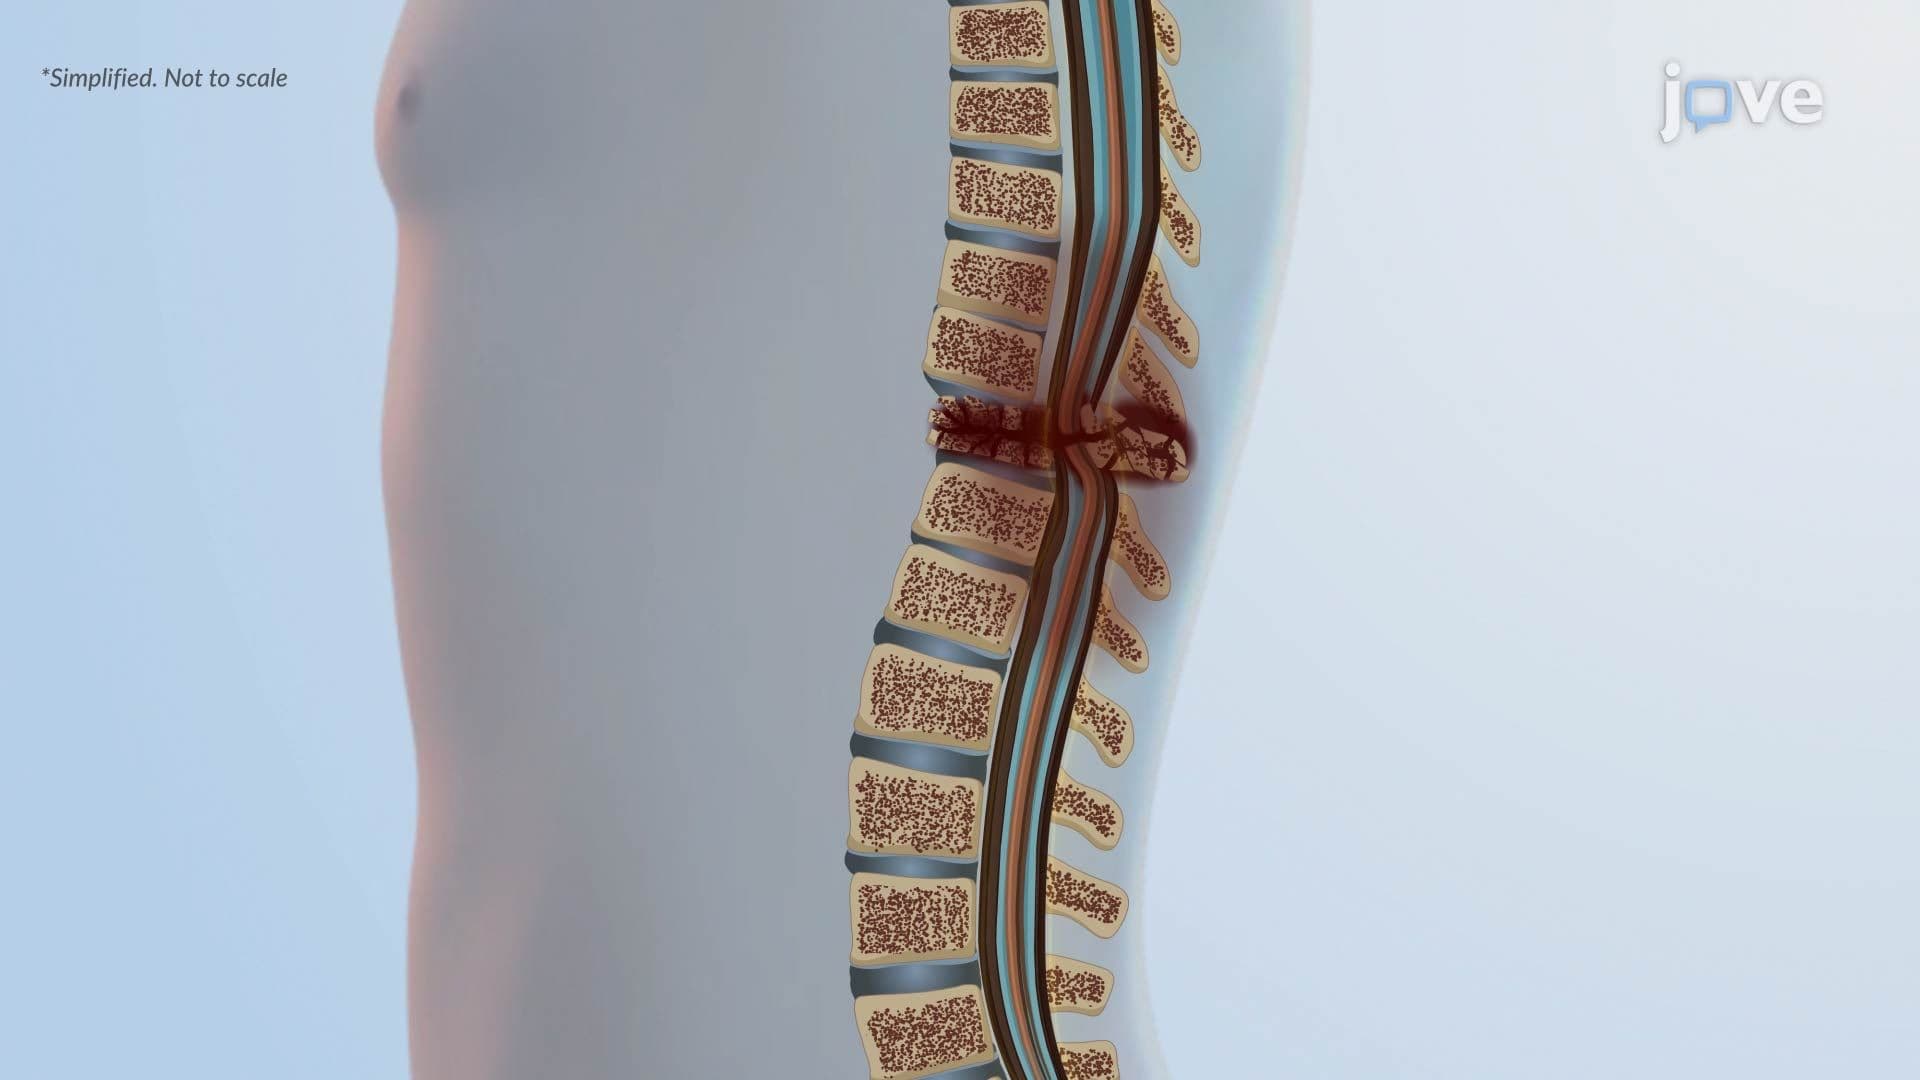
Spinal Cord Injury ll: Pathophysiology
Spinal cord injury progresses through two interconnected phases: primary injury and secondary injury.Primary InjuryPrimary injury happens at the moment of trauma and involves immediate mechanical damage to the spinal cord.Compression happens when broken vertebrae, herniated discs, or accumulating blood (such as a hematoma) press directly against the spinal cord, distorting its normal shape and function. In cases of contusion, the cord is bruised by a blunt force (like penetrating injuries or...
 01:25
Secondary Spinal Cord Injury llI: Pathophysiology
Early Ischemia and Ionic ImbalanceWithin minutes of spinal cord injury, a secondary cascade begins, progressing over hours to weeks. Vascular damage reduces blood flow, causing ischemia and mitochondrial dysfunction. ATP depletion leads to ion pump failure, membrane depolarization, sodium influx, potassium efflux, and water accumulation, resulting in cellular swelling. Increased intracellular calcium further disrupts mitochondria and accelerates cellular injury.Excitotoxicity and Neuronal...