Related Experiment Video
Updated: Sep 3, 2026
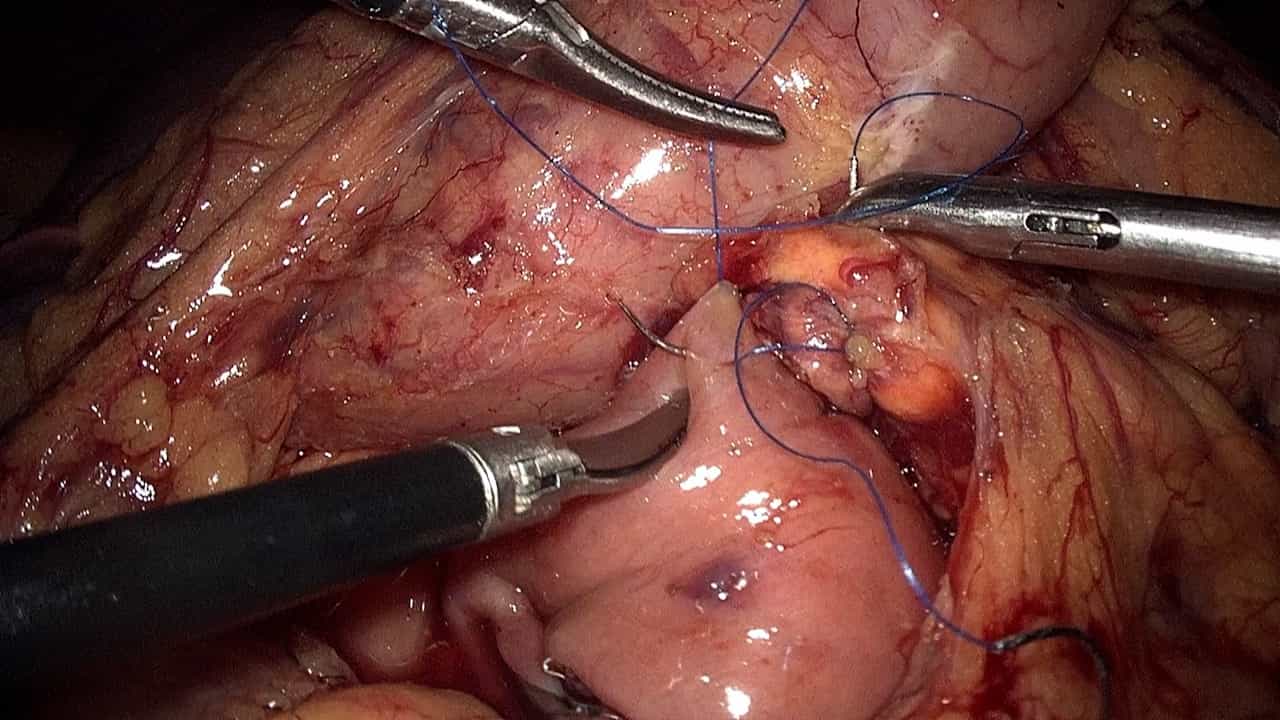

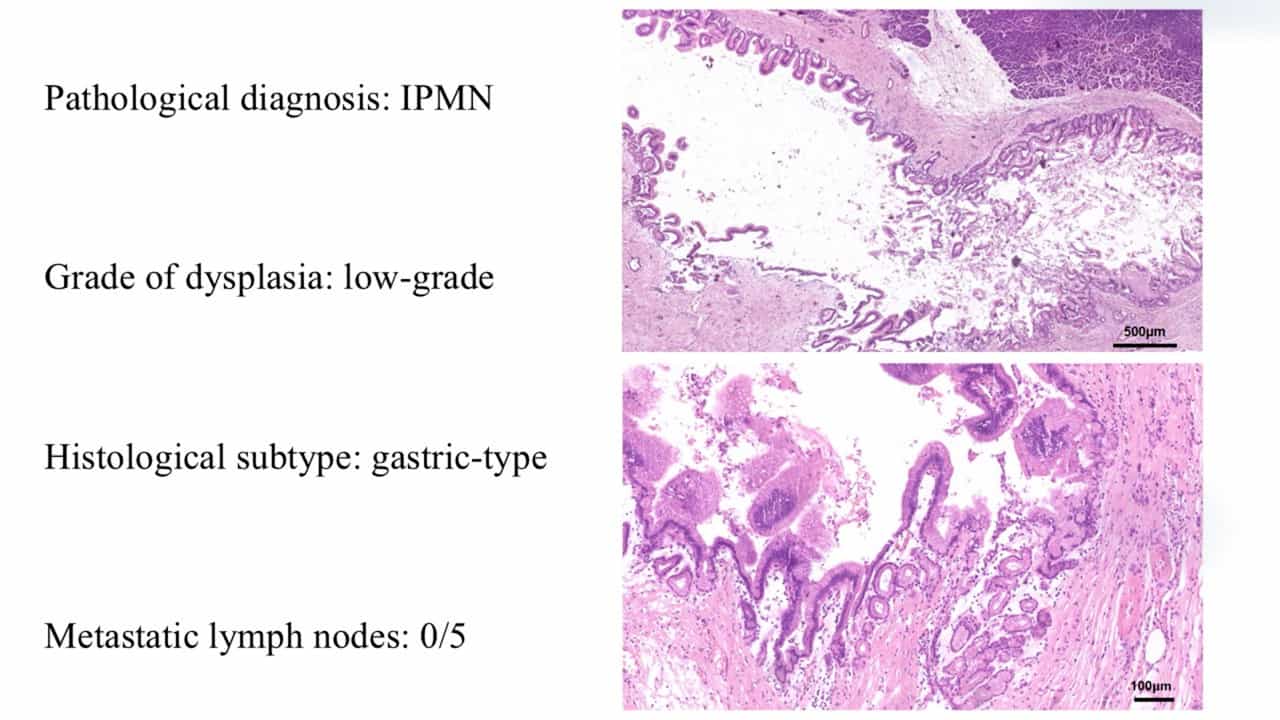
Laparoscopic Duodenum-Preserving Pancreatic Head Resection via Inferior Infracolic Approach: A Surgical Approach for Benign Lesions
Published on: February 9, 2024
[Insidious duodenal injury in a child]

Insights
Pediatric duodenal injuries from blunt abdominal trauma are uncommon but serious. Prompt diagnosis and surgical intervention, such as primary closure or pyloric exclusion, are crucial for better outcomes and reduced mortality.
Area of Science:
- Pediatric Surgery
- Trauma Surgery
- Gastrointestinal Surgery
Context:
- Duodenal injuries are rare in children following blunt abdominal trauma.
- Initial imaging may not reveal duodenal perforation, leading to delayed symptom manifestation.
- Timely diagnosis is critical for effective management and improved patient outcomes.
Purpose:
- To highlight the importance of considering duodenal injury in pediatric blunt abdominal trauma.
- To outline diagnostic challenges and timely management strategies for duodenal perforation.
- To emphasize the correlation between delayed diagnosis and adverse outcomes.
Summary:
- Duodenal perforation in children, though rare, must be suspected in blunt abdominal trauma cases, as imaging can be normal initially.
- Surgical options include primary closure and drainage for early diagnosis (within 24 hours), or more complex procedures like pyloric exclusion, duodenal diverticularization, or pancreaticoduodenectomy for severe injuries.
- Delayed diagnosis significantly increases complication rates, hospitalization duration, and mortality.
Impact:
- Enhances awareness among clinicians regarding a rare but potentially fatal pediatric injury.
- Provides a concise overview of surgical management options based on injury severity.
- Underscores the critical need for prompt diagnosis to mitigate severe complications and reduce mortality in pediatric duodenal trauma.
Abstract:
Duodenal injuries in children are rare. However, we should keep in mind the possibility of duodenal injury in blunt abdominal trauma. Findings on imaging can be normal in spite of duodenal perforation and symptoms may become manifest later after trauma. Duodenal perforation diagnosed within 24 hours can be treated with primary closure and drainage. The safest operative treatment is pyloric exclusion or duodenal diverticularization and gastrojejunostomy or pancreaticoduodenectomy in most serious injuries. Delay in diagnosis is associated with increased complication rate, hospitalization and mortality.
Related Concept Videos
 01:22
Esophageal Perforation-I: Introduction
The location of esophageal perforation can vary, occurring anywhere along the esophagus.
 01:30
Esophageal Strictures-I: Introduction
Etiology
The primary cause of esophageal strictures is long-standing gastroesophageal reflux disease (GERD), accounting for about 70 to 80% of adult cases. Chronic acid reflux can lead to injury and scarring of the esophageal lining, culminating in...
 01:24
Peptic Ulcer Disease II: Pathophysiology
 01:25
Peptic Ulcer Disease III: Clinical Manifestations and Complications
 01:29
Intestinal Obstruction I: Introduction
 01:07
Intestinal Obstruction II: Pathophysiology