Related Experiment Video
Updated: Apr 4, 2026
Pre-Implantation Genetic Testing for Aneuploidy on a Semiconductor Based Next-Generation Sequencing Platform
Published on: August 17, 2022
Prenatal Testing in the Genomic Age: Clinical Outcomes, Quality of Life, and Costs
Anjali J Kaimal1, Mary E Norton, Miriam Kuppermann
1Department of Obstetrics and Gynecology, Massachusetts General Hospital, Boston, Massachusetts; and the Departments of Obstetrics, Gynecology & Reproductive Sciences and Epidemiology & Biostatistics, University of California, San Francisco, San Francisco, California.

Objective:
To use a decision-analytic model to assess a comprehensive set of outcomes of prenatal genetic testing strategies among women of varying ages.
Methods:
We assessed outcomes of six testing strategies incorporating diagnostic testing with chromosomal microarray, multiple marker screening, cell-free DNA screening, and nuchal translucency screening alone, in combination, or in sequence. Clinical outcomes included prenatal detection or birth of a neonate with a significant chromosomal abnormality and diagnostic procedures performed. Other outcomes included maternal quality-adjusted life-years and costs. Sensitivity analyses were conducted to examine the robustness of the findings.
Results:
At all ages assessed, screening strategies starting with multiple marker screening offered the highest detection rate when all chromosomal abnormalities were considered. Incorporating cell-free DNA as an optional secondary screen decreased the number of diagnostic procedures, but also decreased the number of abnormalities diagnosed prenatally, resulting in a similar number of procedures per case diagnosed at age 30 years; the option of secondary cell-free DNA screening becomes more favorable at older ages. Multiple marker screening with optional follow-up diagnostic testing was the most effective (highest quality-adjusted life-years) and least expensive strategy at ages 20-38 years. At age 40 years or older, cell-free DNA screening was optimal with an incremental cost-effectiveness ratio of $73,154 per quality-adjusted life-year.
Conclusion:
When considering all detectable chromosome problems as well as patient preferences and baseline risks, multiple marker screening with the option of diagnostic testing for screen-positive results is the optimal strategy for most women. At age 40 years and older, cell-free DNA as a primary screen becomes optimal and is cost-effective.
Level Of Evidence:
II.

Related Concept Videos
 02:02
Genomics
 01:29
Pharmacogenomics: Identification of New Drug Targets
 03:00
Next-generation Sequencing
Next-Generation Sequencing Methods
Although all next-generation methods use different technologies, they all share a set of standard features....
 01:29
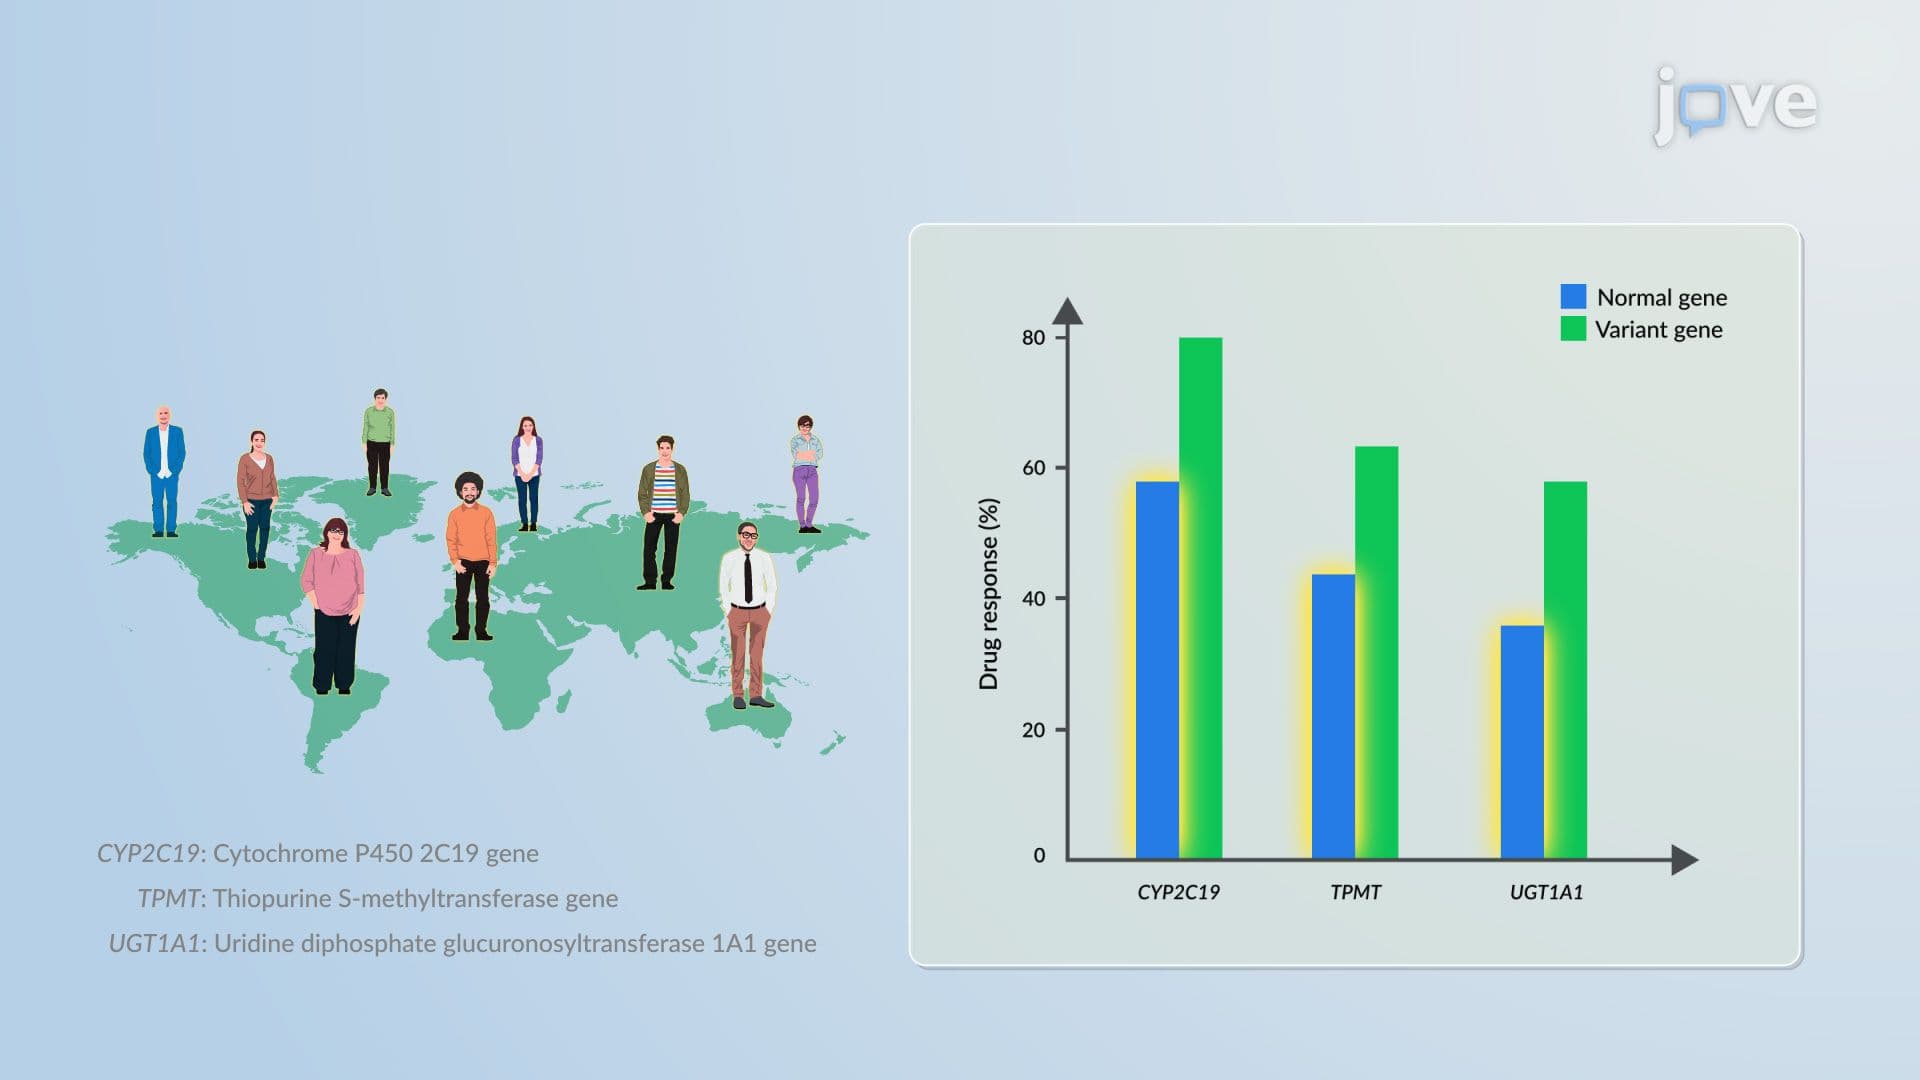
Pharmacogenetics and Pharmacogenomics: Overview
 01:59
CRISPR
 01:28
Human Genetics
The complex relationship between genetics and psychology is observable through common biological components such...