Related Experiment Video
Updated: Apr 4, 2026
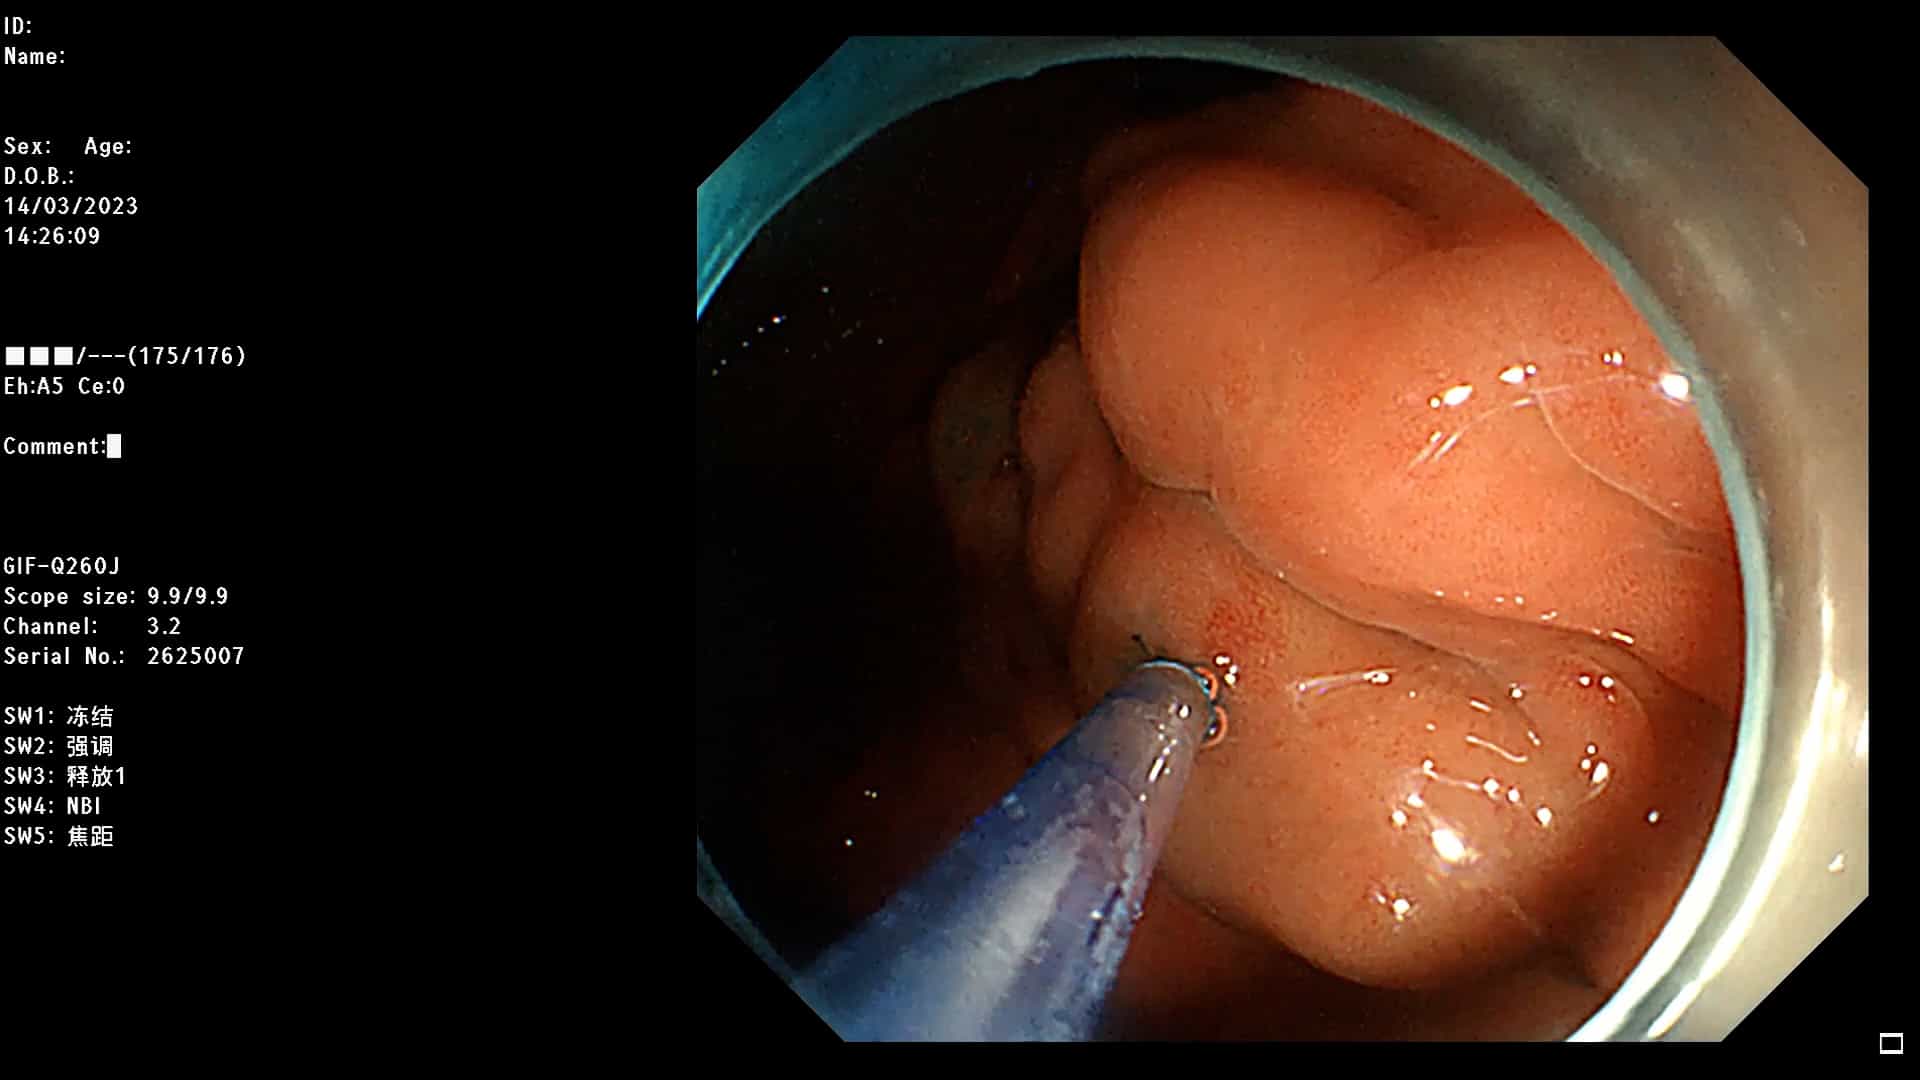
Endoscopic Injection Sclerotherapy Assisted by Cyanoacrylate and Clips for Gastroesophageal Varices
Published on: June 13, 2025
Facility- and Patient-Level Factors Associated with Esophageal Variceal Screening in the USA
Jennifer A Flemming1, Varun Saxena2, Hui Shen2,3
1Departments of Medicine and Public Health Sciences, Queen's University, 166 Brock Street, S4-012, Kingston, ON, K7L 5M2, Canada. flemmij@hdh.kari.net.

Background And Aim:
The American Association for the Study of Liver Disease (AASLD) recommends screening for esophageal varices (EV) by esophagoduodenoscopy (EGD) in patients with cirrhosis to guide decisions regarding primary prophylaxis for EV hemorrhage. We aimed to identify patient and facility factors associated with EV screening in veterans with hepatitis C (HCV)-associated cirrhosis.
Methods:
This was a population-based cohort study. Veterans with HCV and newly diagnosed cirrhosis between 1/1/2004 and 12/31/2005 and followed until 12/31/2011 were included. The primary outcome was receipt of EGD within 1 year of cirrhosis diagnosis. Patient- and facility-level factors associated with EV screening were determined.
Results:
A total of 4230 patients with HCV cirrhosis were identified. During median follow-up of 6.1 years (IQR: 4.0-8.0), 21.5 % developed a decompensating event, and 38.3 % died. Fifty-four percent received an EGD, and 33.8 % had an EGD within guidelines. Median time from cirrhosis diagnosis to EGD was 72 days (IQR: 12-176). Factors independently associated with receipt of EV screening were a decompensation event (OR 1.16, CI 1.01-1.32) and gastroenterology/hepatology clinic access (OR 2.1, CI 1.73-2.46), whereas cardiovascular (OR 0.81, CI 0.69-0.95), mental health (OR 0.79, CI 0.68-0.91), and respiratory (OR 0.85, CI 0.72-0.99) comorbidities were associated with reduced likelihood of EV screening.
Conclusion:
EV screening per AASLD guidelines occurs in only one-third of patients. This missed opportunity was strongly associated with access to gastroenterology/hepatology specialty care. Additionally, providers may be relying on clinical cues (i.e., decompensation) to prompt referral for endoscopy suggesting education to improve compliance with guidelines is needed.
More Related Videos

Related Concept Videos
 01:28
Esophageal Varices-II: Clinical Features and Management
In the initial assessment, a thorough review of the patient's medical history is vital to identify risk factors such as liver disease, alcohol...
 01:24
Esophageal Varices-I: Introduction
 01:26
Esophageal Strictures-II: Clinical Features and Management
Healthcare providers should gather a comprehensive medical history and conduct a physical examination for diagnosis. If esophageal stricture is...
 01:21
Barrett Esophagus-I: Introduction
This constant acid exposure transforms the esophagus's pink mucosal lining (stratified squamous epithelium) into a type of lining more...
 01:21
Barrett Esophagus-II: Clinical Manifestations and Management
To diagnose Barrett's esophagus, healthcare providers often recommend an endoscopy for those showing symptoms of acid reflux. The procedure...
 01:30
Esophageal Strictures-I: Introduction
Etiology
The primary cause of esophageal strictures is long-standing gastroesophageal reflux disease (GERD), accounting for about 70 to 80% of adult cases. Chronic acid reflux can lead to injury and scarring of the esophageal lining, culminating in...