Related Experiment Video
Updated: Aug 13, 2026
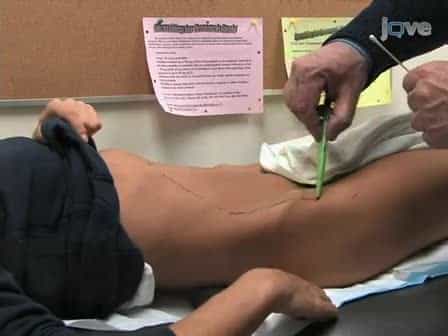

Demonstration of Cutaneous Allodynia in Association with Chronic Pelvic Pain
Published on: June 23, 2009
Vulvodynia. A multifactorial clinical problem
1Department of Dermatology, Grady Memorial Hospital, Emory University School of Medicine, Atlanta.

Abstract:
Symptomatic vulvar burning (vulvodynia) in the absence of abnormal physical findings was long thought to be an unusual psychosomatic gynecologic problem. Within the past decade, however, a number of investigators began to study patients with this frustrating problem. Initial physician insistence on a major role for psychological factors has gradually given way to sophisticated searches for evidence of persistent infectious agents, especially human papillomavirus and Candida. Gynecologists searching for causes and surgical relief of vulvodynia have even reevaluated elements of vulvar anatomy. The purpose of this article is to introduce dermatologists to current perspectives on vulvodynia in the context of the clinical experience of the author, who has been actively involved in the multidisciplinary investigation of this problem since its recognition in the early 1980s. To date, the following five sign-symptom complexes have been identified by the author and recognized by other vulvodynia investigators: (1) vulvar dermatoses, (2) cyclic vulvitis, (3) vulvar papillomatosis, (4) vulvar vestibulitis, and (5) essential vulvodynia. A given patient's complaint may be primarily associated with one of these factors, but it is not unusual to see others develop simultaneously or sequentially. Remission or exacerbation of symptoms may occur when treatment for one condition affects the onset of another. It is evident that vulvodynia is a complex diagnosis and that recognition of multiple factors is important to appropriate patient evaluation and management.

Related Concept Videos
 01:24
Disorders of the Female Reproductive System
 01:30
Irritable Bowel Syndrome II: Clinical Features and Diagnostic Evaluation
Irritable Bowel Syndrome (IBS) is classified into subtypes based on the predominant bowel habits as determined by the Bristol Stool Form Scale (BSFS). The subtypes are:
 01:26
Urinary Tract Calculi II: Pathophysiology and Clinical Manifestations
 01:23
Genital Herpes
 01:20
Candidiasis
 01:18
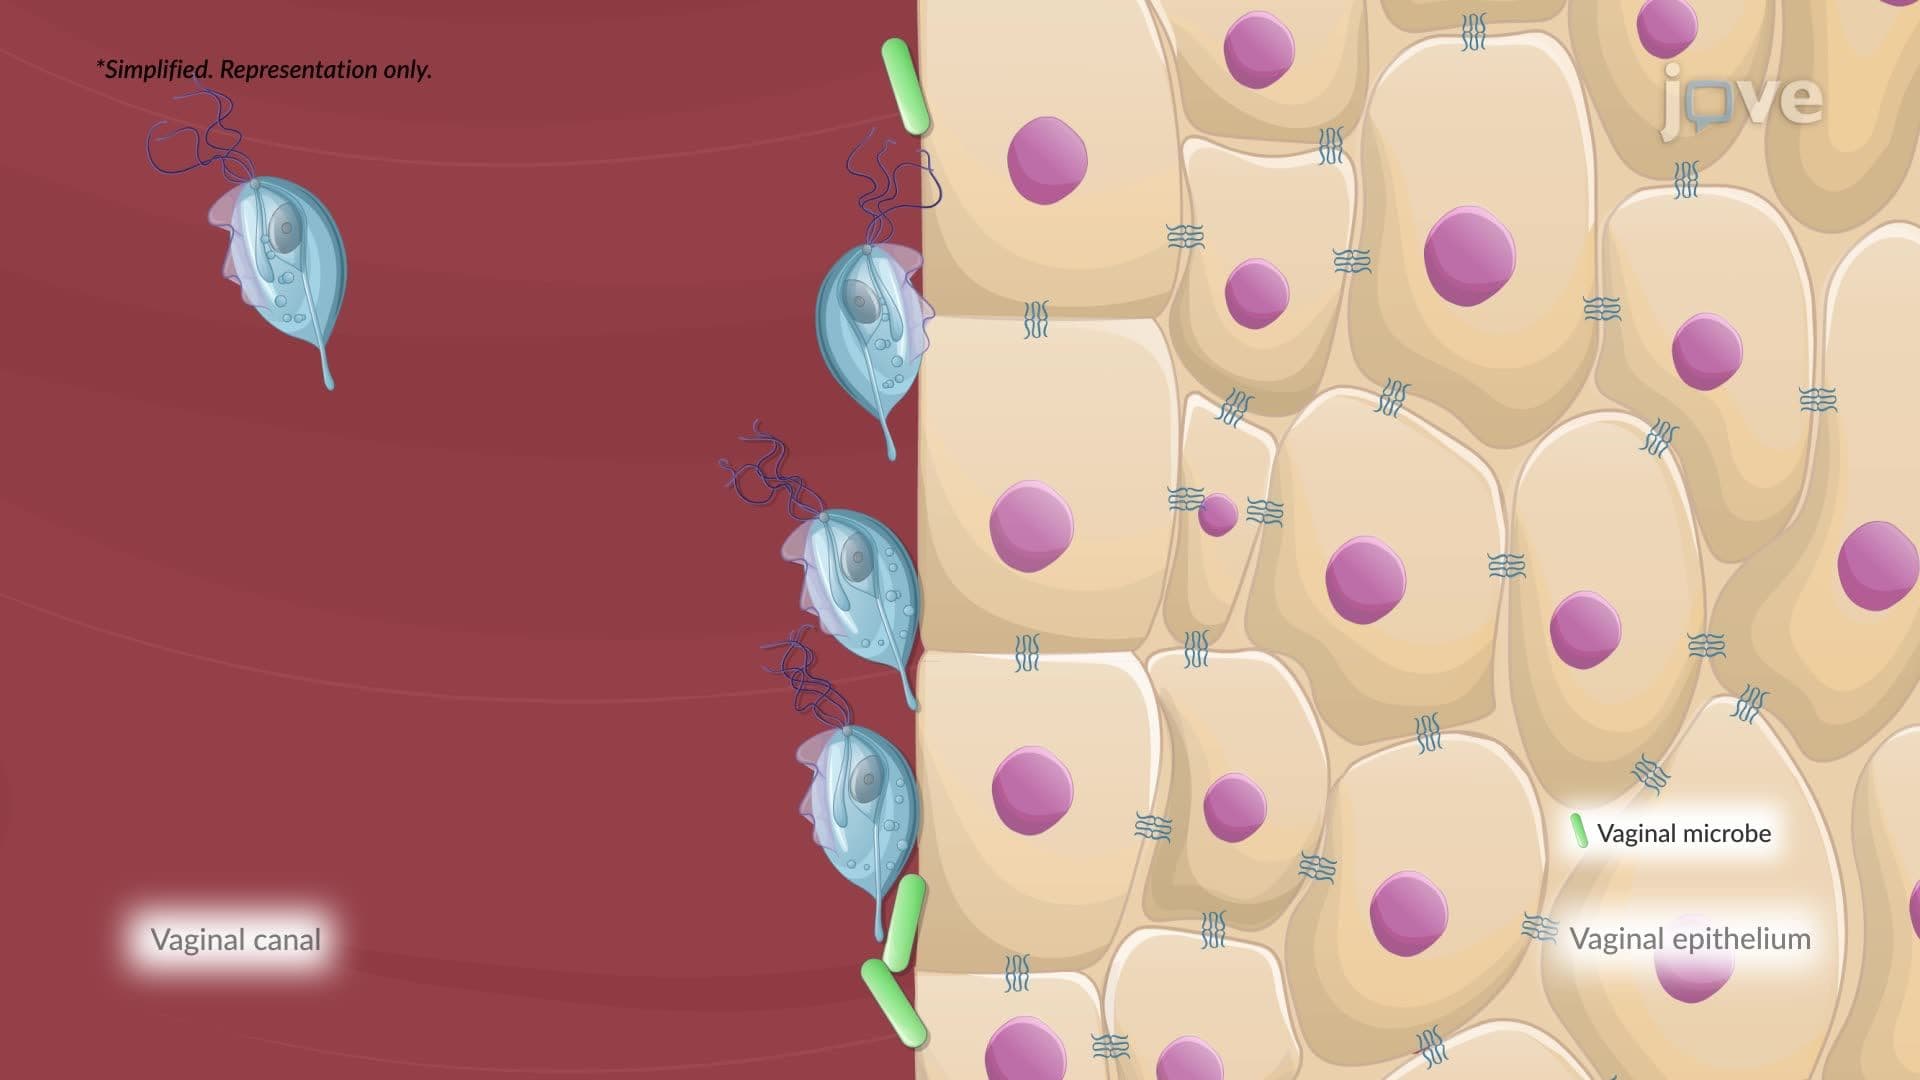
Trichomoniasis