Related Experiment Video
Updated: Apr 1, 2026
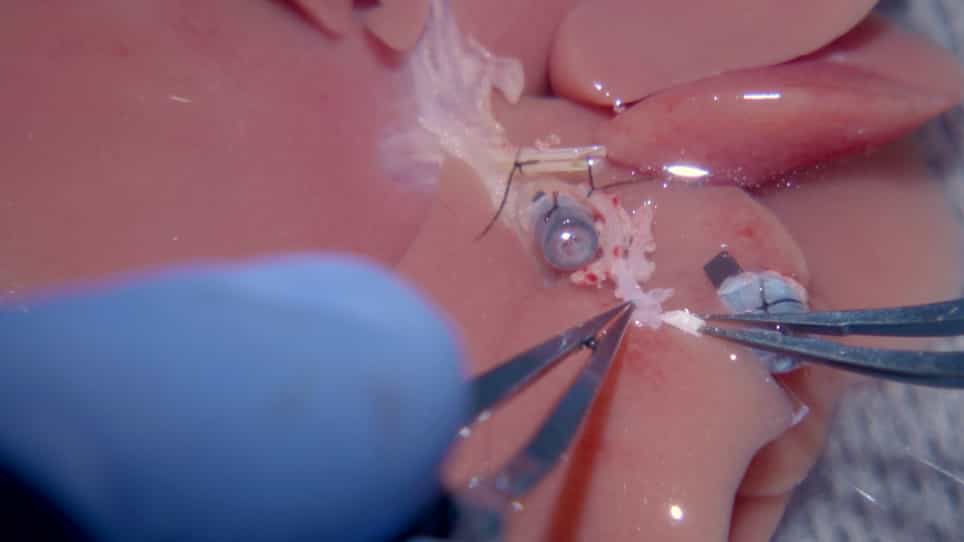

Reduced Complications after Arterial Reconnection in a Rat Model of Orthotopic Liver Transplantation
Published on: November 7, 2020
Everolimus in de novo liver transplant recipients: a systematic review
Cheng-Yong Tang1, Ai Shen, Xu-Fu Wei
1Department of Hepatobiliary Surgery, First Affiliated Hospital of Chongqing Medical University, Chongqing 404100, China. wzjtcy@126.com.

Background:
Everolimus has no nephrotoxicity and is used to treat patients with post-liver transplant chronic renal insufficiency. The present systematic review was to evaluate the efficacy and safety of everolimus in de novo liver transplant patients.
Data Sources:
Randomized controlled trials comparing everolimus for de novo liver transplant in PubMed, the Cochrane Library, and ScienceDirect published up to March 31, 2014 were searched by two independent reviewers. Mean differences and 95% confidence interval (95% CI) for renal function, relative risk (RR) and 95% CI for treated biopsy-proven acute rejection (tBPAR), graft loss, death, neoplasms/tumor recurrence, and adverse events were collected. Meta-analyses were performed with RevMan version 5.10.
Results:
A total of four randomized controlled trials covering 1119 cases were included. The meta-analyses revealed that compared with standard exposure of calcineurin inhibitors (CNIs), everolimus combined with reduced CNIs improved creatinine clearance (calculated with the Cockcroft-Gault formula) by 5.13 mL/min at one year (95% CI: 0.42-9.84; P=0.03), and decreased tBPAR (RR: 0.56; 95% CI: 0.35-0.90; P=0.02). Everolimus initiation with CNIs elimination improved glomerular filtration rate (GFR, measured with the modification of diet in renal disease formula) of 10.42 mL/min/1.73 m2 (95% CI: 3.44-17.41; P<0.01) one year after treatment, but increased tBPAR (RR: 1.71; 95% CI: 1.15-2.53; P<0.01). Everolimus decreased the risk of neoplasms/tumor recurrence after liver transplant (RR: 0.60; 95% CI: 0.34-1.03; P=0.06), but was associated with greater risk of adverse events which resulted in drug discontinuation (RR: 1.98; 95% CI: 1.49-2.64; P<0.01).
Conclusions:
Early introduction of everolimus combined with low-dose or no CNI in de novo liver transplant significantly improves renal function one year post treatment. Everolimus combined with low-dose CNI decreases the risk of tBPAR one year after liver transplant, but everolimus administered without CNIs increases tBPAR.
More Related Videos


Related Concept Videos
 01:28
Kidney Transplant I: Introduction
 01:16
Kidney Transplant III: Nursing Management
 01:26
Extracorporeal Removal of Drugs: Continuous Renal Replacement Therapy
 01:08
Effect of Hepatic Disease on Pharmacokinetics: Dose Adjustments Due to Hepatic Impairment
 01:24
Tissue Transplantation
The Biology of Tissue Transplantation
The biology of tissue transplantation hinges on the Major Histocompatibility Complex (MHC) molecules. These molecules...
 01:22
Effect of Hepatic Disease on Pharmacokinetics: Pathophysiologic Assessment and Liver Function Test