Related Experiment Video
Updated: Jul 21, 2026


Minimally Invasive Endoscopic Intracerebral Hemorrhage Evacuation
Published on: October 15, 2021
Influence of site on course of intracerebral hemorrhage
D B Hier1, D J Babcock1, M A Foulkes2
1University of Illinois at Chicago, Chicago, IL.

The influence of site of hemorrhage on presentation, clinical profile, hospital course, and outcome was examined in 225 patients with intracerebral hemorrhage in the NINDS Stroke Data Bank. Mode of presentation differed by hemorrhage site (coma at onset was most typical of pontine hemorrhage and headache with vomiting was most typical of cerebellar hemorrhage, whereas onset of focal deficit sometimes with headache was typical of lobar and and basal ganglionic hemorrhages). Distinct clinical profiles were found for cerebellar (ataxia, drowsiness, and horizontal gaze paresis), pontine (quadriparesis, coma, vertical and horizontal gaze paresis), and caudate hemorrhages (drowsiness and hemiparesis). Putaminal, thalamic, and lobar hemorrhages presented similarly with hemiparesis, sensory loss, and higher cortical function deficits. However, thalamic hemorrhages had more sensory loss, putaminal hemorrhages had more weakness, and lobar hemorrhages had more higher cortical function deficits. Hemorrhage volume was greatest for the lobar and putaminal hemorrhages and smallest for the pontine and cerebellar hemorrhages. Clot evacuations were performed for 28.9% of the lobar hemorrhages and 48.2% of the cerebellar hemorrhages. Few basal ganglionic hemorrhages or pontine hemorrhages had clot evacuations. Thirty-day survival was lowest for caudate hemorrhage (46.2%) and highest for cerebellar hemorrhage (81.5%). Hydrocephalus, intraventricular blood, larger size, and mass effect were adverse predictors of survival at most but not all hemorrhage sites. History of hypertension was the most prevalent risk factor for hemorrhage (64.0% of the patients). Other risk factors for hemorrhage included anticoagulants, platelet antiaggregating drugs, aneurysms, arteriovenous malformations, pregnancy, alcohol use, amyloid angiopathy, thrombocytopenia, renal and liver failure, and cocaine use. The most common medical complications were pneumonia (15.5%), urinary tract infection (15.0%), arrhythmias (8.4%), and seizures (8.0%).
The influence of site of hemorrhage on presentation, clinical profile, hospital course, and outcome was examined in 225 patients with intracerebral hemorrhage in the NINDS Stroke Data Bank. Mode of presentation differed by hemorrhage site (coma at onset was most typical of pontine hemorrhage and headache with vomiting was most typical of cerebellar hemorrhage, whereas onset of focal deficit sometimes with headache was typical of lobar and and basal ganglionic hemorrhages). Distinct clinical profiles were found for cerebellar (ataxia, drowsiness, and horizontal gaze paresis), pontine (quadriparesis, coma, vertical and horizontal gaze paresis), and caudate hemorrhages (drowsiness and hemiparesis). Putaminal, thalamic, and lobar hemorrhages presented similarly with hemiparesis, sensory loss, and higher cortical function deficits. However, thalamic hemorrhages had more sensory loss, putaminal hemorrhages had more weakness, and lobar hemorrhages had more higher cortical function deficits. Hemorrhage volume was greatest for the lobar and putaminal hemorrhages and smallest for the pontine and cerebellar hemorrhages. Clot evacuations were performed for 28.9% of the lobar hemorrhages and 48.2% of the cerebellar hemorrhages. Few basal ganglionic hemorrhages or pontine hemorrhages had clot evacuations. Thirty-day survival was lowest for caudate hemorrhage (46.2%) and highest for cerebellar hemorrhage (81.5%). Hydrocephalus, intraventricular blood, larger size, and mass effect were adverse predictors of survival at most but not all hemorrhage sites. History of hypertension was the most prevalent risk factor for hemorrhage (64.0% of the patients). Other risk factors for hemorrhage included anticoagulants, platelet antiaggregating drugs, aneurysms, arteriovenous malformations, pregnancy, alcohol use, amyloid angiopathy, thrombocytopenia, renal and liver failure, and cocaine use. The most common medical complications were pneumonia (15.5%), urinary tract infection (15.0%), arrhythmias (8.4%), and seizures (8.0%).


Related Concept Videos
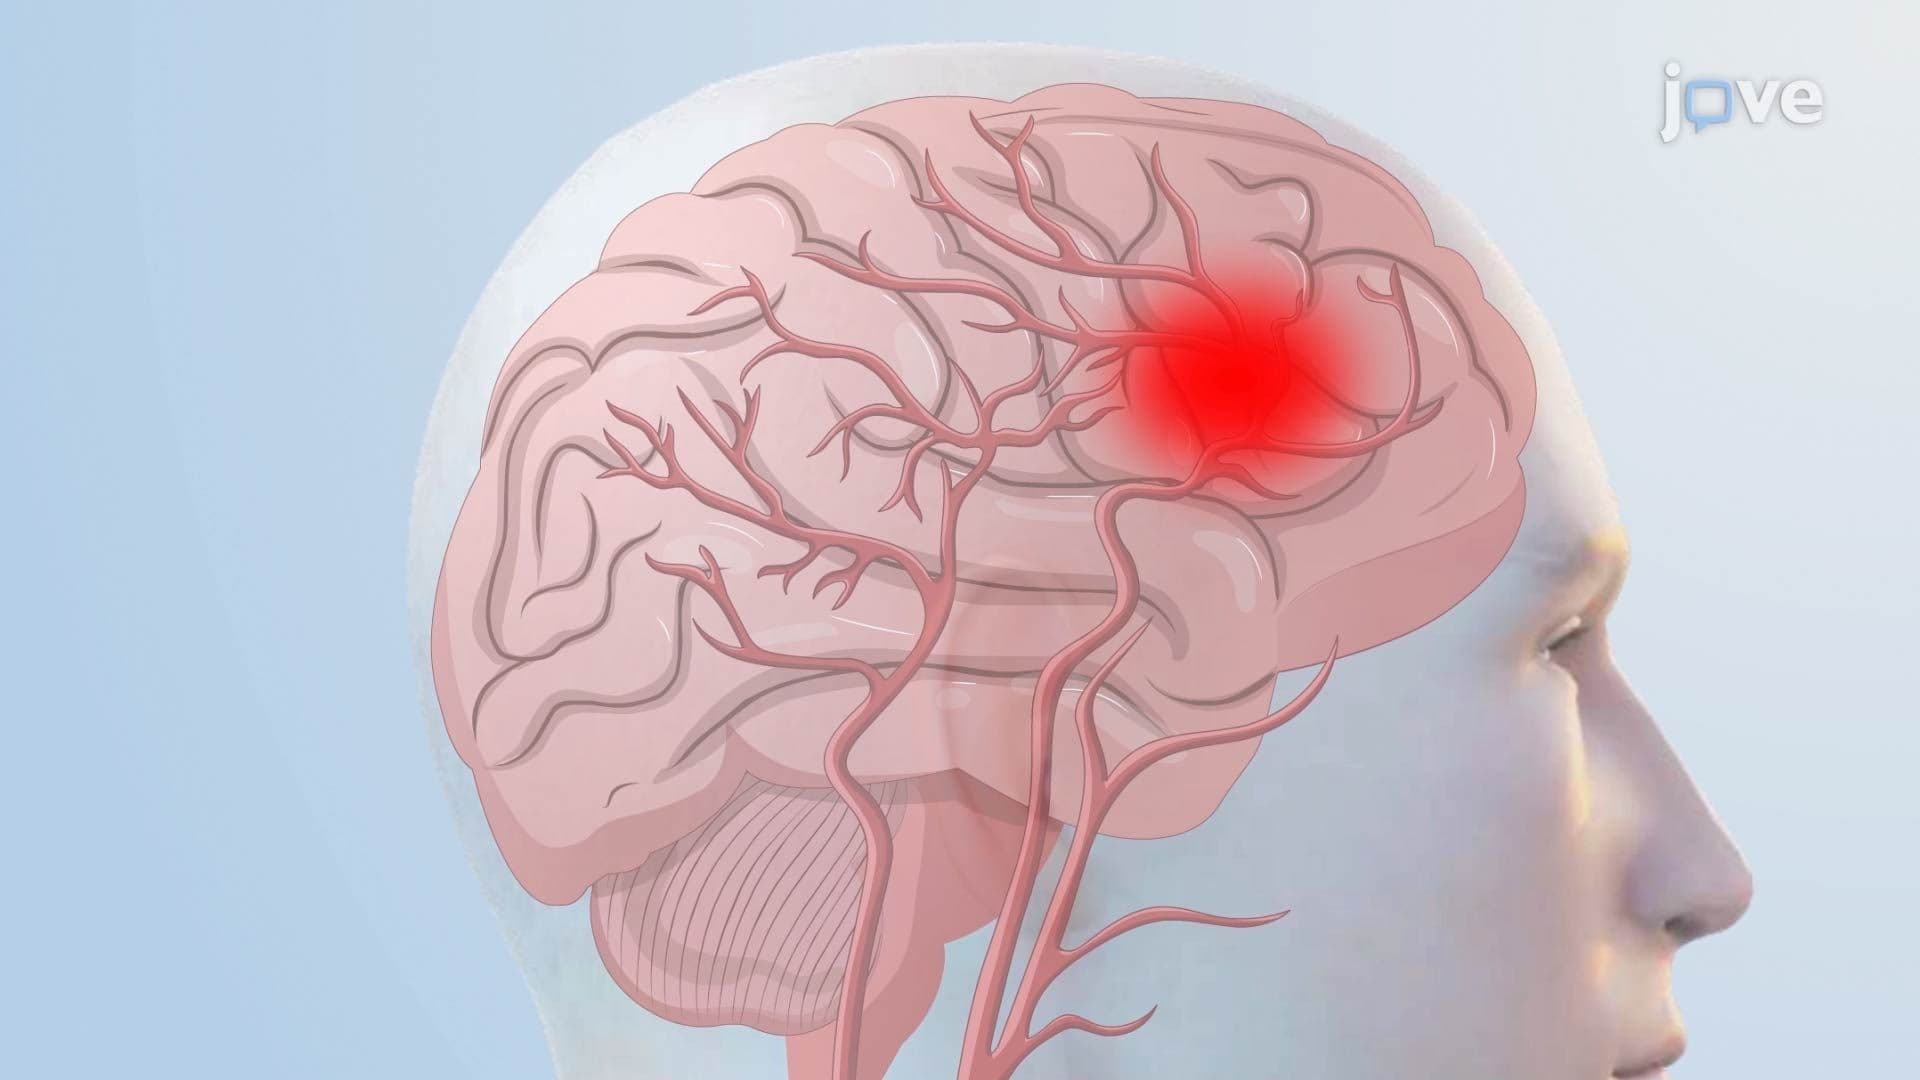 01:29
Stroke: Introduction and Types
 01:15
Ischemic Stroke ll: Pathophysiology
 01:17
Hemorrhagic Stroke l: Introduction
 01:29
Hemorrhagic Stroke ll: Pathophysiology
 01:29
Increased Intracranial Pressure ll: Pathophysiology
 01:22
Cerebral Edema ll: Pathophysiology