Related Experiment Video
Updated: Jul 27, 2026


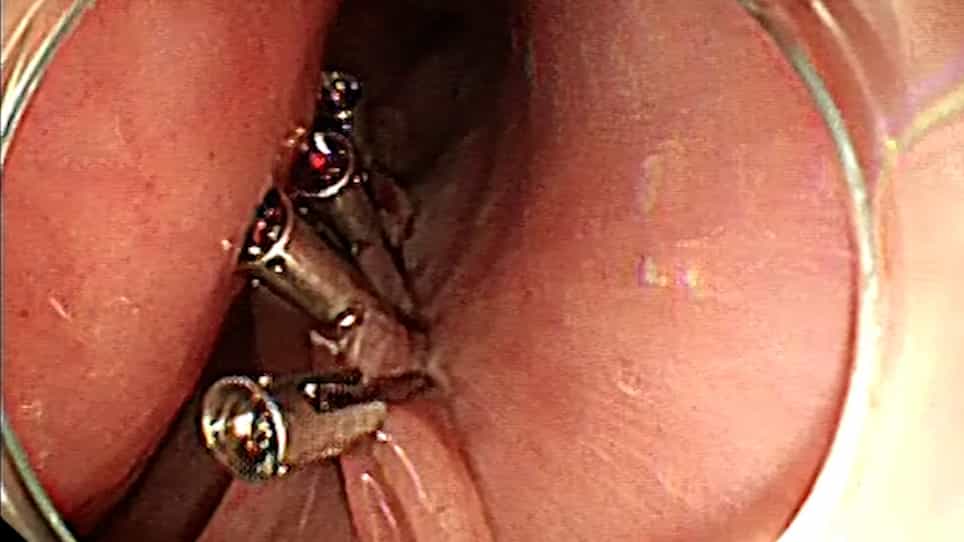
ADSC-sheet Transplantation to Prevent Stricture after Extended Esophageal Endoscopic Submucosal Dissection
Published on: February 10, 2017
Prevention of esophageal stricture after endoscopic submucosal dissection: a systematic review and meta-analysis
J F Oliveira1, E G H Moura2, W M Bernardo3,4
1Gastrointestinal Endoscopy Unit, University of São Paulo Medical School, São Paulo, Brazil. jfoliveira1@gmail.com.

Background:
Endoscopic submucosal dissection (ESD) of extensive superficial cancers of the esophagus may progress with high rates of postoperative stenosis, resulting in significantly decreased quality of life. Several therapies are performed to prevent this, but have not yet been compared in a systematic review.
Methods:
A systematic review of the literature and meta-analysis were performed using the MEDLINE, Embase, Cochrane, LILACS, Scopus, and CINAHL databases. Clinical trials and observational studies were searched from March 2014 to February 2015. Search terms included: endoscopy, ESD, esophageal stenosis, and esophageal stricture. Three retrospective and four prospective (three randomized) cohort studies were selected and involved 249 patients with superficial esophageal neoplasia who underwent ESD, at least two-thirds of the circumference. We grouped trials comparing different techniques to prevent esophagus stenosis post-ESD.
Results:
We conducted different meta-analyses on randomized clinical trials (RCT), non-RCT, and global analysis. In RCT (three studies, n = 85), the preventive therapy decreased the risk of stenosis (risk difference = -0.36, 95 % CI -0.55 to -0.18, P = 0.0001). Two studies (one randomized and one non-randomized, n = 55) showed that preventative therapy lowered the average number of endoscopy dilatations (mean difference = -8.57, 95 % CI -13.88 to -3.25, P < 0.002). There were no significant differences in the three RCT studies (n = 85) in complication rates between patients with preventative therapy and those without (risk difference = 0.02, 95 % CI -0.09 to 0.14, P = 0.68).
Conclusions:
The use of preventive therapy after extensive ESD of the esophagus reduces the risk of stenosis and the number of endoscopic dilatations for resolution of stenosis without increasing the number of complications.
More Related Videos

Related Concept Videos
 01:29
Gastroesophageal Reflux Disease II: Clinical Features and Management
Clinical Manifestations
GERD presents itself in a multitude of ways, with symptoms varying from person to person. The hallmark symptoms are...
 01:21
Barrett Esophagus-I: Introduction
This constant acid exposure transforms the esophagus's pink mucosal lining (stratified squamous epithelium) into a type of lining more similar...
 01:21
Barrett Esophagus-II: Clinical Manifestations and Management
To diagnose Barrett's esophagus, healthcare providers often recommend an endoscopy for those showing symptoms of acid reflux. The procedure entails...
 01:30
Esophageal Strictures-I: Introduction
Etiology
The primary cause of esophageal strictures is long-standing gastroesophageal reflux disease (GERD), accounting for about 70 to 80% of adult cases. Chronic acid reflux can lead to injury and scarring of the esophageal lining, culminating in...
 01:26
Esophageal Strictures-II: Clinical Features and Management
Healthcare providers should gather a comprehensive medical history and conduct a physical examination for diagnosis. If esophageal stricture is...
 01:29
Endoscopic Procedures I: Esophagogastroduodenoscopy
During an EGD, the endoscope can be used to: