Related Experiment Video
Updated: Sep 16, 2026
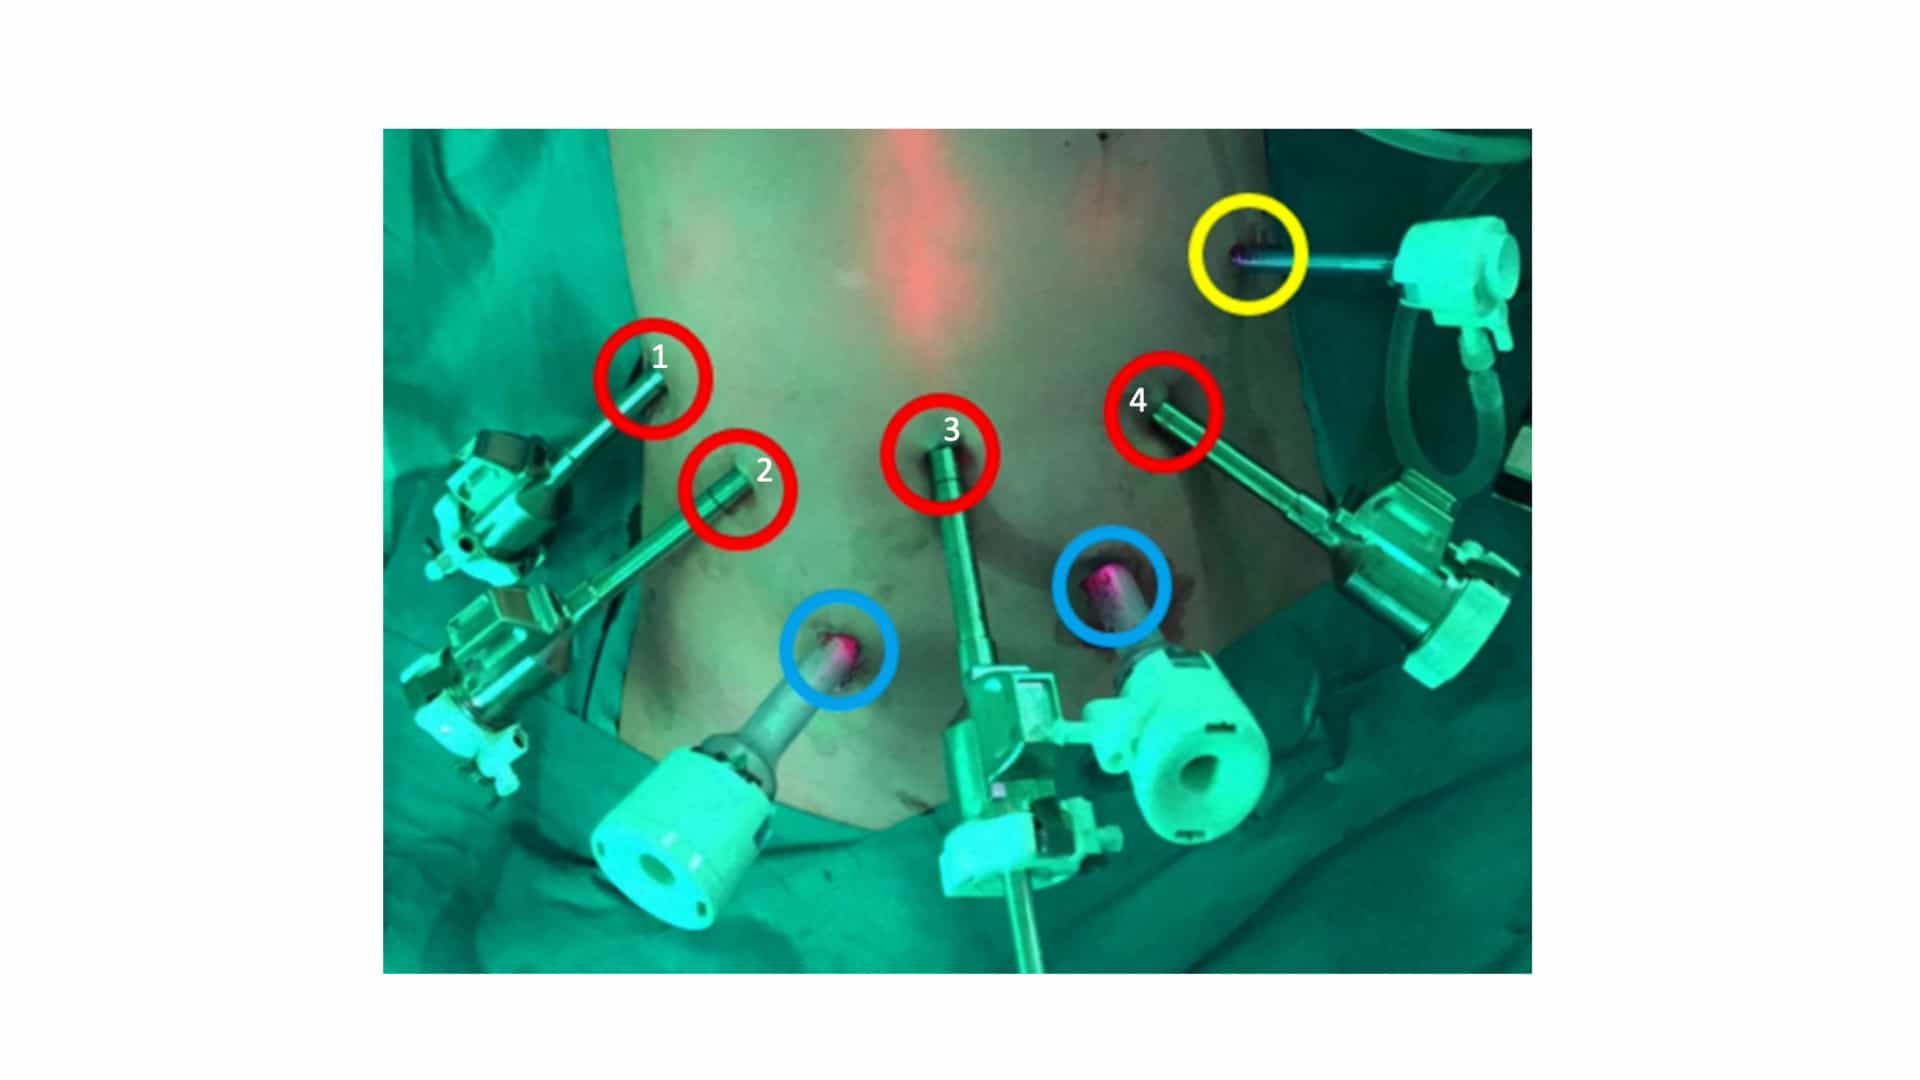

Robotic D3 Partial Duodenal Resection with Primary Side-to-Side Anastomosis
Published on: December 15, 2023
Multicenter outcomes of endoscopic resection for small non-ampullary duodenal neuroendocrine tumors
Mamoru Tokunaga1, Kenichiro Okimoto2, Yuji Ino3
1Division of Endoscopy, Chiba Cancer Center, 666-2 Nitona-Cho, Chuo-Ku, Chiba, Chiba, 260-8717, Japan. mtokunaga@chiba-cc.jp.

Background:
Endoscopic resection is an accepted treatment option for appropriately selected non-ampullary duodenal neuroendocrine tumors (DNETs) measuring 10 mm or less. However, multicenter data from routine practice settings remain limited, particularly regarding histologic outcomes, adverse events, and recurrence after endoscopic resection.
Methods:
This retrospective multicenter cohort study included consecutive patients who underwent endoscopic resection for non-ampullary DNETs at six affiliated centers, including a cancer center, university hospitals, and community hospitals, between January 2012 and July 2024. Primary outcomes were histologically complete (R0) resection and procedure-related adverse events (bleeding and perforation). Secondary outcomes included en bloc resection and recurrence during follow-up. Technique-specific outcomes were summarized descriptively.
Results:
A total of 36 patients with 36 lesions were analyzed. Resection techniques were conventional endoscopic mucosal resection (CEMR, n = 4), EMR with a cap (EMR-C, n = 10), endoscopic submucosal resection with a ligation device (ESMR-L, n = 19), endoscopic muscularis resection with an over-the-scope clip (EMRO, n = 1), and endoscopic submucosal dissection (ESD, n = 2). En bloc resection was achieved in 35/36 lesions (97.2%) and R0 resection in 26/36 (72.2%). Adverse events occurred in 2/36 (5.6%; one bleeding and one perforation). During a median follow-up of 48 months (range < 1-156), no recurrence was documented. ESMR-L was the most frequently selected technique (19/36, 52.8%) and was performed at all six institutions. Among lesions treated with ESMR-L, en bloc resection was achieved in 19/19 lesions (100%), R0 resection in 15/19 lesions (78.9%), and no procedure-related adverse events were documented.
Conclusions:
In this multicenter real-world cohort, endoscopic resection for small non-ampullary DNETs achieved a high en bloc resection rate, an acceptable R0 resection rate, and a low frequency of adverse events, with no documented recurrence during the available follow-up. These findings support endoscopic resection as a reasonable treatment option for appropriately selected patients.