Related Experiment Video
Updated: Mar 31, 2026
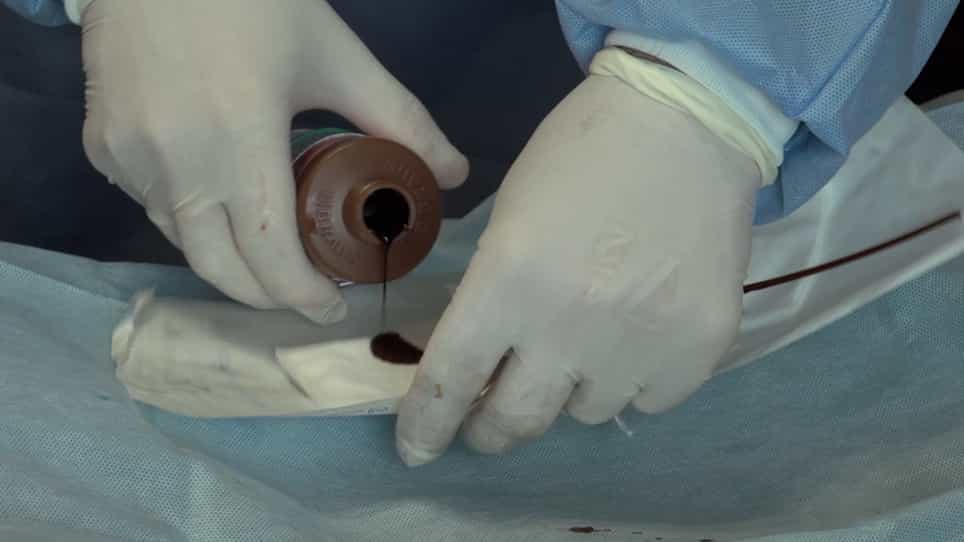

Application of Lucilia sericata Larvae in Debridement of Pressure Wounds in Outpatient Settings
Published on: December 4, 2021
Factors Associated With Treatment Failure of Infected Pressure Sores
Kheeldass Jugun1, Jean-Christophe Richard, Benjamin A Lipsky
1*Division of Plastic, Reconstructive, and Aesthetic Surgery Service, Geneva University Hospitals, Geneva, Switzerland†Orthopedic Surgery Service, Geneva University Hospitals, Geneva, Switzerland‡Service of Infectious Diseases, Geneva University Hospitals, Geneva, Switzerland§Division of Medical Sciences, University of Oxford, Oxford, UK.

Objective:
In this study, we assess interdisciplinary surgical and medical parameters associated to recurrences of infected pressure ulcers.
Background:
There is a little in the published literature regarding factors associated with the outcome of treatment of infected pressure ulcers.
Methods:
We undertook a single-center review of spinal injured adults hospitalized for an infected pressure ulcer or implant-free osteomyelitis and reviewed the literature on this topic from 1990-2015.
Results:
We found 70 lesions in 31 patients (52 with osteomyelitis) who had a median follow-up of 2.7 years (range, 4 months to 19 years). The median duration of antibiotic therapy was 6 weeks, of which 1 week was parenteral. Clinical recurrence after treatment was noted in 44 infected ulcers (63%), after a median interval of 1 year. In 86% of these recurrences, cultures yielded a different organism than the preceding episode. By multivariate analyses, the following factors were not significantly related to recurrence: number of surgical interventions (hazard ratio 0.9, 95% confidence interval 0.5-1.5); osteomyelitis (hazard ratio 1.5; 0.7-3.1); immune suppression; prior sacral infections, and duration of total (or just parenteral) antibiotic sue. Patients with antibiotic treatment for <6 weeks had the same failure rate as those with as >12 weeks (χ test; P = 0.90).
Conclusions:
In patients with infected pressure ulcers, clinical recurrence occurs in almost two-thirds of lesions, but in only 14% with the same pathogen(s). The number of surgical debridements, flap use, or duration of antibiotic therapy was not associated with recurrence, suggesting recurrences are caused by reinfections caused by other extrahospital factors.

Related Concept Videos
 01:26
Factors Affecting the Risk of Infection
The integrity and count of the white blood cells help the body resist pathogens and fight infection. When impaired, it reduces the body's resistance to pathogens. The acidic pH levels of the gastrointestinal, genitourinary tracts, and skin...
 01:25
Peptic Ulcer Disease V: Surgical Management and Nursing Care
Surgical Interventions for Peptic Ulcer Disease
 01:22
Pathophysiology of Peptic Ulcer Disease: Injurious Factors
In the antrum region, G cells secrete the gastrin hormone that binds to gastrin-cholecystokinin-B (CCK2) receptors on parietal and enterochromaffin-like (ECL) cells in the fundic glands. Simultaneously, the vagus nerve releases acetylcholine, which binds...
 01:27
Peptic Ulcer
 01:26
Peptic Ulcer Disease IV: Management
The therapeutic approach involves ensuring adequate rest, implementing drug therapy, promoting smoking cessation, making dietary modifications, and emphasizing long-term follow-up care.
Pharmacological management
The prevailing therapy for peptic ulcers involves a combination of managing the patient's current...
 01:24
Pathophysiology of Peptic Ulcer Disease: Mucosal Defense Factors