Related Experiment Video
Updated: Mar 30, 2026

Deep Neuromuscular Blockade Leads to a Larger Intraabdominal Volume During Laparoscopy
Published on: June 25, 2013
Analysis of Risk Factors for Intraoperative Conversion of Laparoscopic Myomectomy
Evelien M Sandberg1, Sarah L Cohen2, Frank Willem Jansen3
1Department of Gynecology, Minimally Invasive Surgery, Leiden University Medical Center, Leiden, The Netherlands.

Objectives:
To report the surgical outcomes of laparoscopic myomectomy (LM) and abdominal myomectomy (AM) at a high-volume tertiary care hospital, to evaluate the risk of conversion during LM, and to analyze the associated risk factors.
Design:
Retrospective cohort study (Canadian Task Force classification II).
Patients:
All patients who underwent LM and AM in a tertiary academic center in Boston, Massachusetts between 2009 and 2012.
Intervention:
Medical records were reviewed for baseline characteristics and perioperative outcomes. Robot-assisted laparoscopy was considered a subtype of LM.
Results:
A total of 966 patients underwent myomectomy during the study period, including 731 LM cases (75.67%) and 235 AM cases (24.33%). Compared with patients undergoing LM, those undergoing AM had more myomas removed and heavier specimens (mean number of myomas, 12.60 vs 3.54, p ≤ .001; mean weight, 592.75 g vs 263.4 g, p ≤ .001). Conversion was necessary in 8 LM cases (1.09%). All conversions were reactive in nature and were associated with greater blood loss (mean, 1381.25 vs 167.95 mL; p ≤ .001) and longer hospital stay (mean, 3.13 vs 0.55 days; p ≤ .001) compared with cases without conversion. Factors associated with conversion included both the number and the weight of myomas removed (mean number, 9.75 vs 3.48, p = .003; mean weight, 667.9 vs 259.25 g, p = .015), especially with myomas weighing >500 g (odds ratio = 8.551; p = .005).
Conclusion:
The risk of conversion for LM was low (1.09%) in this cohort, and was associated both with the number and the weight of myomas removed. LM is a feasible approach for surgical management of myomas in the majority of cases; however, when myomas are expected to weigh >500 g, it may be prudent to consider referring those cases to specialized centers with highly experienced teams.
More Related Videos
 05:46
Introduction of Intracapsular Rotary-cut Procedures IRCP: A Modified Hysteromyomectomy Procedures Facilitating Fertility Preservation
Published on: January 17, 2019
 05:21
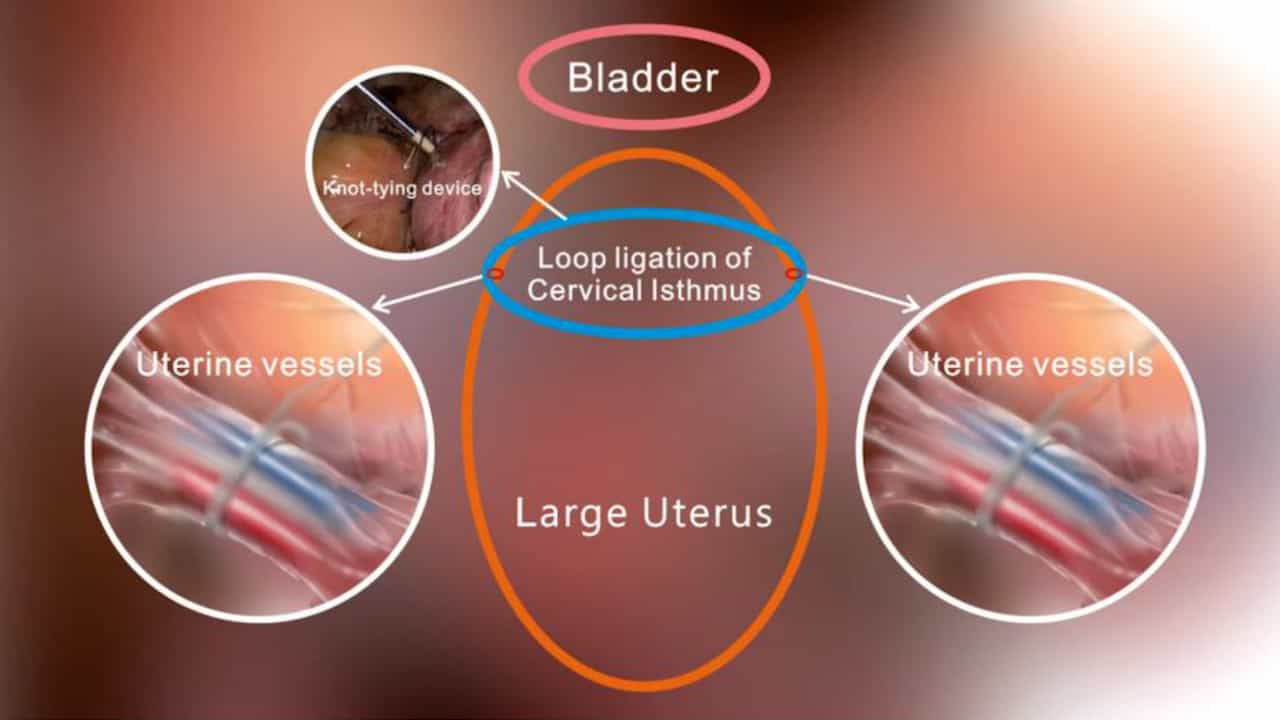
Laparoscopic Extracorporeal Knot-Tying for Uterine Vessel Occlusion during Hysterectomy with Cervical Cerclage in Large Uteri
Published on: September 12, 2025