Related Experiment Video
Updated: Sep 11, 2026
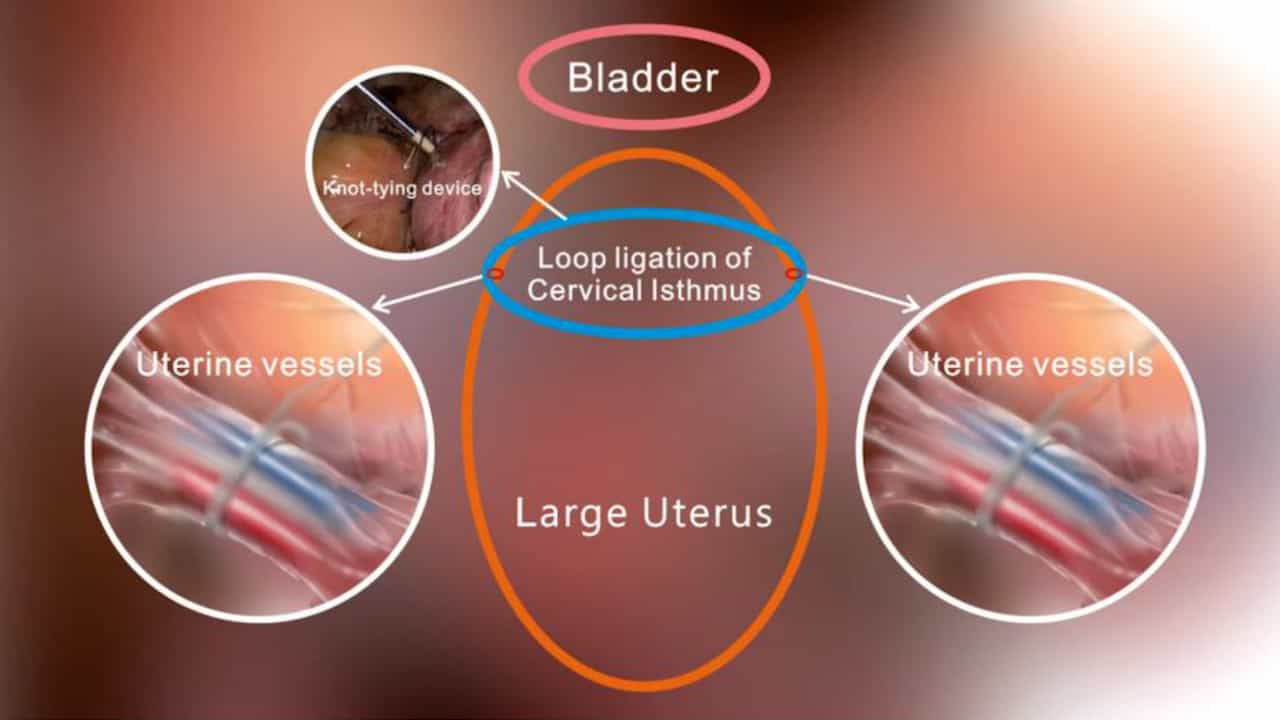

Laparoscopic Extracorporeal Knot-Tying for Uterine Vessel Occlusion during Hysterectomy with Cervical Cerclage in Large Uteri
Published on: September 12, 2025
Hysteroscopy-assisted laparoscopic tubo-tubal reanastomosis using a modified sequential distal-knot suturing
Minjiao Zhu1, Shunna Ge1, Siqin Yang1
1International Peace Maternity and Child Health Hospital, School of Medicine, Shanghai Jiao Tong University, Shanghai, China; Shanghai Key Laboratory of Embryo Original Diseases, Shanghai, China; Shanghai Municipal Key Clinical Specialty, Shanghai, China.

Study Objective:
To describe a modified sequential distal-knot suturing technique in hysteroscopy-assisted laparoscopic tubo-tubal reanastomosis.
Design:
Surgical video article. Stepwise narrated video demonstration of the modified technique.
Participants:
A total of 25 women after sterilization were included in our study.
Setting:
With China's fertility policy adjustment, more women seek fertility restoration after tubal ligation via tubal reanastomosis or in vitro fertilization (IVF) [1]. Although laparoscopic reanastomosis may offer advantages such as less invasiveness, faster recovery, the possibility of natural conception and more than one subsequent pregnancy, and potentially lower costs than IVF, the choice between the two approaches should be individualized according to age, ovarian reserve, remaining tubal length and condition, and male factor infertility [2,3]. Nevertheless, the laparoscopic procedure itself is technically demanding due to the small tubal lumen and the need for precise multiple sutures that tend to tangle and prolong operative time [4]. Here, we describe a hysteroscopy-assisted laparoscopic tubo-tubal reanastomosis with a modified technique that organizes sutures, lowers difficulty, and improves feasibility.
Interventions:
Hysteroscopy-assisted laparoscopic surgery was performed. After opening the mesosalpinx and confirming anastomosis ends, the sterilized segment was resected. The muscular layer and mucosa were sutured with 5-0 absorbable sutures at 6, 12, 9, and 3 o'clock. A modified suturing and knotting technique was employed here: After each stitch is placed, a temporary distal knot is tied and the suture ends are cut before the next stitch is placed. Once all four stitches have been secured in this manner, the temporary distal knots are sequentially cut and the corresponding suture ends are tied proximally. Hysteroscopy was performed to assess tubal patency and confirm proper repair.
Conclusion:
Our technique, described and demonstrated in this video article, is a feasible and technically reproducible approach for restoring fertility in women after sterilization. The modified sequential distal-knot suturing technique prevents suture disorganization and limit traction on the tubal ends, thereby reducing tubal injury and operative time caused by repeated manipulation-a feature conducive to wider adoption.
