Related Experiment Video
Updated: Mar 29, 2026


A Syngeneic Mouse Model of Metastatic Renal Cell Carcinoma for Quantitative and Longitudinal Assessment of Preclinical Therapies
Published on: April 12, 2017
Everolimus Versus Sunitinib Prospective Evaluation in Metastatic Non-Clear Cell Renal Cell Carcinoma (ESPN): A
Nizar M Tannir1, Eric Jonasch1, Laurence Albiges2
1Department of Genitourinary Medical Oncology, Division of Cancer Medicine, The University of Texas MD Anderson Cancer Center, Houston, TX, USA.

Background:
Sunitinib and everolimus are standard first-line and second-line therapies, respectively, in clear cell renal cell carcinoma (ccRCC).
Objective:
To conduct a randomized phase 2 trial comparing sunitinib and everolimus in non-clear cell RCC (non-ccRCC).
Design, Setting, And Participants:
Patients with metastatic, non-ccRCC, or ccRCC with >20% sarcomatoid features (ccSRCC) were randomized to receive sunitinib or everolimus with crossover at disease progression.
Outcome Measurement And Statistical Analysis:
Primary end point was progression-free survival (PFS) in first-line therapy; 108 patients were needed to show improvement in median PFS (mPFS) from 12 wk with sunitinib to 20 wk with everolimus.
Results And Limitations:
Interim analysis of 68 patients (papillary [27], chromophobe [12], unclassified [10], translocation [7], ccSRCC [12]) prompted early trial closure. The mPFS in first-line therapy was 6.1 mo with sunitinib and 4.1 mo with everolimus (p=0.6); median overall survival (mOS) was not reached with sunitinib and was 10.5 mo with everolimus, respectively (p=0.014). At final analysis, mOS was 16.2 and 14.9 mo with sunitinib and everolimus, respectively (p=0.18). There were four partial responses (PRs) in first-line therapy (sunitinib: 3 of 33 [9%]; everolimus, 1 of 35 [2.8%]) and four PRs in second-line therapy (sunitinib: 2 of 21 [9.5%]; everolimus, 2 of 23 [8.6%]), with mPFS of 1.8 mo and 2.8 mo, respectively. In patients without sarcomatoid features in their tumors (n=49), mOS was 31.6 mo with sunitinib and 10.5 mo with everolimus (p=0.075). Genomic profiling of a chromophobe RCC from a patient with a PR to first-line everolimus revealed a somatic TSC2 mutation.
Conclusions:
In this trial, everolimus was not superior to sunitinib. Both agents demonstrated modest efficacy, underscoring the need for better therapies in non-ccRCC.
Patient Summary:
This randomized phase 2 trial provides the first head-to-head comparison of everolimus and sunitinib in patients with metastatic non-clear cell renal cell carcinoma (non-ccRCC). The observed very modest efficacy underscores the need to develop more effective therapies for non-ccRCC.
More Related Videos
 07:50
Utilization of Ultrasound Guided Tissue-directed Cellular Implantation for the Establishment of Biologically Relevant Metastatic Tumor Xenografts
Published on: May 25, 2018
 11:27
Modeling Spontaneous Metastatic Renal Cell Carcinoma mRCC in Mice Following Nephrectomy
Published on: April 29, 2014
Related Concept Videos
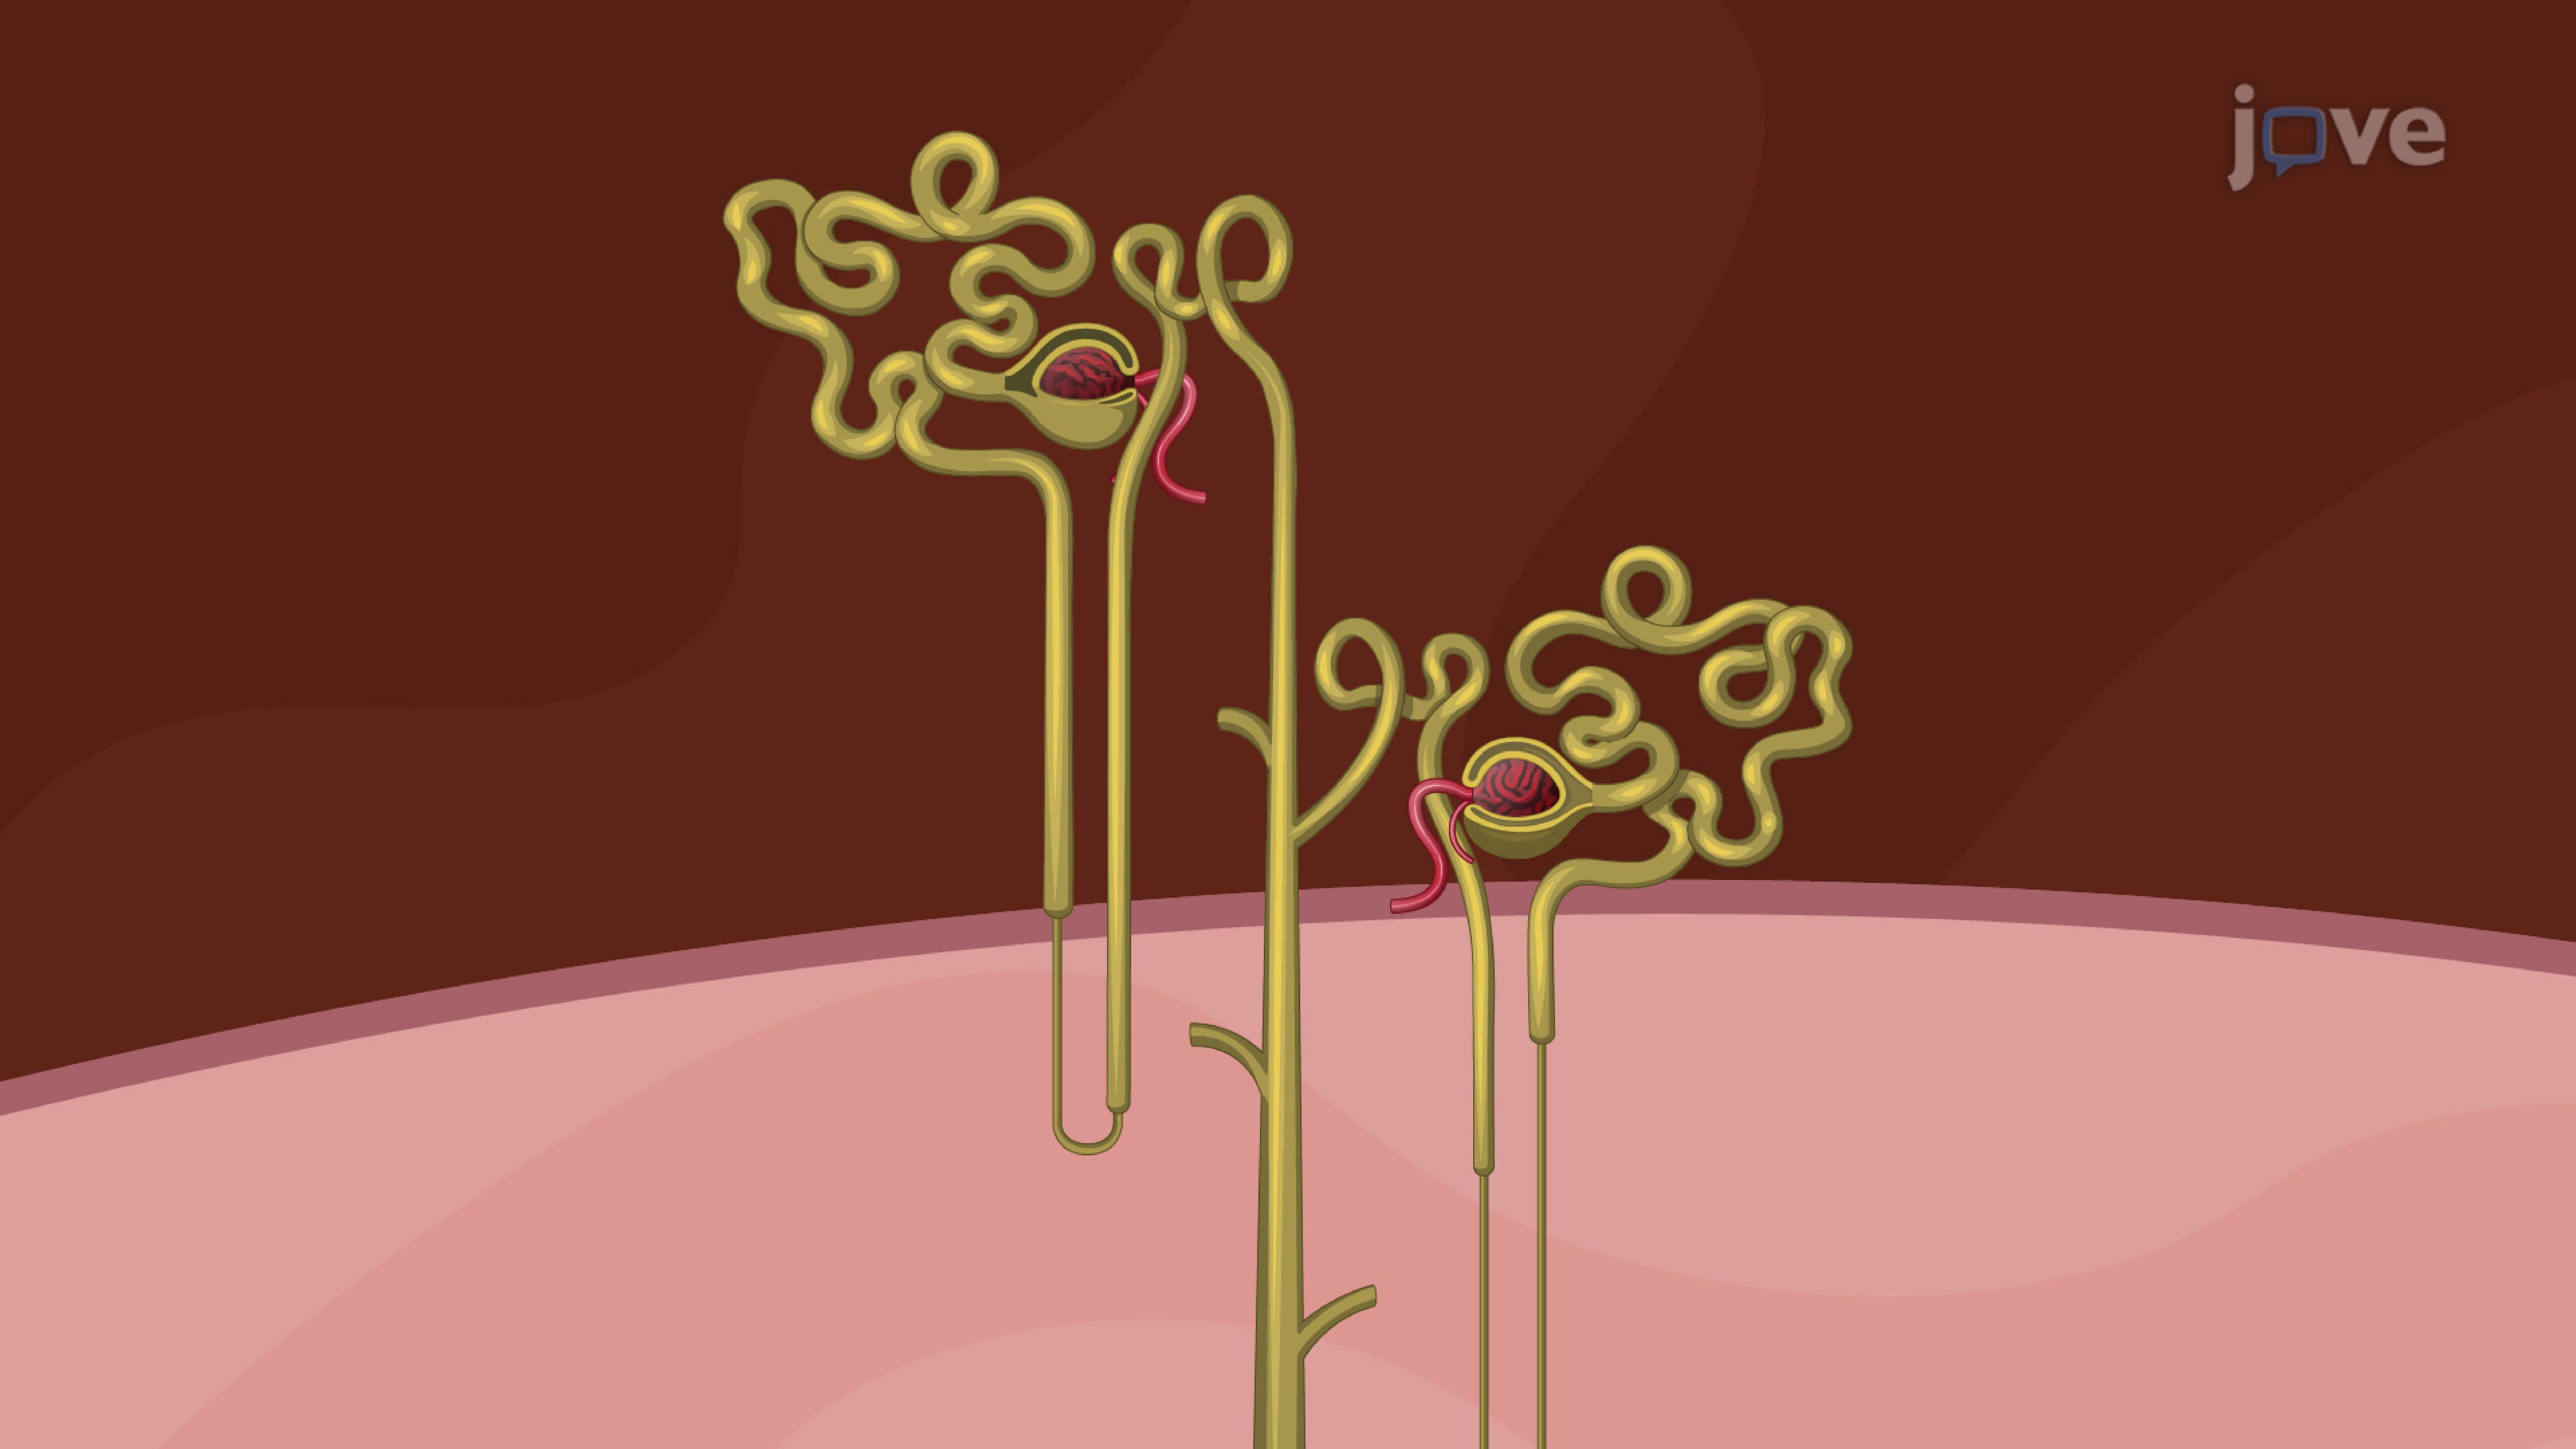 01:15
Renal Drug Excretion: Overview
A nephron consists of two primary structures: the renal corpuscle and the renal tubule. The renal corpuscle contains the glomerulus, a network of capillaries where the first step of renal excretion, glomerular filtration, occurs. Blood pressure forces water, ions, and small molecules...
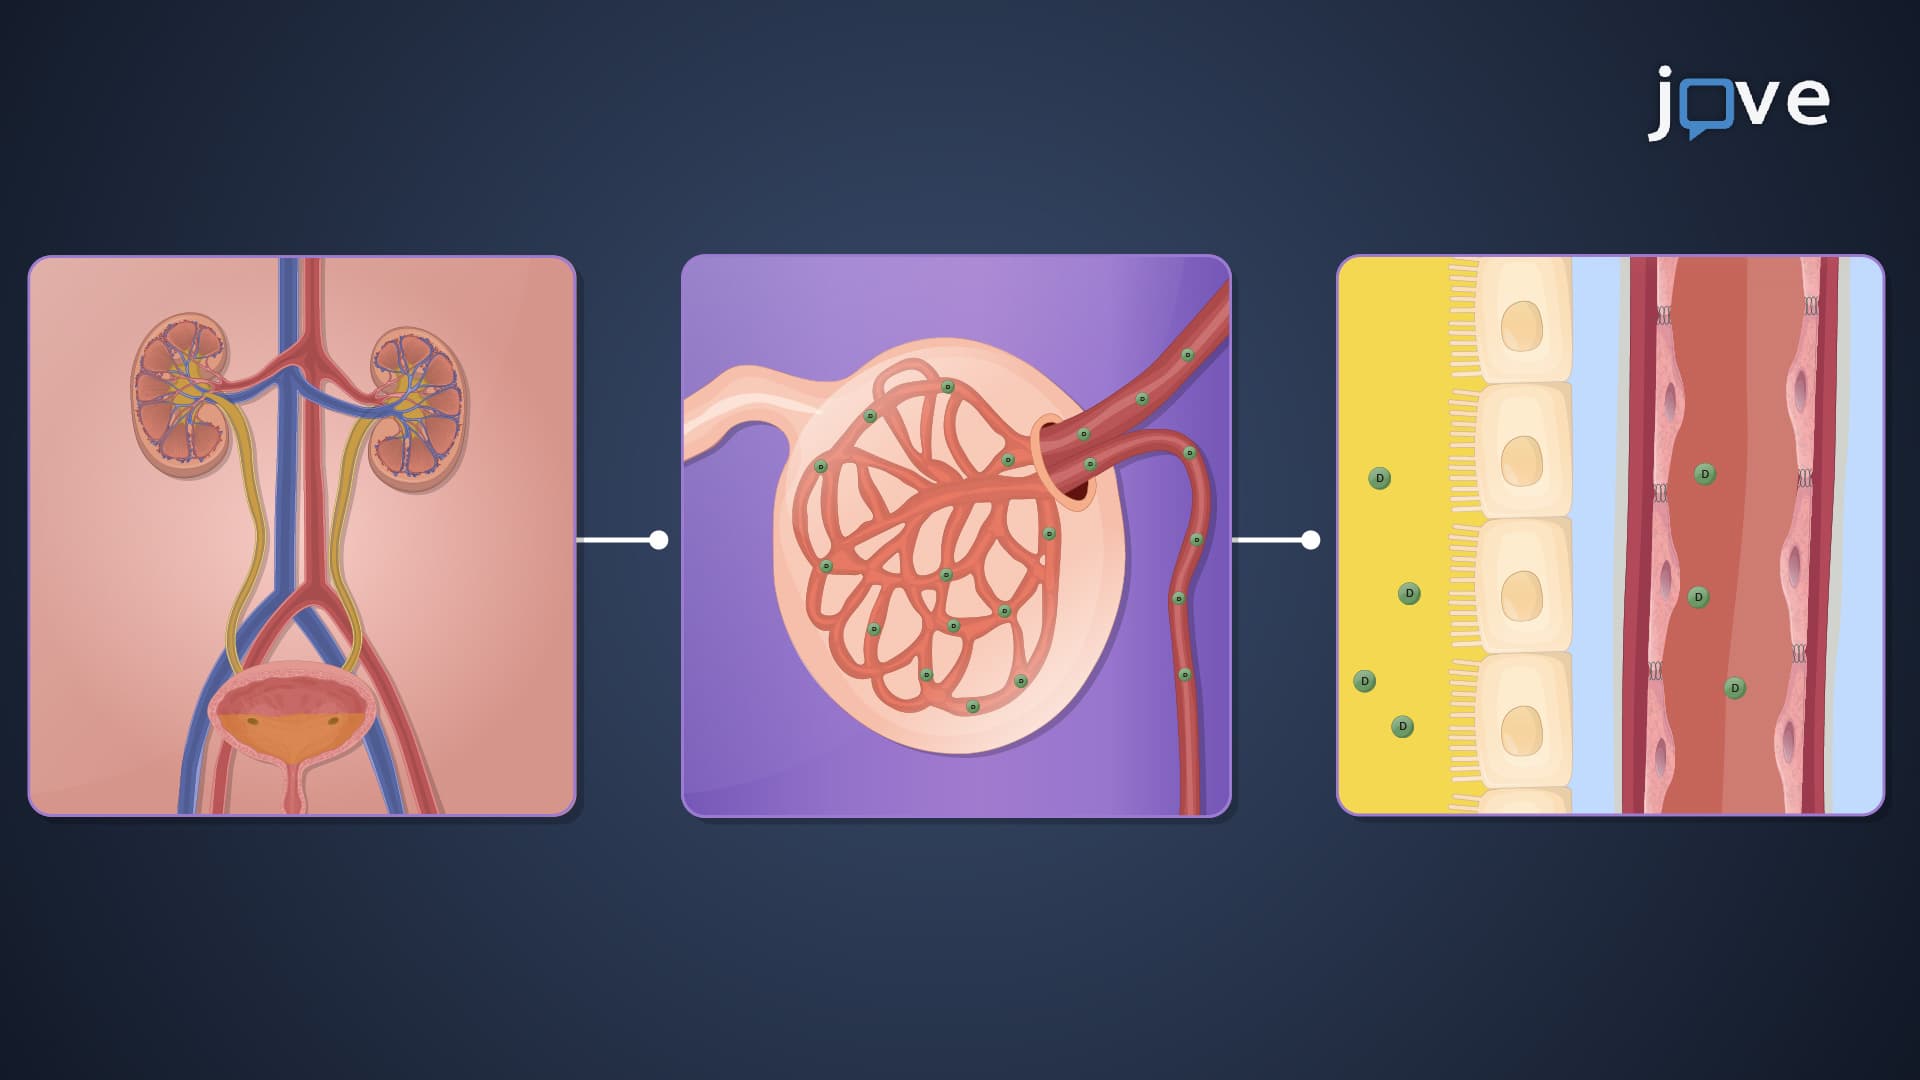 01:08
Renal Drug Clearance: Comparison Between Renal Excretion Methods
Renal clearance is often associated with the renal glomerular filtration rate (GFR), which represents the rate at which plasma is filtered through the glomeruli in the kidney. When drug reabsorption is minimal and there is no active secretion, renal clearance is closely related to the...
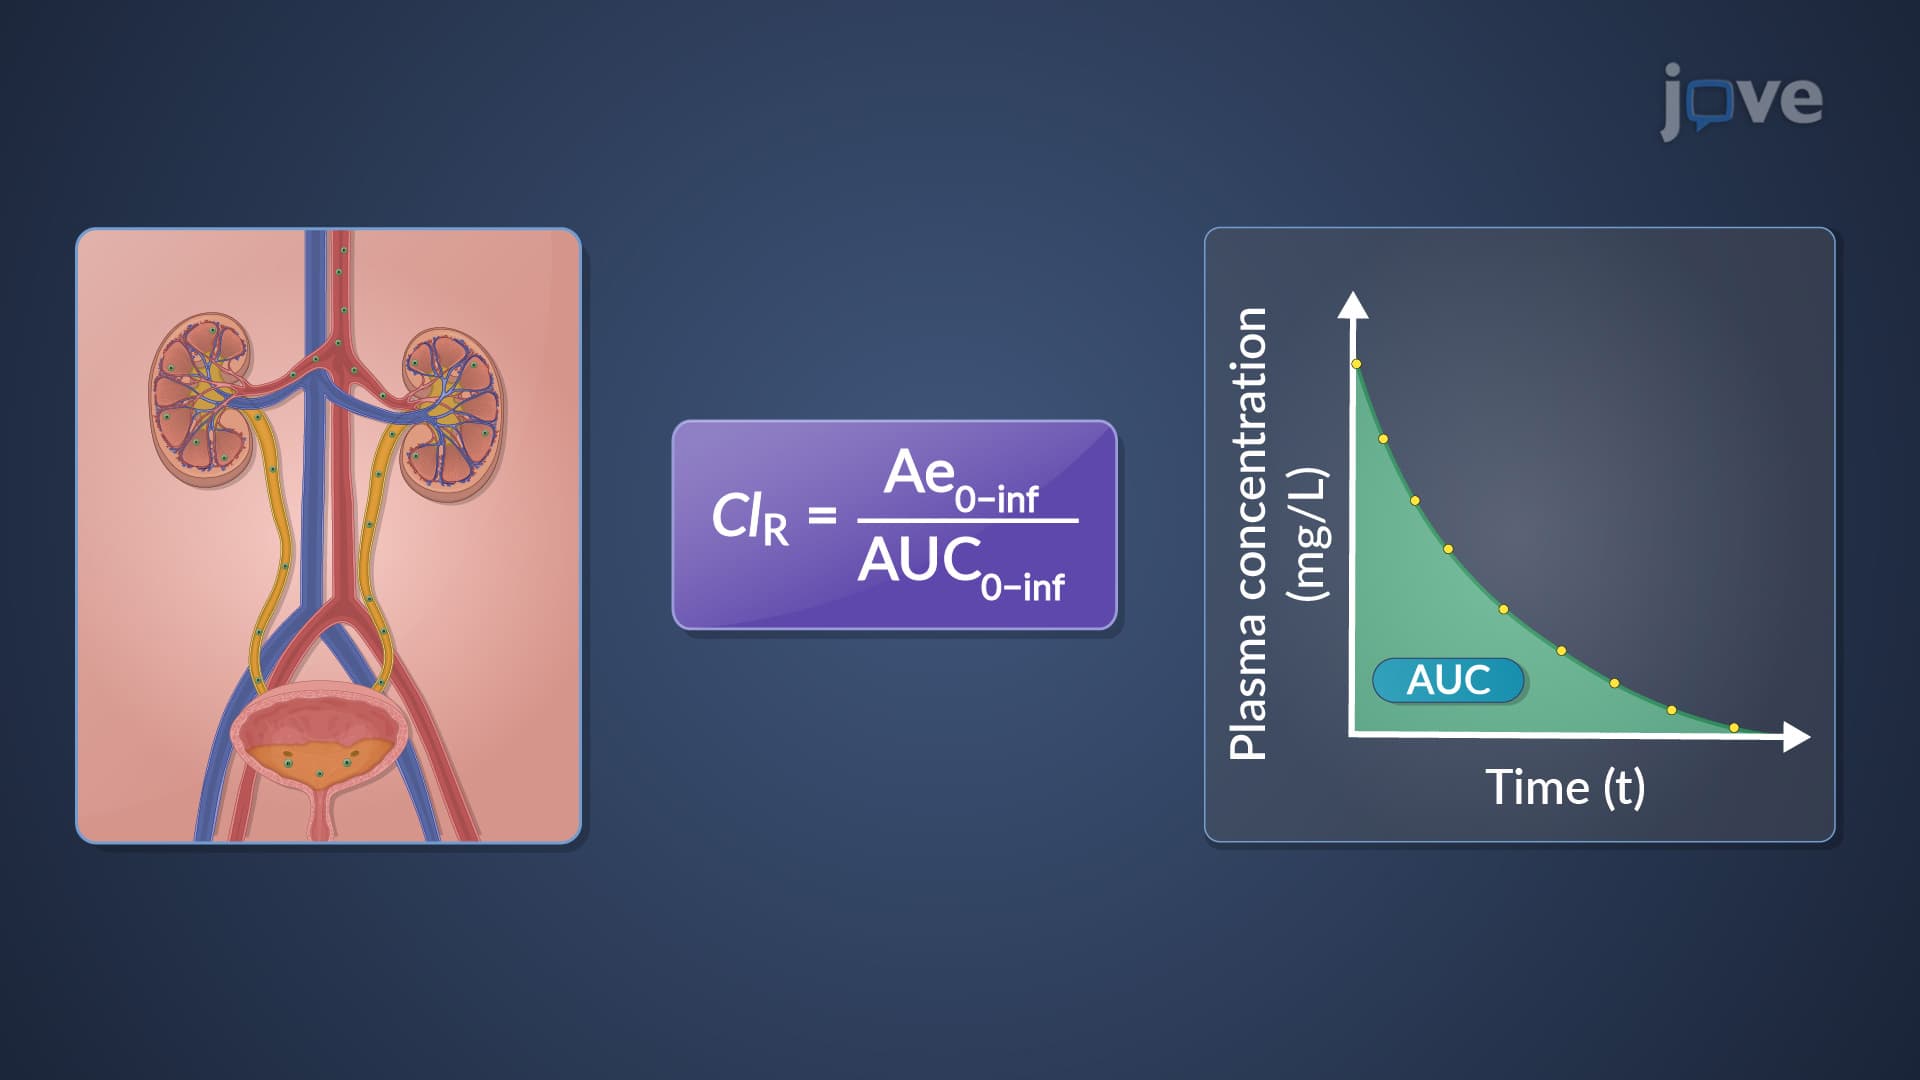 01:06
Renal Drug Clearance: Overview
Renal clearance can be calculated using different methods. One approach is to divide the urinary drug excretion rate by the plasma drug concentration. This method directly measures renal clearance, indicating the kidneys' efficiency in...
 01:25
Renal Drug Excretion: Tubular Reabsorption
 01:28
Renal Drug Excretion: Tubular Secretion
 02:56
Treatment Resistent Cancers