Related Experiment Video
Updated: Mar 26, 2026

Integration of Brain Tissue Saturation Monitoring in Cardiopulmonary Exercise Testing in Patients with Heart Failure
Published on: October 1, 2019
Predictors of cerebral blood flow in patients with and without anemia
Matthew T Borzage1, Adam M Bush2, Soyoung Choi3
1Division of Neonatology and Radiology, Children's Hospital Los Angeles, Los Angeles, California;

Insights
Cerebral blood flow (CBF) regulation in sickle cell disease (SCD) is primarily linked to oxygen content, not blood viscosity. These findings clarify normal CBF regulation, crucial for understanding stroke risk in affected populations.
Area of Science:
- Neurology
- Hematology
- Physiology
Background:
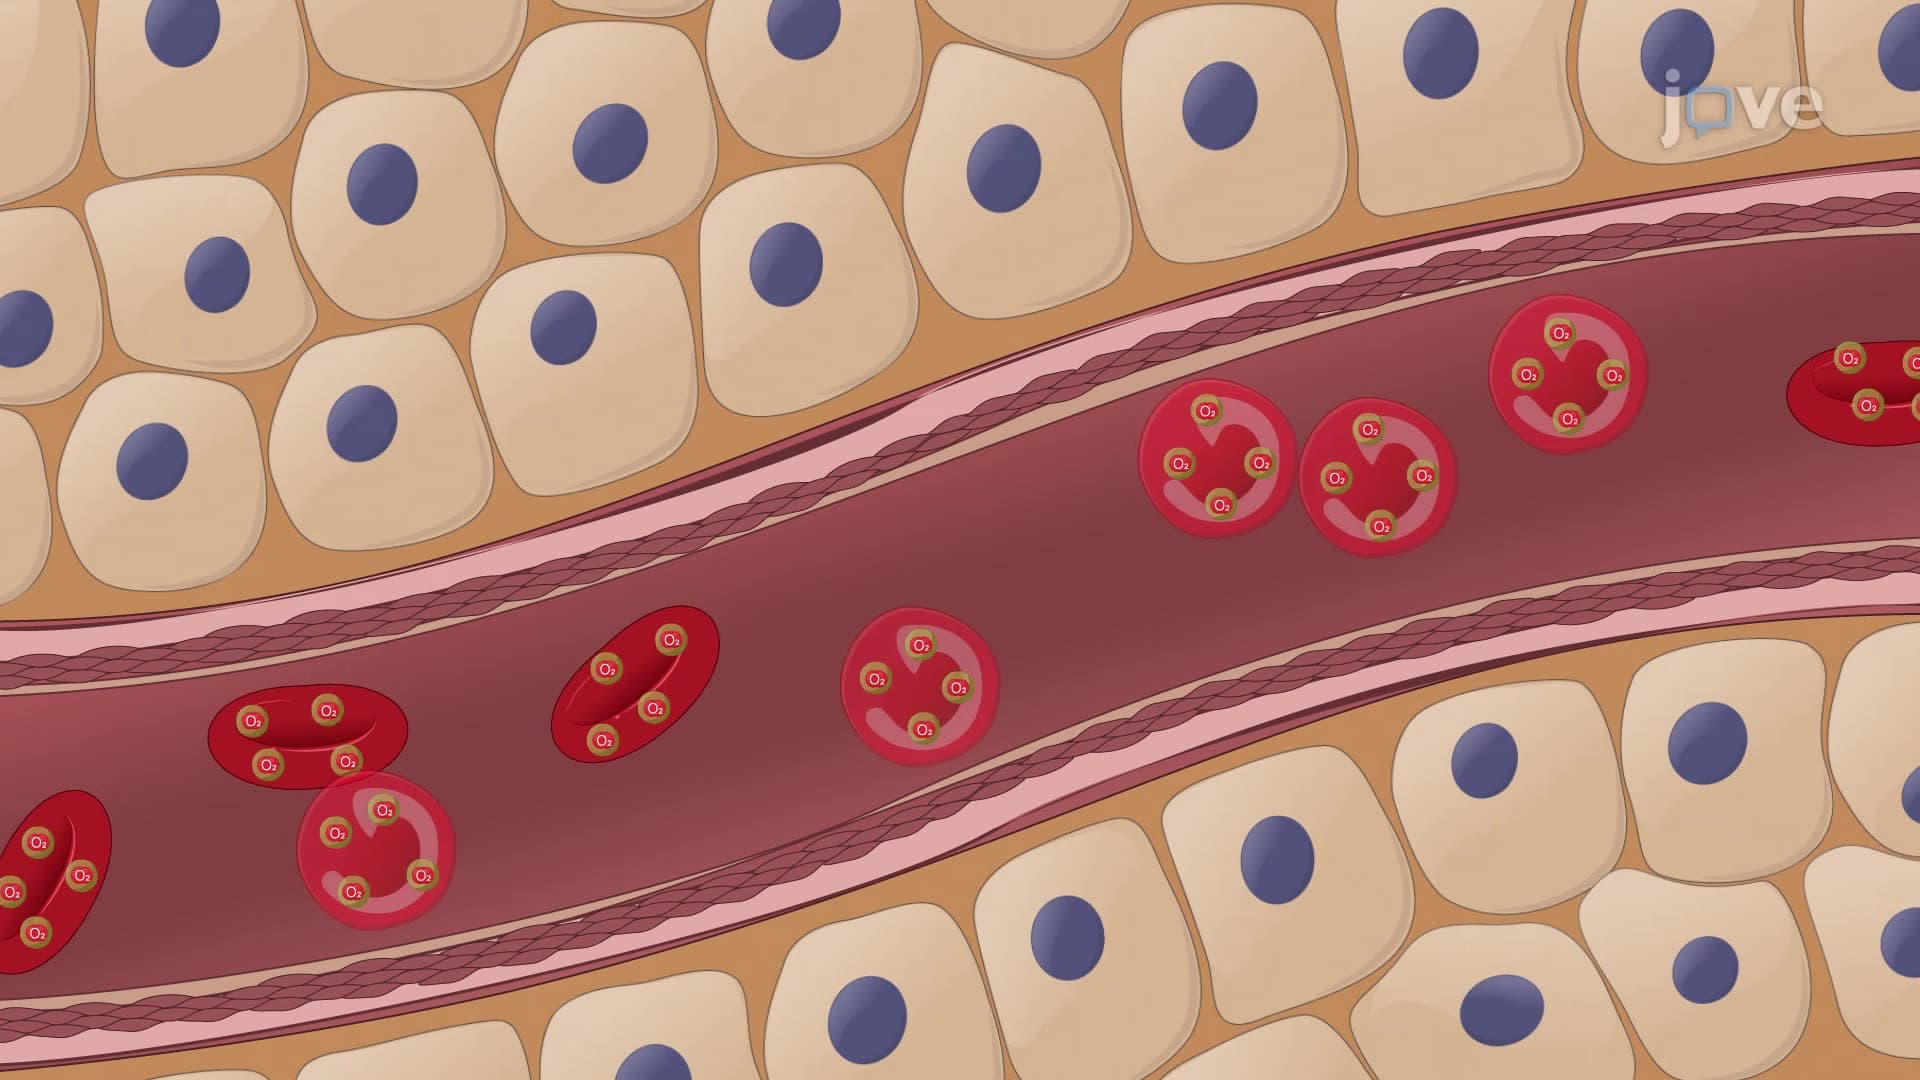
- Sickle cell disease (SCD) is a leading cause of childhood stroke, often attributed to oxygen supply-demand imbalance.
- Resting cerebral blood flow (CBF) is understudied in African Americans, a population with common risk factors like obesity and hypertension.
- Understanding CBF in this demographic is crucial for elucidating SCD's physiological underpinnings.
Purpose of the Study:
- To investigate resting cerebral blood flow (CBF) in young, asymptomatic African Americans with and without sickle cell trait.
- To differentiate the effects of chronic anemia from sickle hemoglobin on CBF.
- To analyze factors influencing CBF regulation, including oxygen content, viscosity, and brain composition.
Main Methods:
- Measured CBF in 32 asymptomatic African Americans (14 with sickle cell trait).
- Studied 13 subjects with other anemias (thalassemia major, dyserythropoetic anemia, spherocytosis) to isolate anemia effects.
- Utilized multivariate regression analysis, complete blood counts, hemoglobin electrophoresis, and hyperoxia challenges.
Main Results:
- Oxygen content was the strongest predictor of CBF (r(2)= 0.33, P<0.001).
- CBF declined with age, linked to reduced gray matter, with persistent age effects possibly indicating microvascular impairment.
- CBF was independent of viscosity, hemoglobin S percentage, and BMI; hyperoxia reduced CBF by 12.6%.
Conclusions:
- Normal regulation of CBF, balancing oxygen supply and demand, is maintained despite hemoglobin subtypes.
- Oxygen content, not viscosity or hemoglobin S%, is the primary determinant of CBF in this population.
- Findings provide insights into cerebrovascular physiology relevant to SCD and stroke risk.
Abstract:
Sickle cell disease (SCD) is the most common cause of stroke in childhood and results primarily from a mismatch of cerebral oxygen supply and demand rather than arterial obstruction. However, resting cerebral blood flow (CBF) has not been examined in the general African American population, in whom obesity, hypertension, cerebrovascular disease, and diminished cerebrovascular reserve capacity are common. To better understand the underlying physiological substrate upon which SCD is superimposed, we measured CBF in 32 young (age 28 ± 10 yr), asymptomatic African American subjects with and without sickle cell trait (n= 14). To characterize the effects of chronic anemia, in isolation of sickle hemoglobin we also studied a cohort of 13 subjects with thalassemia major (n= 10), dyserythropoetic anemia (n= 1), or spherocytosis (n= 2). Blood was analyzed for complete blood count, hemoglobin electrophoresis, cell free hemoglobin, and lactate dehydrogenase. Multivariate regression analysis showed that oxygen content was the strongest predictor of CBF (r(2)= 0.33,P< 0.001). CBF declined rapidly in the second and third decades of life, but this drop was explained by reductions in cerebral gray matter. However, age effects persisted after correction for brain composition, possibly representing microvascular impairment. CBF was independent of viscosity, hemoglobin S%, and body mass index. Hyperoxia resulted in reduced CBF by 12.6% (P= 0.0002), and CBF changes were proportional to baseline oxygen content (r(2)= 0.16,P= 0.02). These data suggest that these hemoglobin subtypes do not alter the normal CBF regulation of the balance of oxygen supply and demand.