Related Experiment Video
Updated: Mar 26, 2026
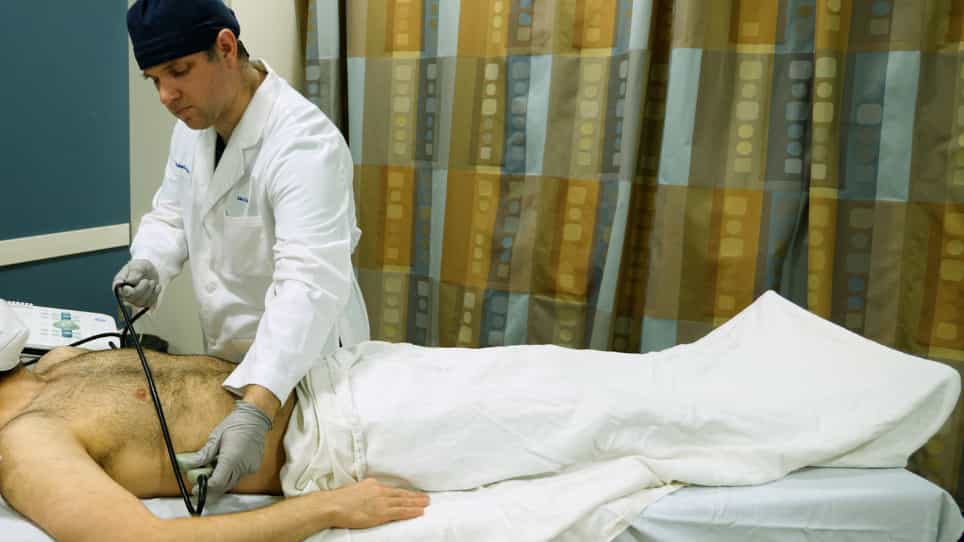

Focused Assessment with Sonography for Trauma FAST Exam: Image Acquisition
Published on: September 22, 2023
Computed tomography in hemodynamically unstable severely injured blunt and penetrating trauma patients
Carlos A Ordoñez1, Juan P Herrera-Escobar, Michael W Parra
1From the Clinical Research Center (C.A.O., J.P.H.-E., M.P.G.-G.), and Division of Trauma and Acute Care Surgery (C.A.O., P.A.R.-O., A.I.S.), Department of Surgery, Fundación Valle del Lili; Division of Trauma and Acute Care Surgery (C.A.O., D.A.M., M.B., L.F.P.), Department of Surgery, Universidad del Valle; and Division of Trauma and Acute Care Surgery (C.A.O., M.B., M.M., J.C.R.-M., L.F.P.), Department of Surgery, Hospital Universitario del Valle, Cali, Colombia; Division of Trauma Critical Care (M.W.P.), Broward General Medical Center, Fort Lauderdale, Florida; and Division of Trauma and Acute Care Surgery (J.C.P.), Department of Surgery University of Pittsburgh, Pittsburgh, Pennsylvania.

Background:
Dynamic and efficient resuscitation strategies are now being implemented in severely injured hemodynamically unstable (HU) patients as blood products become readily and more immediately available in the trauma room. Our ability to maintain aggressive resuscitation schemes in HU patients allows us to complete diagnostic imaging studies before rushing patients to the operating room (OR). As the criteria for performing computed tomography (CT) scans in HU patients continue to evolve, we decided to compare the outcomes of immediate CT versus direct admission to the OR and/or angio suite in a retrospective study at a government-designated regional Level I trauma center in Cali, Colombia.
Methods:
During a 2-year period (2012-2013), blunt and penetrating trauma patients (≥ 15 years) with an Injury Severity Score (ISS) greater than 15 who met criteria of hemodynamic instability (systolic blood pressure [SBP] <100 mm Hg and/or heart rate >100 beats/min and/or ≥ 4 U of packed red blood cells transfused in the trauma bay) were included. Isolated head trauma and patients who experienced a prehospital cardiac arrest were excluded. The main study outcome was mortality.
Results:
We reviewed 171 patients. CT scans were performed in 80 HU patients (47%) immediately upon arrival (CT group); the remaining 91 patients (53%) went directly to the OR (63 laparotomies, 20 thoracotomies) and/or 8 (9%) to the angio suite (OA group). Of the CT group, 43 (54%) were managed nonoperatively, 37 (46%) underwent surgery (15 laparotomies, 3 thoracotomies), and 2 (5%) underwent angiography (CT OA subgroup). None of the mortalities in the CT group occurred in the CT suite or during their intrahospital transfers.
Conclusion:
There was no difference in mortality between the CT and OA groups in HU patients. CT scan was attainable in 47% of HU patients and avoided surgery in 54% of the cases. Furthermore, CT scan was helpful in deciding definitive/specific surgical management in 46% scanned HU patients who necessitated surgery after CT.
Level Of Evidence:
Therapy/care management study, level IV.

Related Concept Videos
 01:10
Computed Tomography
The technique was invented in the 1970s and is based on the principle that as X-rays pass through the body, they are absorbed or reflected at different levels. In the technique, a patient lies on a motorized platform while a computerized axial tomography (CAT) scanner rotates...
 01:28
Imaging Studies for Cardiovascular System V: CT
 01:27
Imaging Studies III: Computed Tomography
 01:14
Imaging Studies I: CT and MRI
Description of the Procedures
Computed Tomography (CT) scan:
Computed Tomography (CT) scans use X-ray technology to generate detailed images of bones, organs, and tissues. During the scan, the patient lies on a moving table...
 01:26
Flail Chest-II
Assessment:
1. Clinical Evaluation:
History: