Related Experiment Video
Updated: Mar 26, 2026


Antimicrobial Synergy Testing by the Inkjet Printer-assisted Automated Checkerboard Array and the Manual Time-kill Method
Published on: April 18, 2019
Multicenter Prospective Cohort Study of Renal Failure in Patients Treated with Colistin versus Polymyxin B
Maria Helena Rigatto1, Maura S Oliveira2, Lauro V Perdigão-Neto2
1Infectious Diseases Service, Hospital São Lucas da Pontifícia Universidade Católica do Rio Grande do Sul, Porto Alegre, Brazil Infectious Diseases Service, Hospital de Clinicas de Porto Alegre, Porto Alegre, Brazil.

Abstract:
Nephrotoxicity is the main adverse effect of colistin and polymyxin B (PMB). It is not clear whether these two antibiotics are associated with different nephrotoxicity rates. We compared the incidences of renal failure (RF) in patients treated with colistimethate sodium (CMS) or PMB for ≥48 h. A multicenter prospective cohort study was performed that included patients aged ≥18 years. The primary outcome was renal failure (RF) according to Risk, Injury, Failure, Loss, and End-stage renal disease (RIFLE) criteria. Multivariate analysis with a Cox regression model was performed. A total of 491 patients were included: 81 in the CMS group and 410 in the PMB group. The mean daily doses in milligrams per kilogram of body weight were 4.2 ± 1.3 and 2.4 ± 0.73 of colistin base activity and PMB, respectively. The overall incidence of RF was 16.9% (83 patients): 38.3% and 12.7% in the CMS and PMB groups, respectively (P< 0.001). In multivariate analysis, CMS therapy was an independent risk factor for RF (hazard ratio, 3.35; 95% confidence interval, 2.05 to 5.48;P< 0.001) along with intensive care unit admission, higher weight, older age, and bloodstream and intraabdominal infections. CMS was also independently associated with a higher risk of RF in various subgroup analyses. The incidence of RF was higher in the CMS group regardless of the patient baseline creatinine clearance. The development of RF during therapy was not associated with 30-day mortality in multivariate analysis. CMS was associated with significantly higher rates of RF than those of PMB. Further studies are required to confirm our findings in other patient populations.
Insights
Colistimethate sodium (CMS) is linked to higher rates of acute kidney injury compared to polymyxin B (PMB). This study found CMS significantly increased renal failure risk in patients, highlighting a critical safety difference between these antibiotics.
Area of Science:
- Nephrology
- Infectious Diseases
- Pharmacology
Background:
- Nephrotoxicity is a primary concern for colistin and polymyxin B (PMB).
- Comparative nephrotoxicity rates between colistimethate sodium (CMS) and PMB remain unclear.
- Understanding these differences is crucial for patient safety and effective antibiotic selection.
Purpose of the Study:
- To compare the incidence of renal failure (RF) in patients treated with CMS versus PMB for at least 48 hours.
- To identify risk factors associated with RF in patients receiving these antibiotics.
Main Methods:
- A multicenter prospective cohort study involving adult patients (≥18 years).
- Renal failure (RF) was assessed using Risk, Injury, Failure, Loss, and End-stage renal disease (RIFLE) criteria.
- Multivariate Cox regression analysis was employed to determine independent risk factors.
Main Results:
- The overall incidence of RF was 16.9%.
- Patients receiving CMS had a significantly higher incidence of RF (38.3%) compared to those receiving PMB (12.7%) (P<0.001).
- CMS therapy was an independent risk factor for RF (HR, 3.35; P<0.001), alongside ICU admission, higher weight, older age, and specific infections.
Conclusions:
- Colistimethate sodium (CMS) is associated with significantly higher rates of renal failure compared to polymyxin B (PMB).
- CMS is an independent risk factor for RF, irrespective of baseline creatinine clearance.
- Further research is needed to validate these findings in diverse patient populations.
More Related Videos
 11:17
Multiplex Therapeutic Drug Monitoring by Isotope-dilution HPLC-MS/MS of Antibiotics in Critical Illnesses
Published on: August 30, 2018
 09:26
Antibiotic Efficacy Testing in an Ex vivo Model of Pseudomonas aeruginosa and Staphylococcus aureus Biofilms in the Cystic Fibrosis Lung
Published on: January 22, 2021
Related Concept Videos
 01:30
Acute Kidney Injury IV: Diagnostic Studies and Prevention
 01:15
Determination of Multiple Dosing Parameters: Steady-State, Minimum and Maximum Concentrations
 01:28
Acute Pyelonephritis II: Diagnostic Studies and Management
 01:24
Drug Accumulation During Multiple Dosing: Intermittent IV Infusions
 01:11
Renal Failure: Dose Adjustments
Reduced renal clearance and elimination rate are common outcomes of renal impairment. These alterations lead to a prolonged elimination half-life and an altered apparent volume of distribution for drugs. As a result, dosage adjustments are typically necessary to maintain optimal drug levels in the body.
However, dosage adjustments...
 01:15
Renal Drug Excretion: Overview
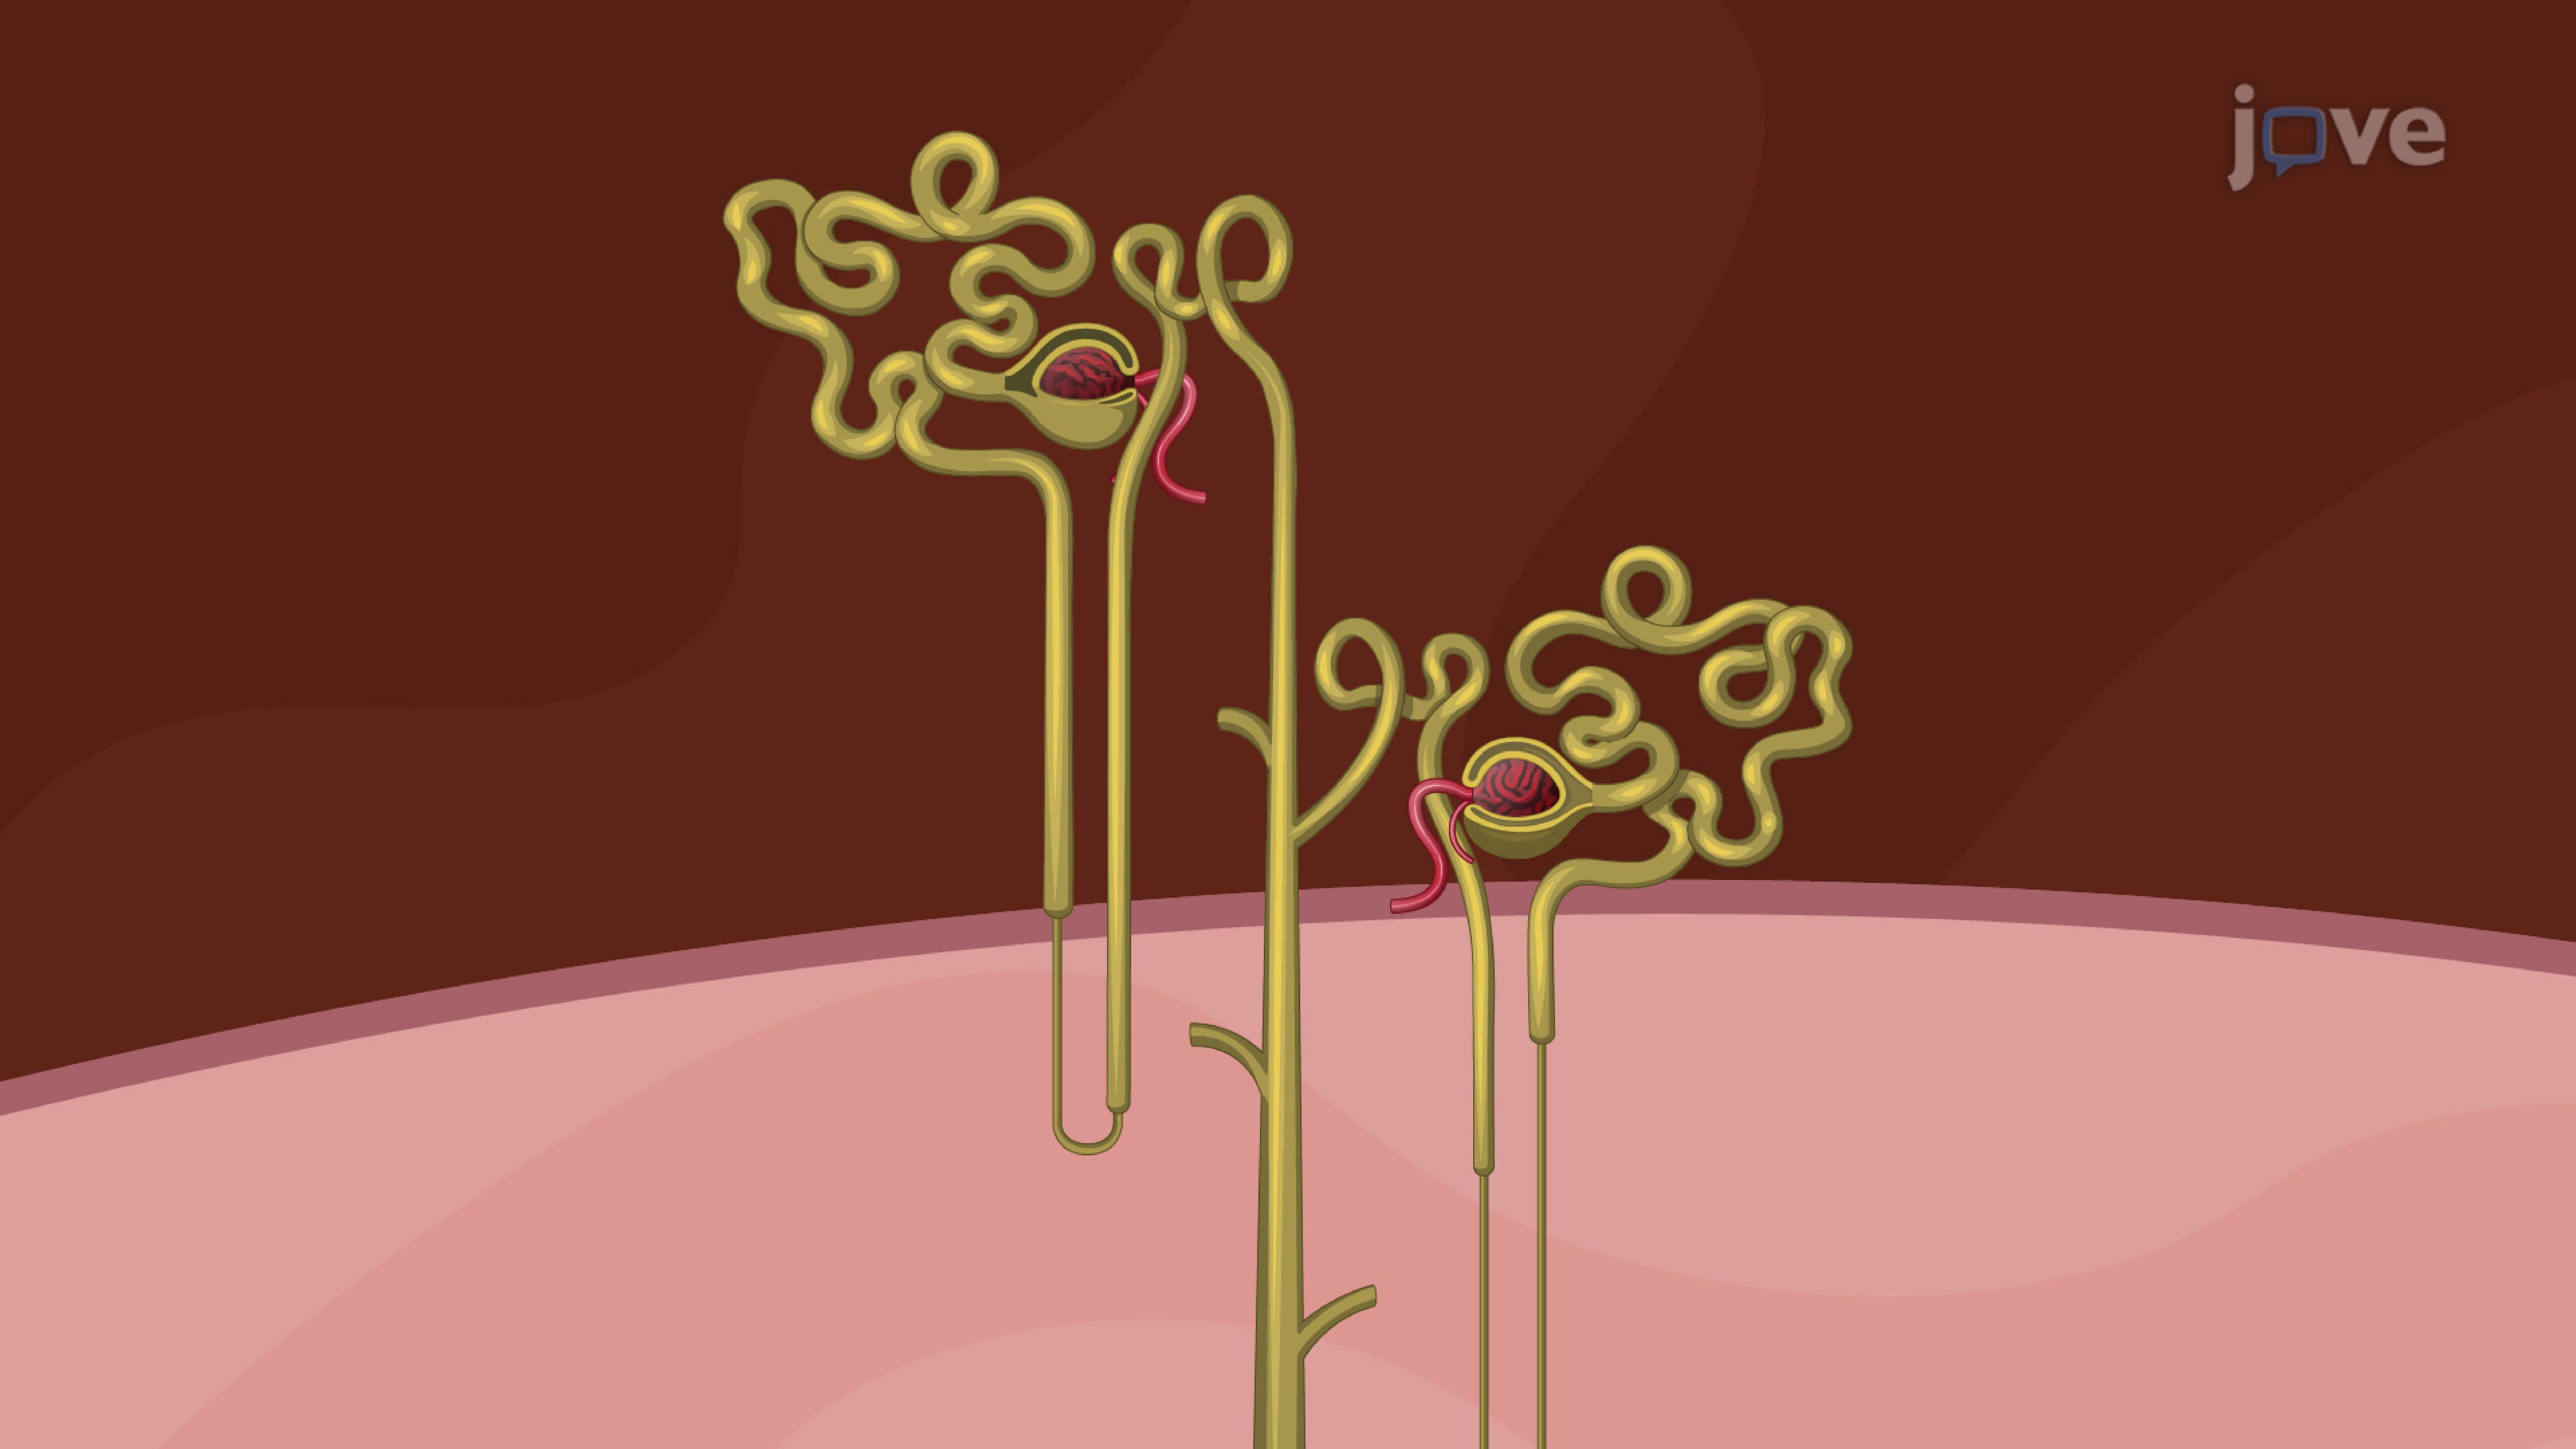
A nephron consists of two primary structures: the renal corpuscle and the renal tubule. The renal corpuscle contains the glomerulus, a network of capillaries where the first step of renal excretion, glomerular filtration, occurs. Blood pressure forces water, ions, and small molecules...