Related Experiment Video
Updated: Mar 25, 2026


Synergizing Antegrade Endoscopic with Bridging Vein Harvesting for Improvement of Great Saphenous Vein Graft Quality from the Lower Leg
Published on: November 19, 2019
Contemporary outcomes of lower extremity vascular repairs extending below the knee: A multicenter retrospective study
Gerald Fortuna1, Joseph J DuBose, Ranan Mendelsberg
1From the University of Texas Health Sciences Center (G.F., K.C-O.), Houston, Texas; David Grant Medical Center (J.J.D.), University of California-Davis, Sacramento, California; Los Angeles County and University of Southern California Hospital (R.M., K.I.), Los Angeles, California; University of Arizona (A.H., B.J.), Tucson, Arizona; University of Florida-Jacksonville (D.S.), Jacksonville, Florida; Loma Linda University Medical Center (M.J.S., T.A.O.), Loma Linda, California.

Objectives:
To determine the outcomes of vascular injury interventions extending below the knee.
Methods:
Vascular injury repairs extending below the knee from January 2008 to December 2014 were collected from six American College of Surgeons Level I trauma centers. Demographics, management, and outcomes were collected and analyzed.
Results:
A total of 194 vascular injuries were identified. The mean age was 33.7 years, with 88.1% male, and 71.1% had blunt injury. Admission systolic blood pressure was less than 90 mm Hg in 10.8%; prehospital tourniquets were used in 5.6%. Median mangled extremity severity score (MESS) was 6.0 [interquartile range, 6]. Imaging used included computed tomography angiography (58.2%) and angiography (7.2%); with 66 (34.0%) proceeding directly to OR based on examination alone. Vascular interventions were conducted primarily by vascular (66.0%) and trauma (25.3%) surgeons at a median time from injury of 8 hours (interquartile range, 7 hours). Initial interventions included graft interposition (57.7%) with saphenous vein (111) or synthetic graft (1), primary repair (14.9%), endovascular stent-graft (1.5%), and patch angioplasty (2.1%). Fasciotomy was performed at initial operation in 41.8%, and for delayed compartment syndrome in 2.1%. Vascular reintervention was required in 20 patients (6.7%) for bleeding (seven patients) or thrombosis (13 patients). There was a higher reintervention rates for thrombosis among interposition grafts with distal anastomotic sites at the below-knee popliteal compared to those extending to the tibioperoneal trunk or distal trifurcation vessels, but this was not significant. (4/60, 6.7% vs. 6/49, 12.2%; p = 0.34). Postintervention amputation rates were significantly higher among interposition grafts extending distal to the popliteal (4/60 [6.7%] vs. 15/49 [30.6%]; p = 0.006).
Conclusions:
The management of vascular injuries extending below the knee remains a complex issue of extremity trauma care. The need for delayed amputation is significantly more common when revascularization below the distal popliteal artery is required.
Level Of Evidence:
Prognostic/epidemiologic study, level III; therapeutic/care management study, level IV.

Related Concept Videos
 01:23
Peripheral Artery Disease V: Postoperative Nursing Management
 01:15
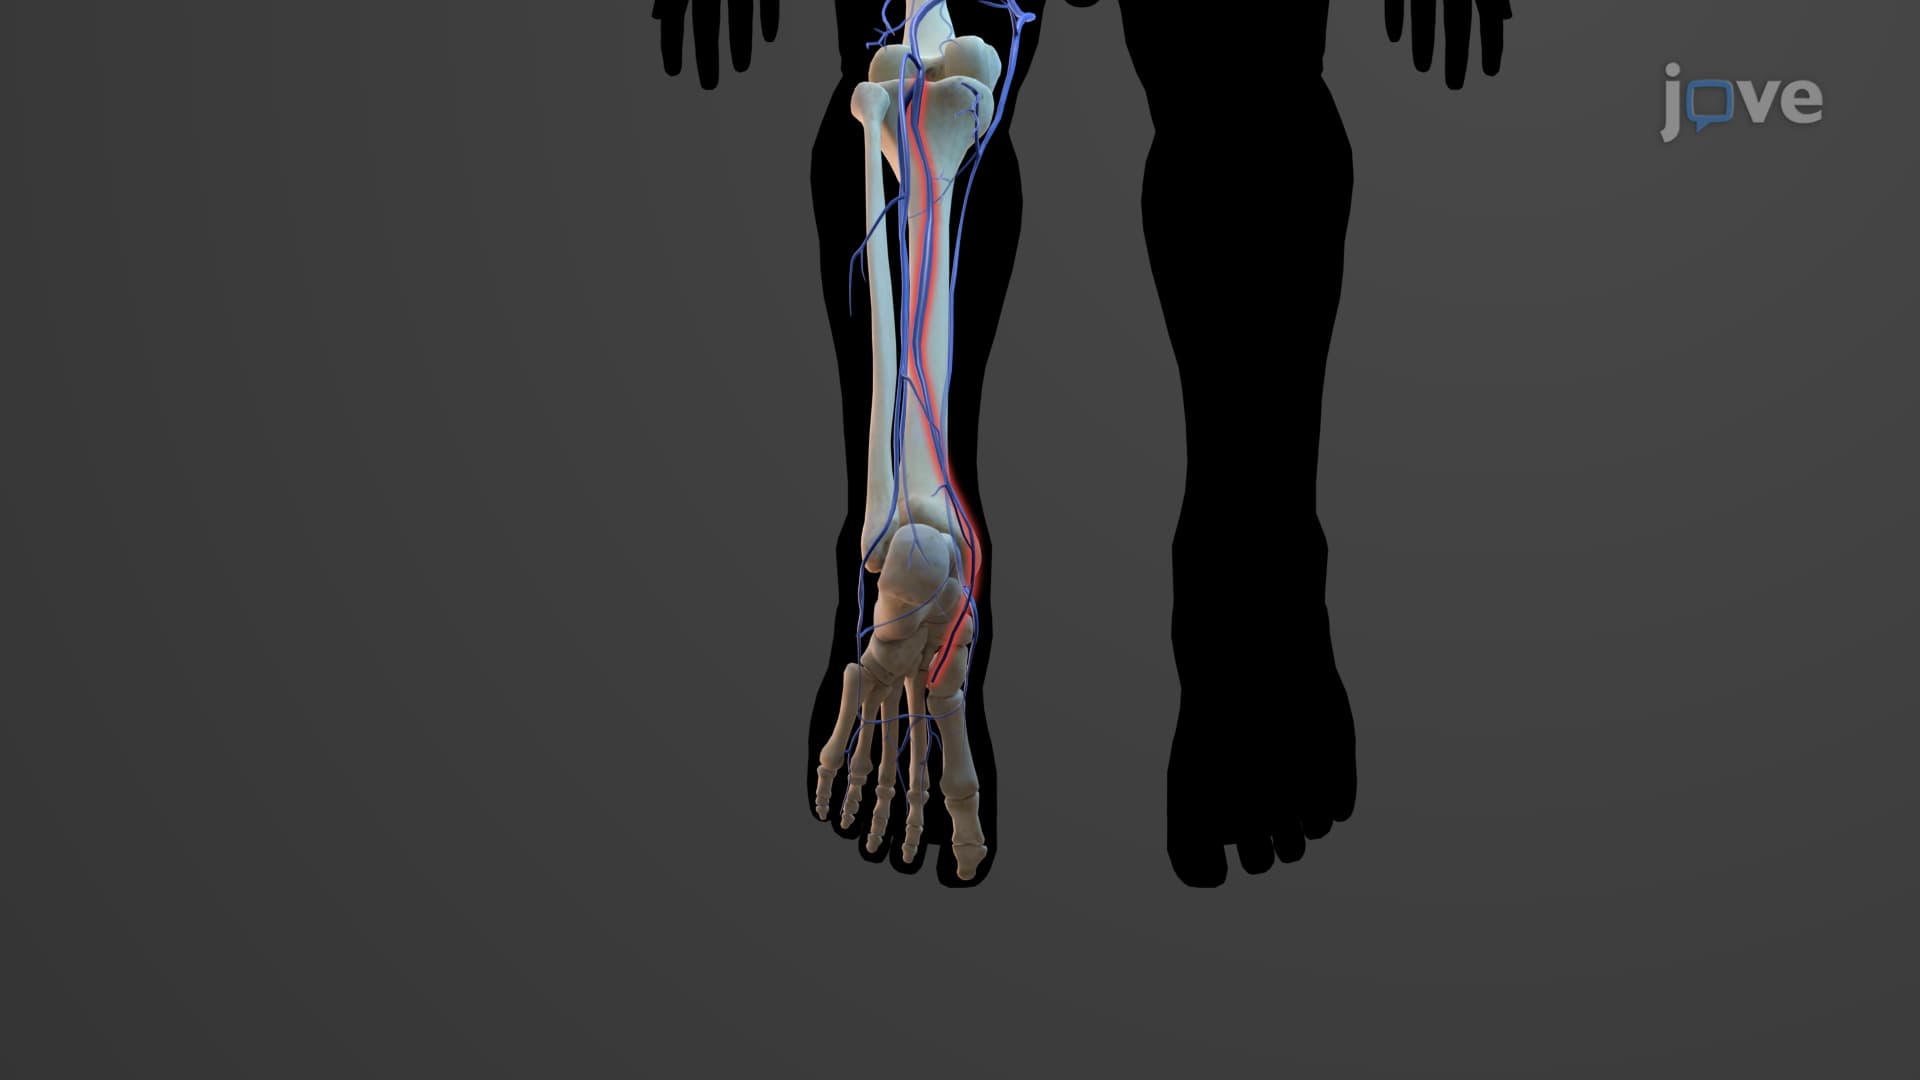
Veins of Lower Limbs
Formed by the union of the medial and lateral plantar veins, the posterior tibial vein, rising through the calf muscle, assimilates the fibular vein. The anterior tibial vein, a superior extension of the foot's dorsalis pedis vein, merges with the posterior tibial vein at the...
 01:27
Peripheral Artery Disease III: Interprofessional Care
 01:26
Varicose Veins II: Diagnostic Studies and Interprofessional Care
 01:29
Venous Thrombosis III: Interprofessional Care
 01:30
Venous Thrombosis IV: Nursing Management