Related Experiment Video
Updated: Aug 13, 2026


Leprdb Mouse Model of Type 2 Diabetes: Pancreatic Islet Isolation and Live-cell 2-Photon Imaging Of Intact Islets
Published on: May 11, 2015
Amylin and the amylin gene: structure, function and relationship to islet amyloid and to diabetes mellitus
G J Cooper1, A J Day, A C Willis
1Department of Biochemistry, University of Oxford, U.K.

Abstract:
Amylin, the major peptide component of the islet amyloid commonly found in the pancreases of patients with type 2 (non-insulin-dependent) diabetes mellitus (NIDDM), is a recently discovered islet polypeptide. This peptide has many structural and functional features suggesting that it is a novel hormone, which may control carbohydrate metabolism in partnership with insulin and other glucoregulatory factors. Amylin is synthesised in, and probably secreted from, the beta-cells of the islets of Langerhans, where it has recently been immunolocalised to secretory granules. DNA cloning studies indicate that in the human and the rat, amylin is generated from a precursor, preproamylin, which displays a typical signal peptide followed by a small prohormone-like sequence containing the amylin sequence. The presence of the signal peptide suggests that amylin is secreted and plays a physiological role. Amylin is probably generated by proteolytic processing similar to that for proinsulin and other islet prohormones. The human amylin gene encodes the complete polypeptide precursor in two exons which are separated by an intron of approx. 5 kb, and is located on chromosome 12. Amylin is a potent modulator of glycogen synthesis and glucose uptake in skeletal muscle, and is capable of inducing an insulin-resistant state in this tissue in vitro, and perhaps also in the liver in vivo. In normal metabolism, amylin could act in concert with insulin as a signal for the body to switch the site of carbohydrate disposal from glycogen to longer-term stores in adipose tissue, by making skeletal muscle relatively insulin-resistant, whilst at the same time leaving rates of insulin-stimulated carbohydrate metabolism in adipose tissue unaltered. Several lines of evidence now implicate elevated amylin levels in the pathogenic mechanisms underlying NIDDM, and suggest to us that the obesity which frequently accompanies this syndrome is a result of, rather than a risk factor for, NIDDM. Following the beta-cell destruction which occurs in type 1 (insulin-dependent) diabetes mellitus (IDDM), it is probable that amylin secretion disappears in addition to that of insulin. As patients with insulin-treated IDDM frequently experience problems with hypoglycaemia, and as amylin acts to modulate the action of insulin in various tissues, it is possible that amylin deficiency may contribute to morbidity in insulin-treated IDDM, perhaps through the loss of a natural damping mechanism which guards against hypoglycaemia under conditions of normal physiology.


Related Concept Videos
 01:22
Diabetes Mellitus: Overview and Type I Subtype
Type 1 diabetes is an autoimmune disease in which the immune system mistakenly attacks and destroys the insulin-producing beta cells in the pancreas. As a result, the body is unable to produce sufficient insulin, and individuals with...
 01:27
Glucose Homeostasis: Pancreatic Islets and Insulin Secretion
Insulin and C-peptide are co-secreted in...
 01:28
Insulin: The Receptor and Signaling Pathways
 01:25
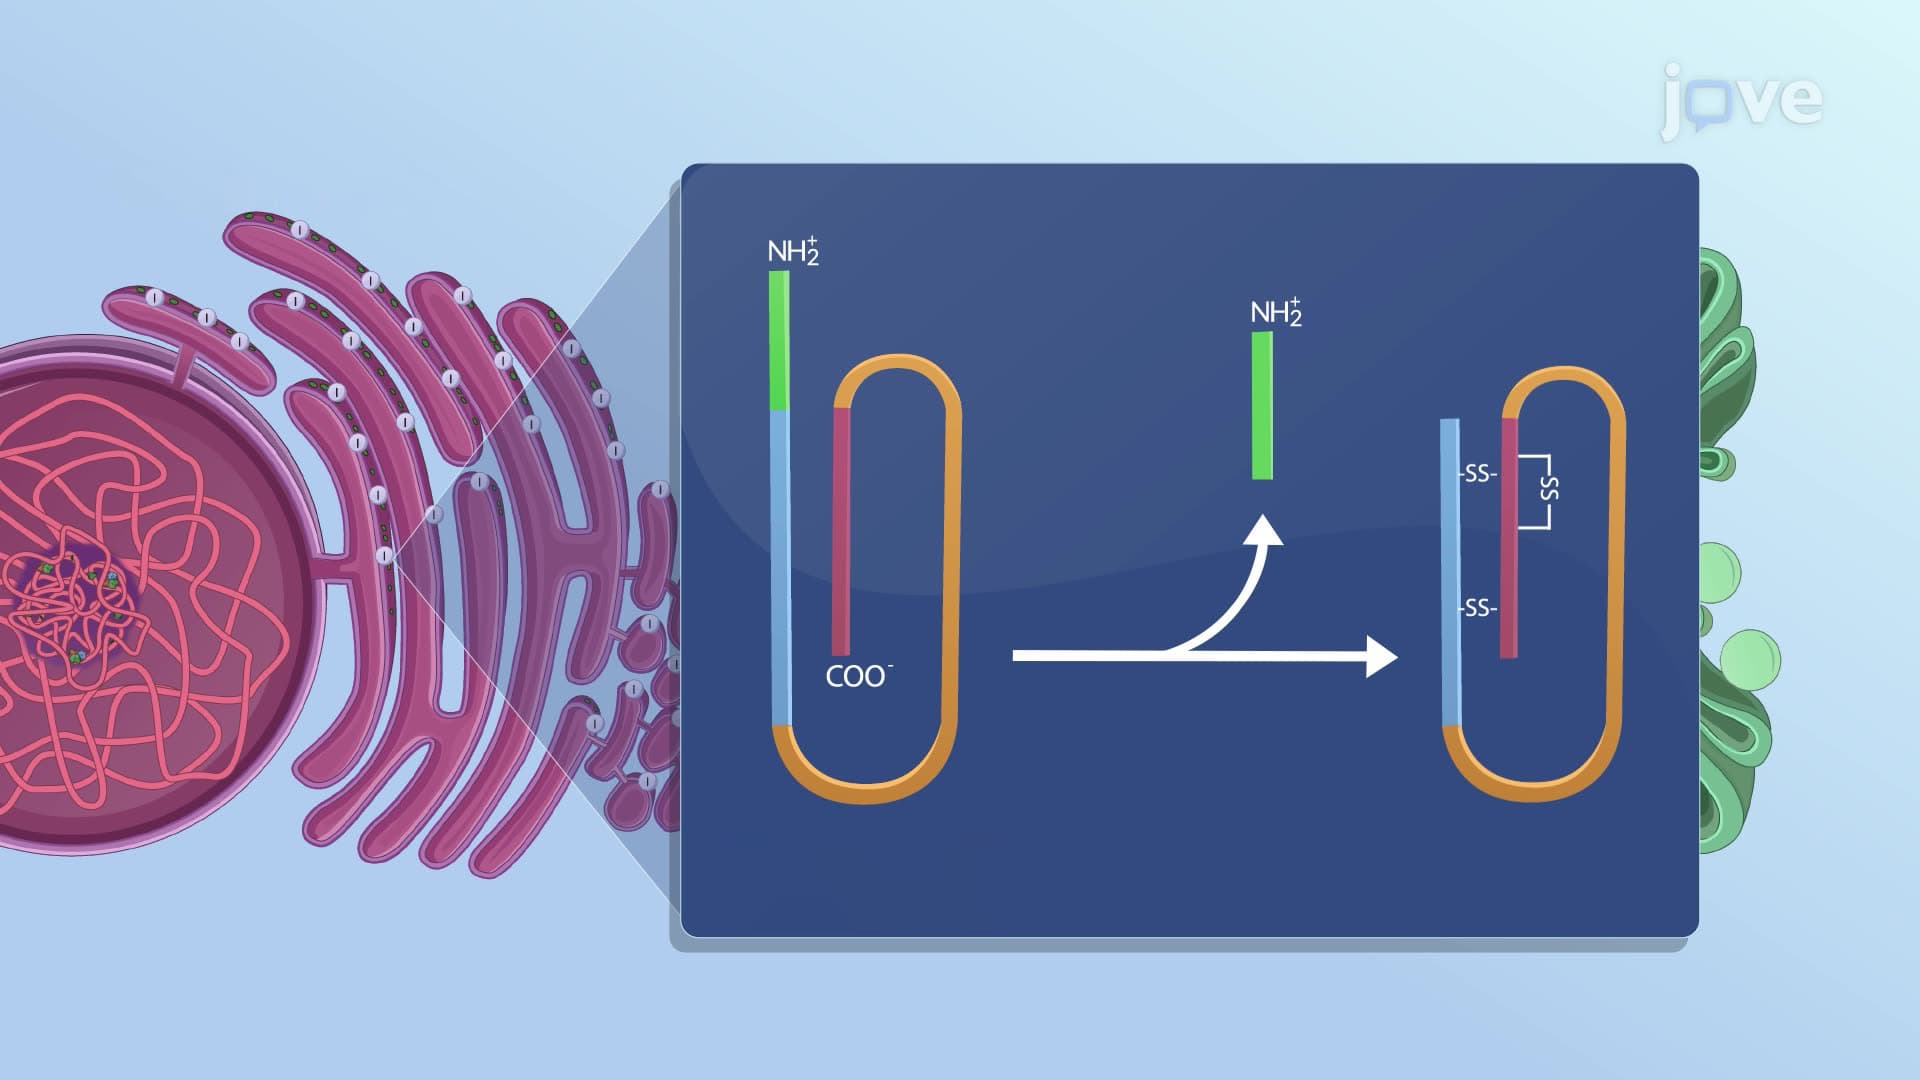
Insulin: Biosynthesis, Chemistry, and Preparation
Damage or functional impairment of β-cells inhibits insulin production, leading to diabetes. Diabetes treatment primarily uses...
 01:26
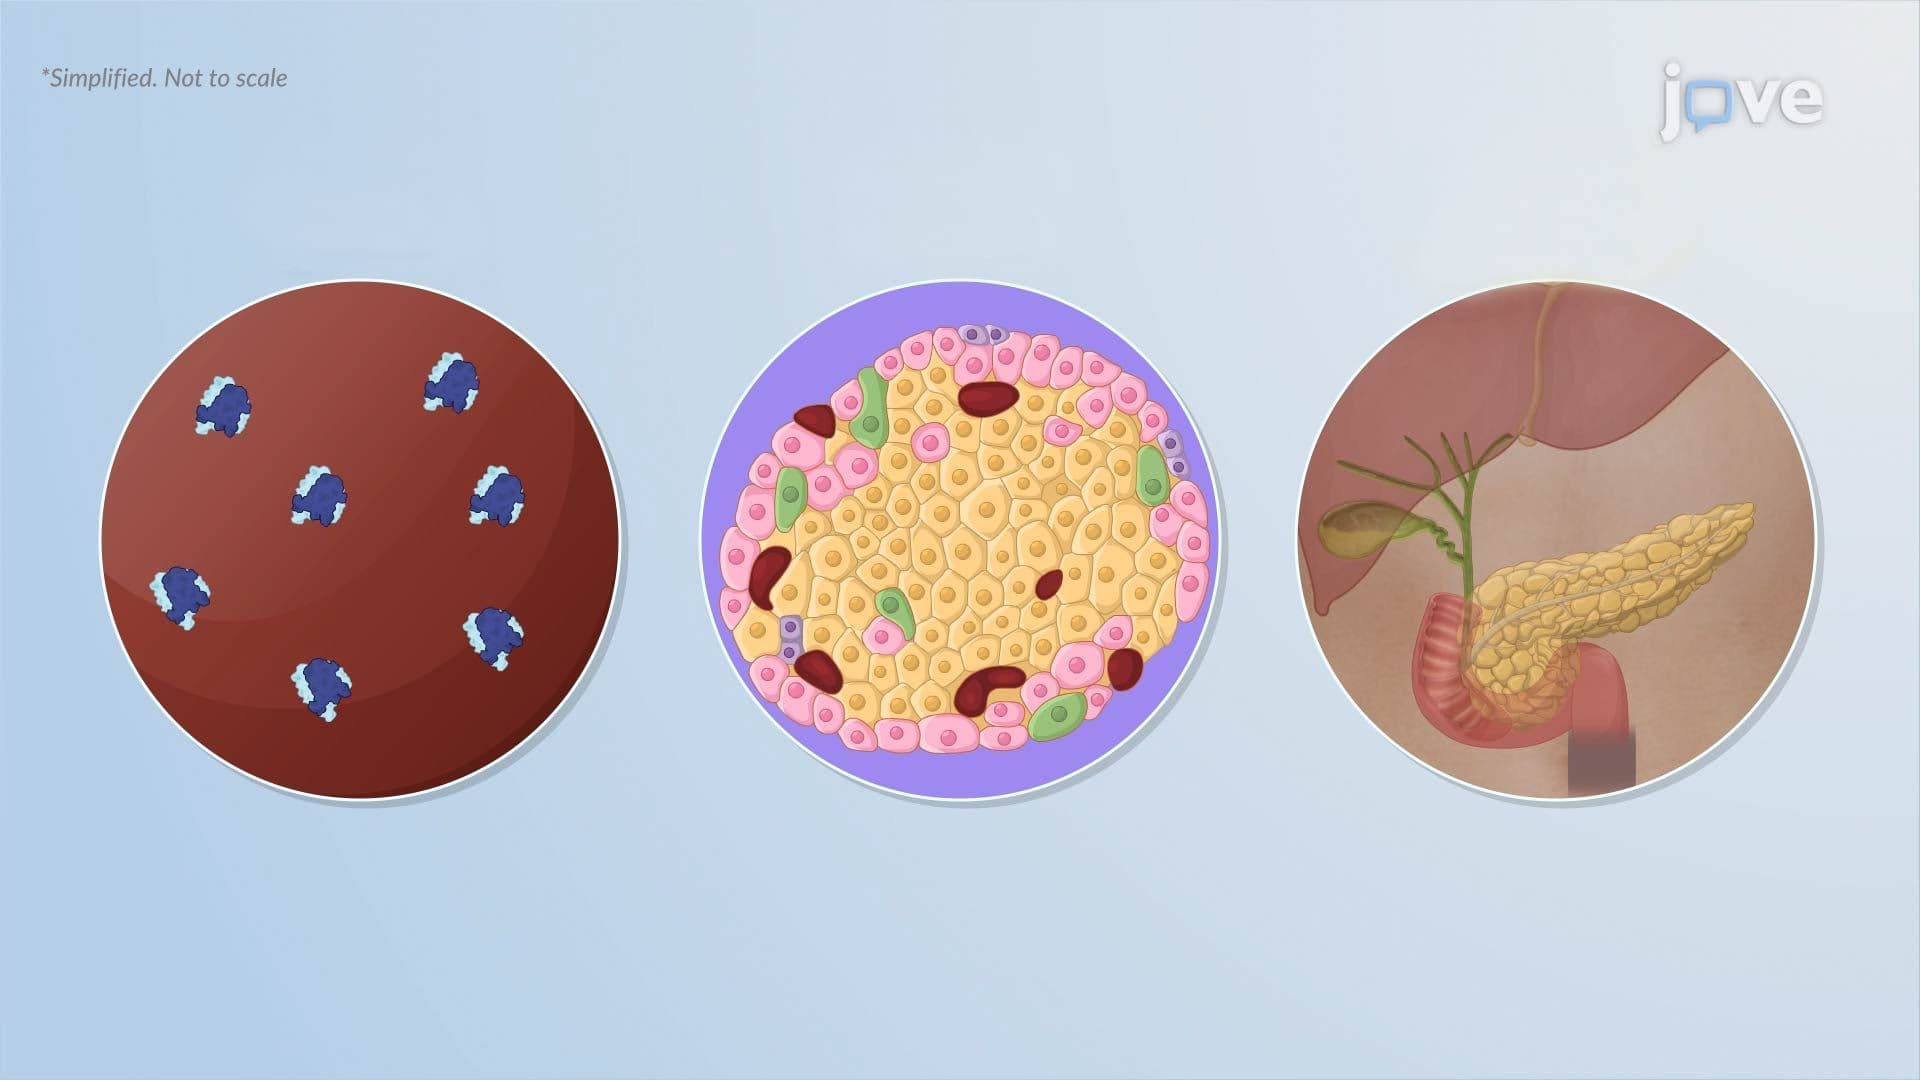
Diabetes Mellitus: Introduction
 01:26
Type I Diabetes II: Pathophysiology