Related Experiment Video
Updated: Mar 23, 2026


Modified Octopus Technique for Thoracoabdominal Aortic Aneurysm
Published on: August 1, 2025
Characteristics and Outcomes of Ascending Versus Descending Thoracic Aortic Aneurysms
Joshua S Vapnik1, Joon Bum Kim2, Eric M Isselbacher1
1Massachusetts General Hospital Thoracic Aortic Center, Harvard Medical School, Boston, Massachusetts; Division of Cardiology, Harvard Medical School, Boston, Massachusetts.

Abstract:
Thoracic aortic aneurysms (TAs) occur in reproducible patterns, but etiologic factors determining the anatomic distribution of these aneurysms are not well understood. This study sought to gain insight into etiologic differences and clinical outcomes associated with repetitive anatomic distributions of TAs. From 3,247 patients registered in an institutional Thoracic Aortic Center database from July 1992 to August 2013, we identified 844 patients with full aortic dimensional imaging by computerized axial tomography or magnetic resonance imaging scan (mean age 62.8 ± 14 years, 37% women, median follow-up 40 months) with TA diameter >4.0 cm and without evidence of previous aortic dissection. Patient demographic and imaging data were analyzed in 3 groups: isolated ascending thoracic aortic aneurysms (AAs; n = 628), isolated descending TAs (DTAs; n = 130), and combined AA and DTA (mixed thoracic aortic aneurysm, MTA; n = 86). Patients with DTA had more hypertension (82% vs 59%, p <0.001) and a higher burden of atherosclerosis (88% vs 9%, p <0.001) than AA. Conversely, patients with isolated AA were younger (59.5 ± 13.5 vs 71.0 ± 11.8 years, p <0.001) and contained almost every case of overt, genetically triggered TA. Patients with isolated DTA were demographically indistinguishable from patients with MTA. In follow-up, patients with DTA/MTA experienced more aortic events (aortic dissection/rupture) and had higher mortality than patients with isolated AA. In multivariate analysis, aneurysm size (odds ratio 1.1, 95% CI 1.07 to 1.16, p <0.001) and the presence of atherosclerosis (odds ratio 5.7, 95% CI 2.02 to 16.15, p <0.001) independently predicted adverse aortic events. We find that DTA with or without associated AA appears to be a disease more highly associated with atherosclerosis, hypertension, and advanced age. In contrast, isolated AA appears to be a clinically distinct entity with a greater burden of genetically triggered disease.


Related Concept Videos
 01:21
Aneurysm II: Clinical Manifestations and Diagnostic Studies
 01:30
Aneurysm I: Introduction
 01:26
Aneurysm III: Interprofessional Care
 01:15
Aortic Regurgitation I: Introduction
 01:22
Aortic Regurgitation II: Clinical Features and Diagnostic Tests
 01:14
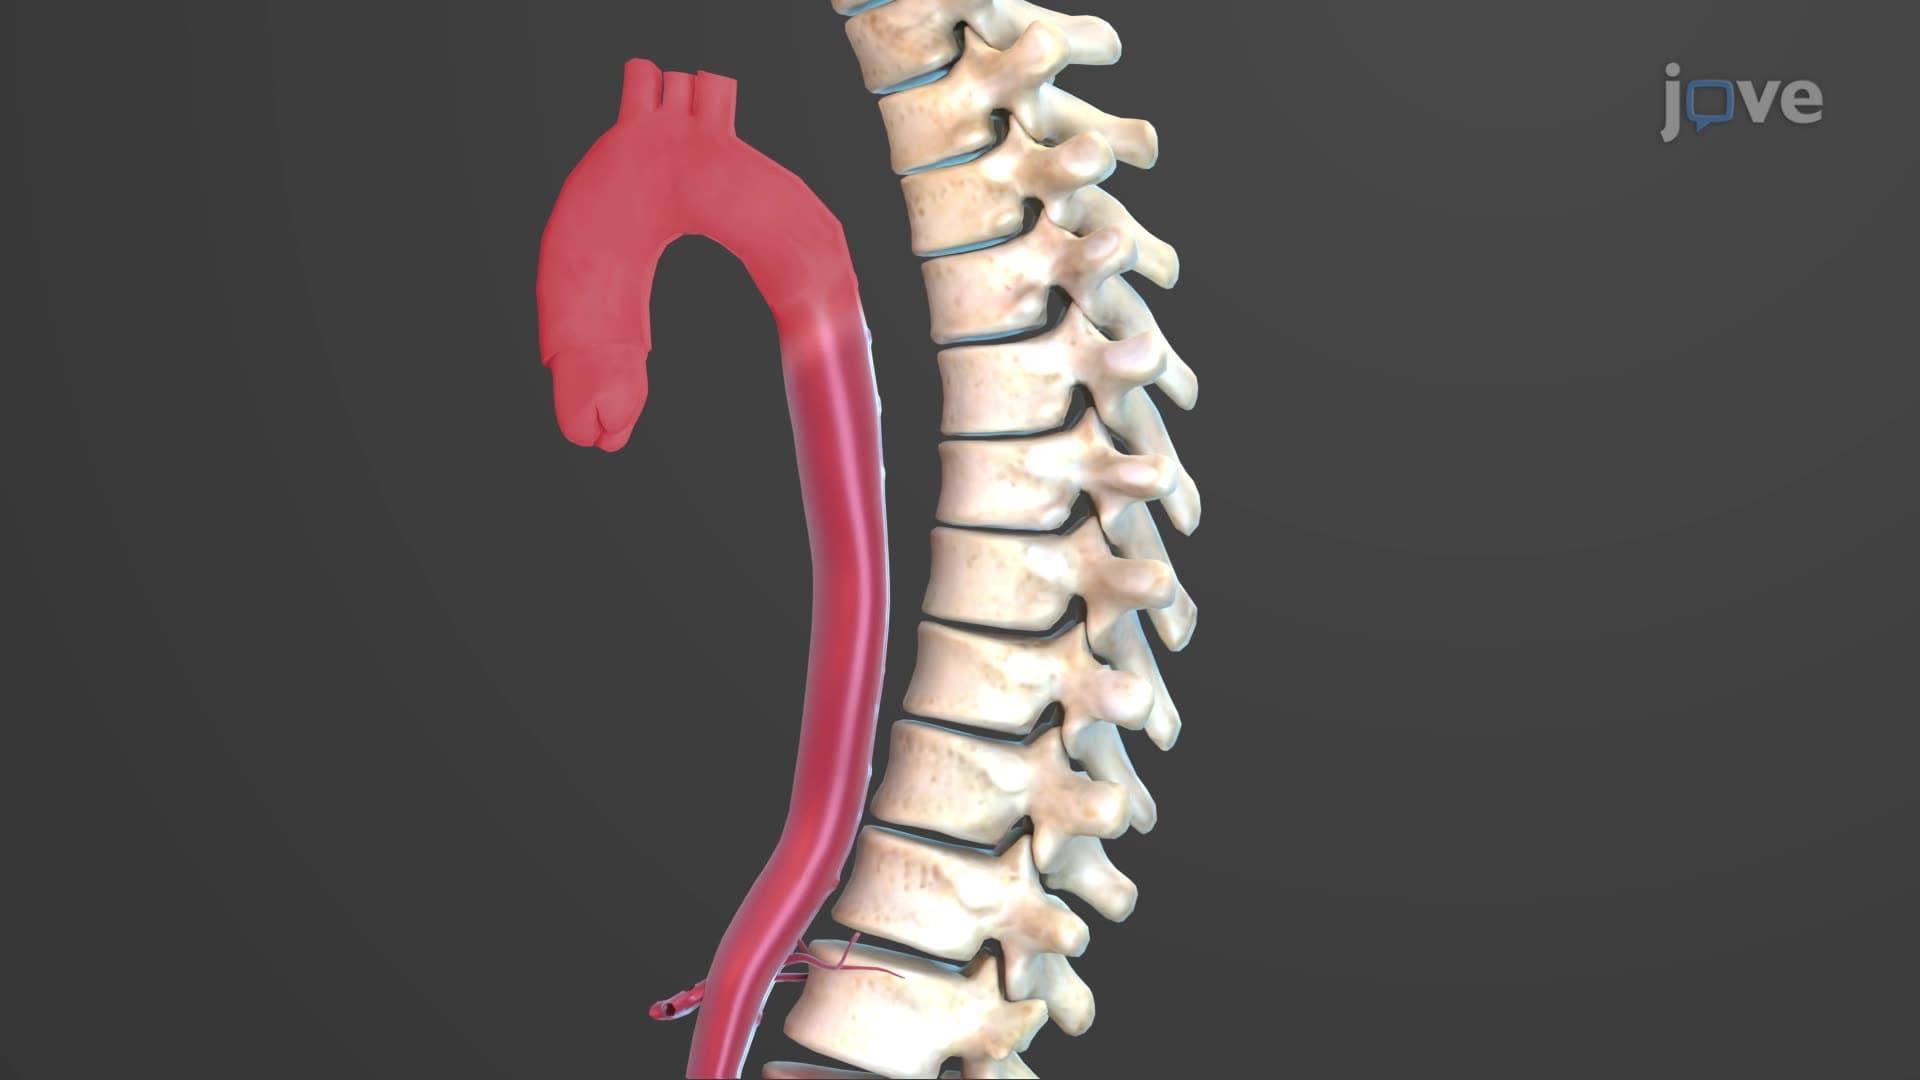
The Aorta
The average diameter of the aorta is approximately 2-3 cm, but the size can vary depending on the section of the aorta and the individual's age, sex, and body size. The aorta is...