Related Experiment Video
Updated: Mar 23, 2026
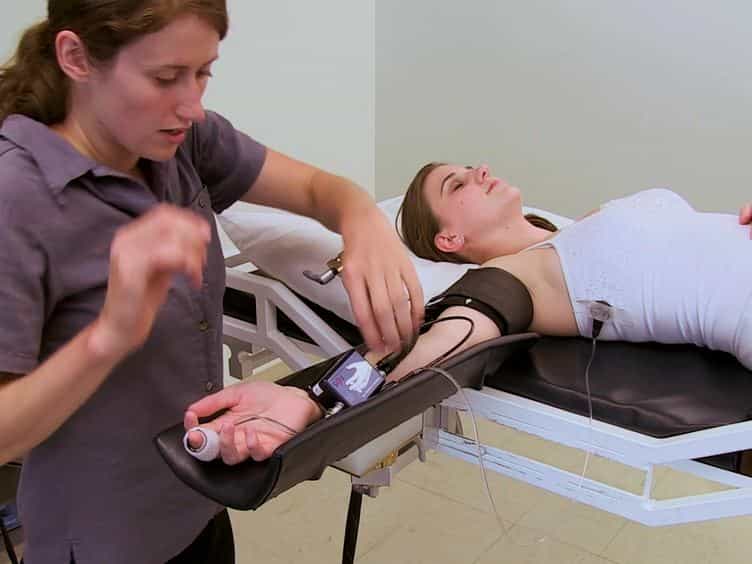

Tilt Testing with Combined Lower Body Negative Pressure: a "Gold Standard" for Measuring Orthostatic Tolerance
Published on: March 21, 2013
Reliability of Clinical Assessments in Older Adults With Syncope or Near Syncope
Daniel K Nishijima1, Amber L Laurie2, Robert E Weiss3
1Department of Emergency Medicine, UC Davis School of Medicine, Sacramento, CA. dnishijima@ucdavis.edu.

Objectives:
Clinical prediction models for risk stratification of older adults with syncope or near syncope may improve resource utilization and management. Predictors considered for inclusion into such models must be reliable. Our primary objective was to evaluate the inter-rater agreement of historical, physical examination, and electrocardiogram (ECG) findings in older adults undergoing emergency department (ED) evaluation for syncope or near syncope. Our secondary objective was to assess the level of agreement between clinicians on the patient's overall risk for death or serious cardiac outcomes.
Methods:
We conducted a cross-sectional study at 11 EDs in adults 60 years of age or older who presented with unexplained syncope or near syncope. We excluded patients with a presumptive cause of syncope (e.g., seizure) or if they were unable or unwilling to follow-up. Evaluations of the patient's past medical history and current medication use were completed by treating provider and trained research associate pairs. Evaluations of the patient's physical examination and ECG interpretation were completed by attending/resident, attending/advanced practice provider, or attending/attending pairs. All evaluations were blinded to the responses from the other rater. We calculated the percent agreement and kappa statistic for binary variables. Inter-rater agreement was considered acceptable if the kappa statistic was 0.6 or higher.
Results:
We obtained paired observations from 255 patients; mean (±SD) age was 73 (±9) years, 137 (54%) were male, and 204 (80%) were admitted to the hospital. Acceptable agreement was achieved in 18 of the 21 (86%) past medical history and current medication findings, none of the 10 physical examination variables, and three of the 13 (23%) ECG interpretation variables. There was moderate agreement (Spearman correlation coefficient, r = 0.40) between clinicians on the patient's probability of 30-day death or serious cardiac outcome, although as the probability increased, there was less agreement.
Conclusions:
Acceptable agreement between raters was more commonly achieved with historical rather than physical examination or ECG interpretation variables. Clinicians had moderate agreement in assessing the patient's overall risk for a serious outcome at 30 days. Future development of clinical prediction models in older adults with syncope should account for variability of assessments between raters and consider the use of objective clinical variables.


Related Concept Videos
 01:23
Assessment of the Cardiovascular System I: Subjective Data
Initial Enquiry
Ask the patient about their primary concern and thoroughly explore all reported symptoms.
Medical History
Investigate past illnesses affecting the cardiovascular system, such as angina, anemia, rheumatic fever, congenital heart disease, stroke, thrombophlebitis, dysrhythmias, varicosities
Inquire about symptoms...
 01:30
Dysrhythmias V: Evaluating Dysrhythmias
 01:27
Pharmacodynamics in Geriatric Patients: Effects of Age
 01:28
Special considerations while measuring blood pressure
Monitoring Both Arms:
Monitoring BP in both arms during the initial assessment is advisable, as the systolic value may differ by five to ten mm Hg between arms. For subsequent BP assessments, use the arm with the higher reading.
 01:29
Angina III: Clinical Manifestations and Assessment