Related Experiment Video
Updated: Mar 23, 2026


Evaluation of Patients' Posture and Gait Profile After Lumbar Fusion Surgery by Video Rasterstereography and Treadmill Gait Analysis
Published on: March 23, 2019
Pelvic Floor Symptoms and Spinal Curvature in Women
Isuzu Meyer1, Tatum A McArthur, Ying Tang
1From the *Division of Urogynecology and Pelvic Reconstructive Surgery, Department of Obstetrics and Gynecology, †Department of Radiology, ‡Department of Biostatistics, University of Alabama at Birmingham, Birmingham, AL; §Center for Pelvic and Women's Health, Marathon Physical therapy and Sports Medicine, LLC, Norton, MA ∥Division of Clinical Immunology and Rheumatology, UABH Osteoporosis Prevention and Treatment Clinic, University of Alabama at Birmingham, Birmingham, AL.

Objectives:
To characterize the association between thoracic (T) and lumbar (L) spinal curvature and pelvic floor (PF) symptoms (pelvic organ prolapse, urinary incontinence [UI], fecal incontinence [FI]).
Methods:
Of women undergoing a bone mineral density scan from January 2007 to October 2010, patients who completed PF symptom questionnaires and had T and/or L spine radiographs or computed tomography examinations within 3 years of questionnaire completion were included in this study. The spine angles were measured using the Cobb angle method. The T and L curvatures were categorized as hypokyphosis (<20°), normal T kyphosis (20-40°), hyperkyphosis (>40°), hypolordosis (<40°), normal L lordosis (40-70°), and hyperlordosis (>70°). The presence and type of UI were identified with the 3 Incontinence Questionnaire and FI with the Modified Manchester Questionnaire. Pelvic organ prolapse was defined as a positive response to the presence of a bulge question from the PF Distress Inventory-20.
Results:
Of 1665 eligible women, 824 and 302 (mean age 64 ± 10 for both) had T and L spine images, respectively. No differences in PF symptoms were observed in the T or L spine groups categorized by hypo-, normal, and hyperkyphosis/lordosis except for urgency UI being more prevalent in the hypolordosis group (P = 0.01). However, upon further characterization using logistic regression, no association was noted between PF symptoms and T or L spine angles; no differences in the mean angles were found between women with versus without PF symptoms (P ≥ 0.05).
Conclusions:
The current study shows that the T and L spinal curvatures are not associated with the presence of PF symptoms.

Related Concept Videos
 01:16
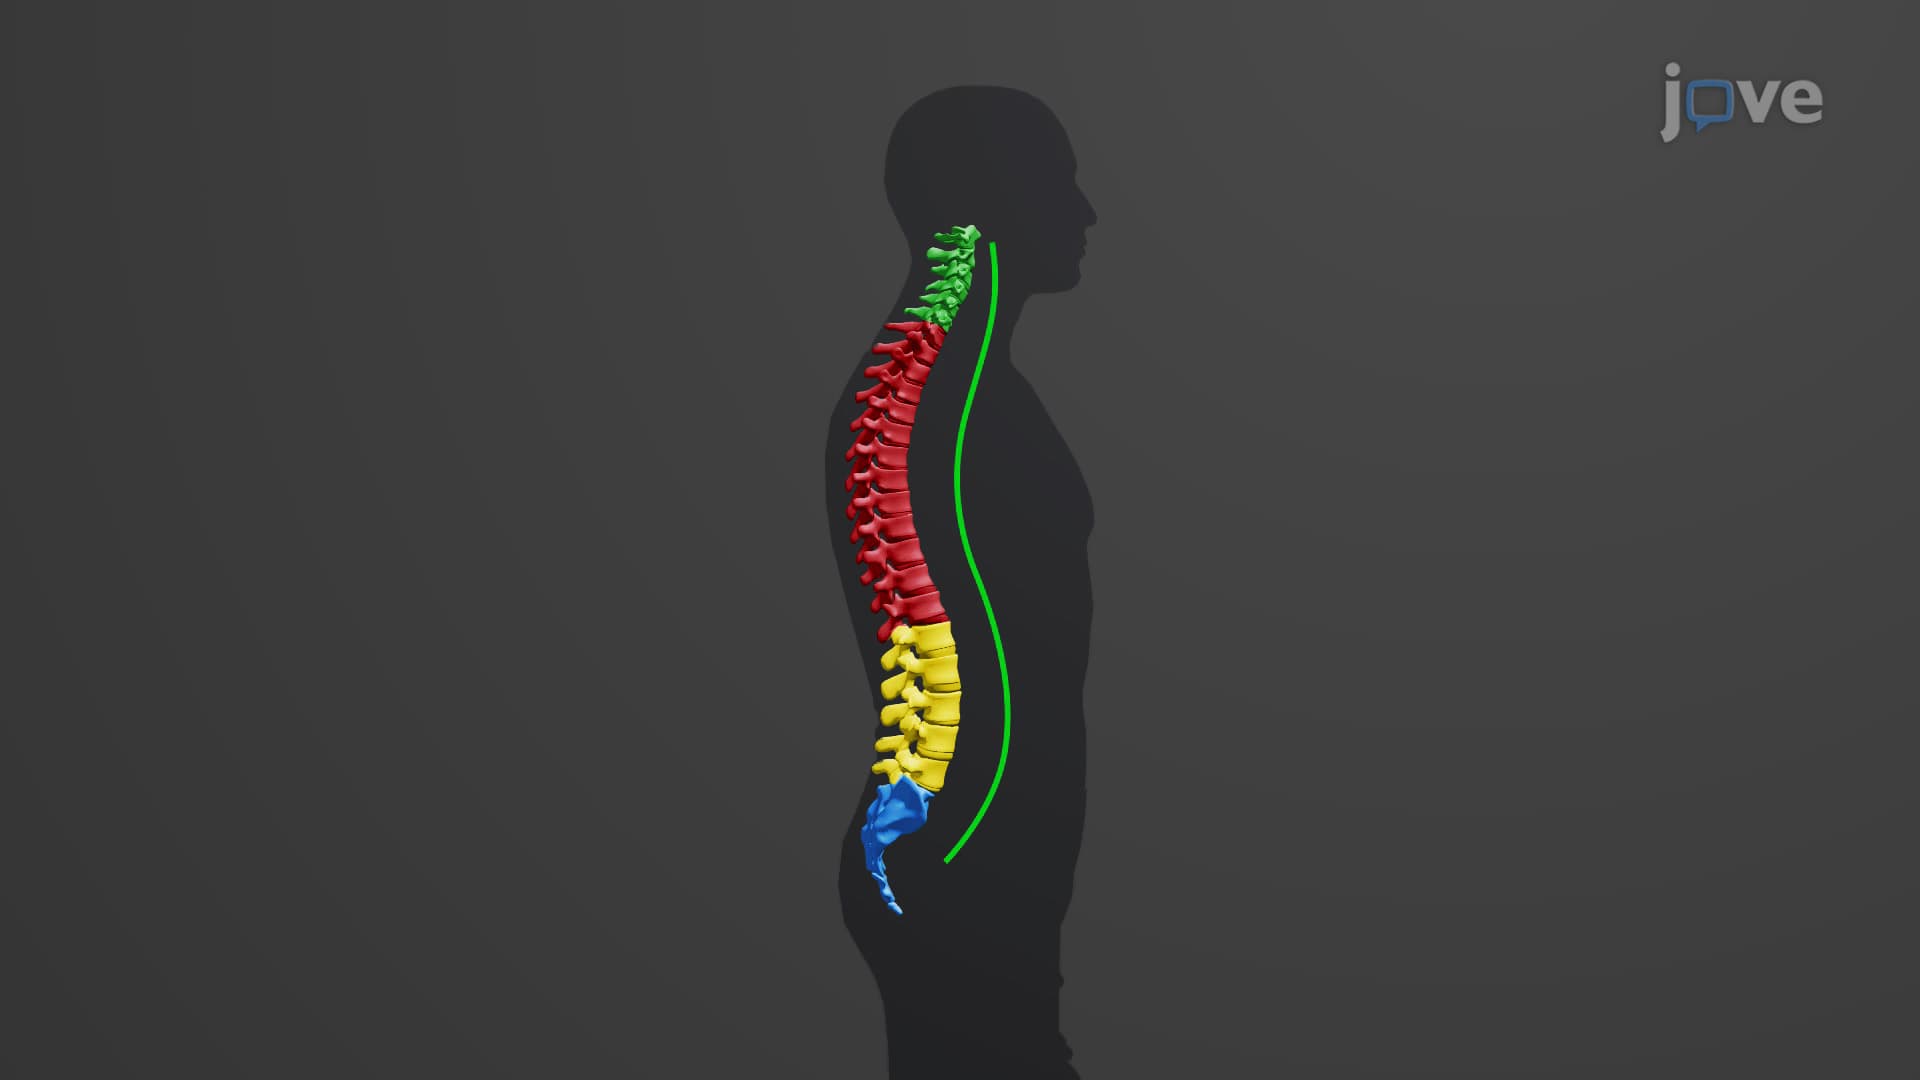
Vertebral Column: Regions and Curvature
Regions of the Vertebral Column
In an adult, the spine is subdivided into five regions: the cervical, the thoracic, the lumbar, the sacral, and the coccygeal region. The spine initially develops as a series of 33 vertebrae; after 20 years of age, the nine bones in the sacral region, five sacral, and four coccygeal bones fuse to form...
 01:24
Disorders of the Female Reproductive System
 01:26
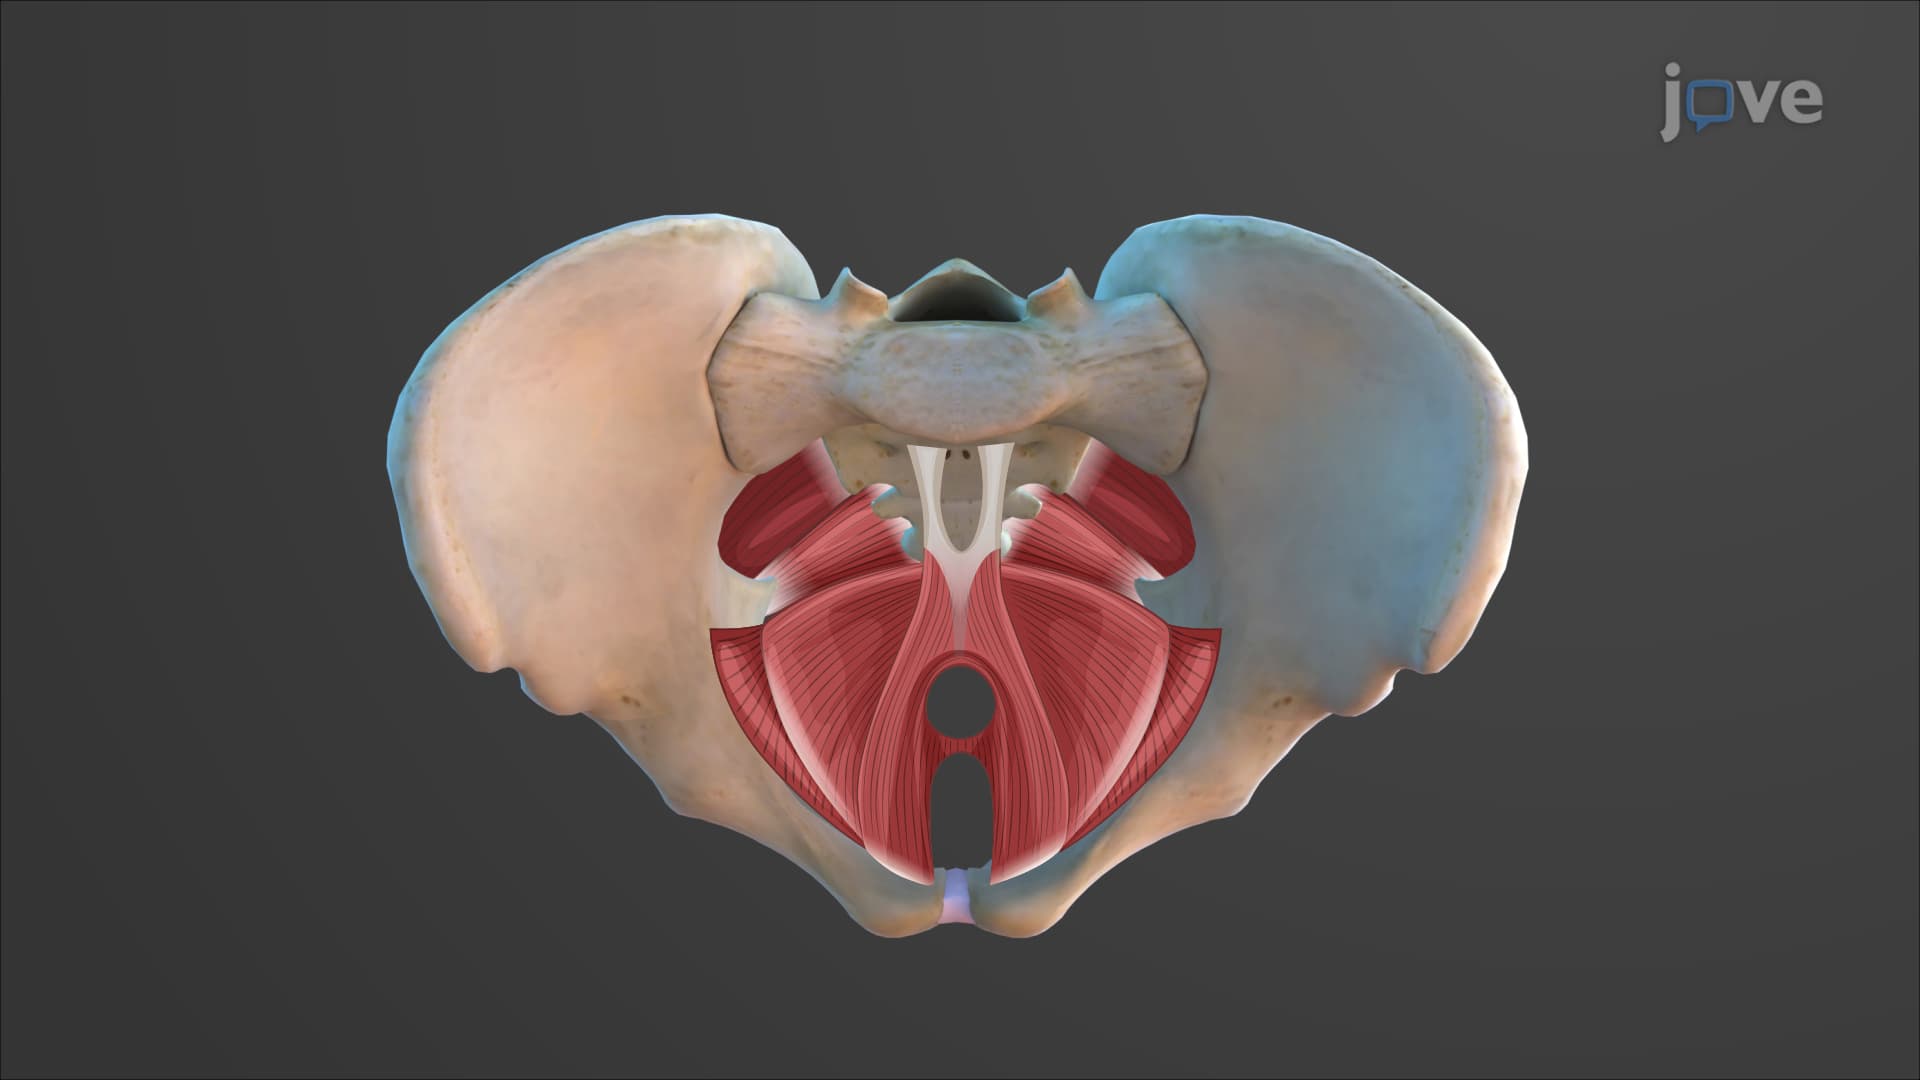
Muscles of the Pelvic Floor and Perineum
Perineal Layer
The perineum is a diamond-shaped area below the pelvic diaphragm, divided into an anterior urogenital triangle that contains the external genitals and a posterior anal triangle housing the anus. The urogenital...
 01:22
Appendicitis-I: Introduction
Etiology: Appendicitis can arise from various causes, primarily rooted in the obstruction of the appendix lumen. Factors contributing to this obstruction include fecal accumulation, lymphoid hyperplasia and, in...
 01:26
Nursing Assessment of the Genitourinary System II: Inspection and Palpation
 01:19
Abdominal Regions and Quadrants
The simpler quadrants approach, which is more commonly used in medicine, subdivides the cavity with one horizontal and one vertical line that intersects at the patient's umbilicus (navel). The four...