Related Experiment Video
Updated: Mar 23, 2026
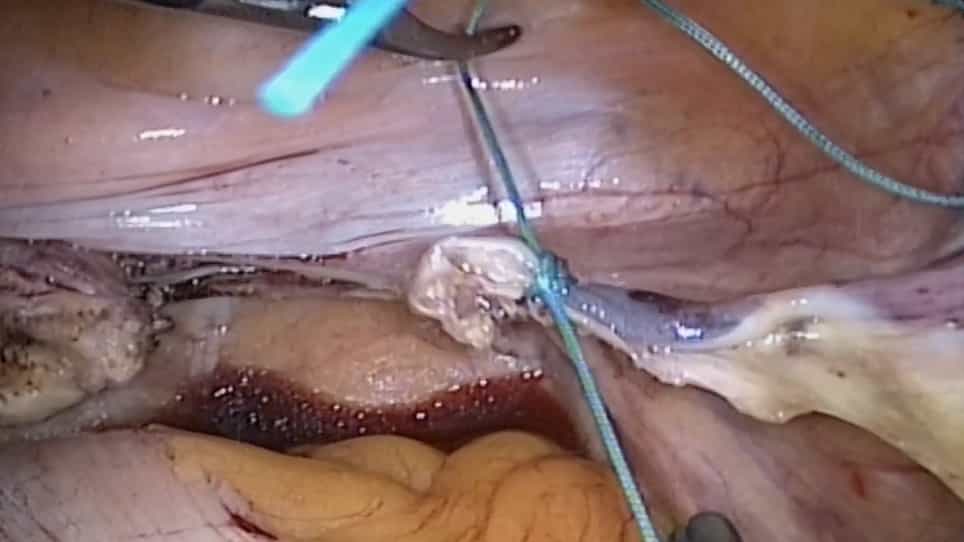

Laparoscopic Non-Mesh Cerclage Pectopexy for Pelvic Organ Prolapse
Published on: September 13, 2022
Cervical Cerclage During Periviability: Can We Stabilize a Moving Target?
Joshua D Dahlke1, Jeffrey D Sperling, Suneet P Chauhan
1Nebraska Methodist Women's Hospital and Perinatal Center, Omaha, Nebraska; the Department of Obstetrics & Gynecology, Warren Alpert Medical School of Brown University, Women & Infants Hospital, Providence, Rhode Island; the Division of Maternal-Fetal Medicine, Department of Obstetrics, Gynecology, and Reproductive Sciences, UT Health-University of Texas Medical School at Houston, Texas; and the Division of Maternal-Fetal Medicine, Department of Obstetrics and Gynecology, Sidney Kimmel Medical College of Thomas Jefferson University, Philadelphia, Pennsylvania.

The American College of Obstetricians and Gynecologists and the Society for Maternal-Fetal Medicine recently published consensus guidelines on periviable birth recommending that obstetric interventions (antenatal corticosteroids, tocolysis, magnesium sulfate, antibiotics for preterm premature rupture of membranes or group B streptococcus prophylaxis, and cesarean delivery for fetal indications) may be considered at 23 0/7 weeks of gestation and neonatal resuscitation at 22 0/7 weeks of gestation. Cervical cerclage significantly decreases preterm delivery and improves perinatal outcomes in women with a singleton pregnancy, prior spontaneous preterm birth, and transvaginal cervical length less than 25 mm before 24 0/7 weeks of gestation or in women who experience painless cervix dilation in the second trimester. Randomized trials assessing ultrasonogram-indicated and physical examination-indicated cerclage report a procedure-related complication rate of 0.3% and 0.9%, respectively. If previability is a requisite for receiving a cerclage, an increasing subset of women may not be afforded an intervention that has known benefit, because obstetric and neonatal interventions are likely to occur at earlier gestational ages. Given the low procedure-related complication rate demonstrated in randomized trials, appropriately selected women should continue to be offered the procedure up to 24 0/7 weeks of gestation. Based on current evidence, cerclage placed after 24 0/7 weeks of gestation cannot be recommended, and future inquiry in the form of a well-designed randomized trial after this gestational age should be considered. The goal of this commentary is to review the history of cerclage and discuss the indications, risks, benefits, and implications on future research of this procedure as it relates to gestational age during periviability.
The American College of Obstetricians and Gynecologists and the Society for Maternal-Fetal Medicine recently published consensus guidelines on periviable birth recommending that obstetric interventions (antenatal corticosteroids, tocolysis, magnesium sulfate, antibiotics for preterm premature rupture of membranes or group B streptococcus prophylaxis, and cesarean delivery for fetal indications) may be considered at 23 0/7 weeks of gestation and neonatal resuscitation at 22 0/7 weeks of gestation. Cervical cerclage significantly decreases preterm delivery and improves perinatal outcomes in women with a singleton pregnancy, prior spontaneous preterm birth, and transvaginal cervical length less than 25 mm before 24 0/7 weeks of gestation or in women who experience painless cervix dilation in the second trimester. Randomized trials assessing ultrasonogram-indicated and physical examination-indicated cerclage report a procedure-related complication rate of 0.3% and 0.9%, respectively. If previability is a requisite for receiving a cerclage, an increasing subset of women may not be afforded an intervention that has known benefit, because obstetric and neonatal interventions are likely to occur at earlier gestational ages. Given the low procedure-related complication rate demonstrated in randomized trials, appropriately selected women should continue to be offered the procedure up to 24 0/7 weeks of gestation. Based on current evidence, cerclage placed after 24 0/7 weeks of gestation cannot be recommended, and future inquiry in the form of a well-designed randomized trial after this gestational age should be considered. The goal of this commentary is to review the history of cerclage and discuss the indications, risks, benefits, and implications on future research of this procedure as it relates to gestational age during periviability.
More Related Videos
 05:21
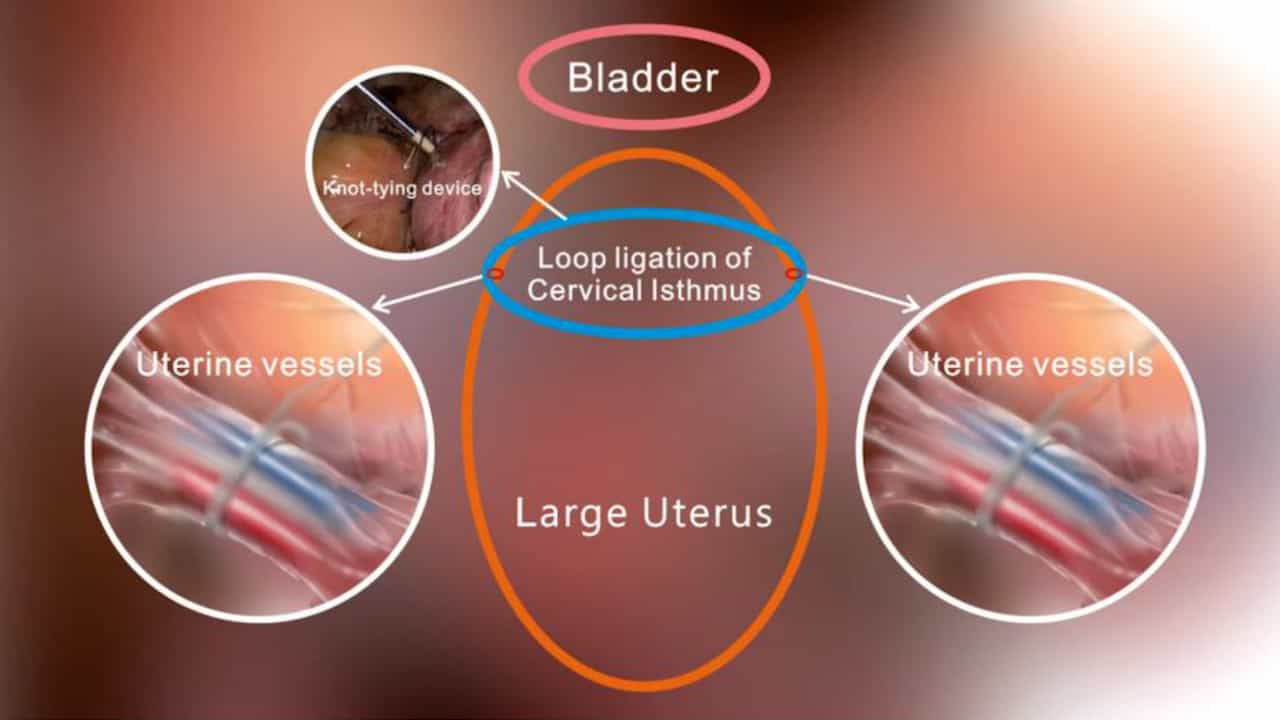
Laparoscopic Extracorporeal Knot-Tying for Uterine Vessel Occlusion during Hysterectomy with Cervical Cerclage in Large Uteri
Published on: September 12, 2025
 03:30
Author Spotlight: Advancing Pelvic Prolapse Treatment with a Non-Mesh Approach using Laparoscopic Pectopexy
Published on: October 25, 2024
Related Concept Videos
 01:18
Uterus and Cervix
The uterus is securely anchored within the pelvic cavity by paired broad ligaments on either side. It is further stabilized by three pairs...
 01:24
In Vitro Fertilization
The IVF process begins with ovarian stimulation, during which reproductive endocrinologists prescribe hormonal medications to stimulate the ovaries to produce multiple eggs instead of the single...
 01:16
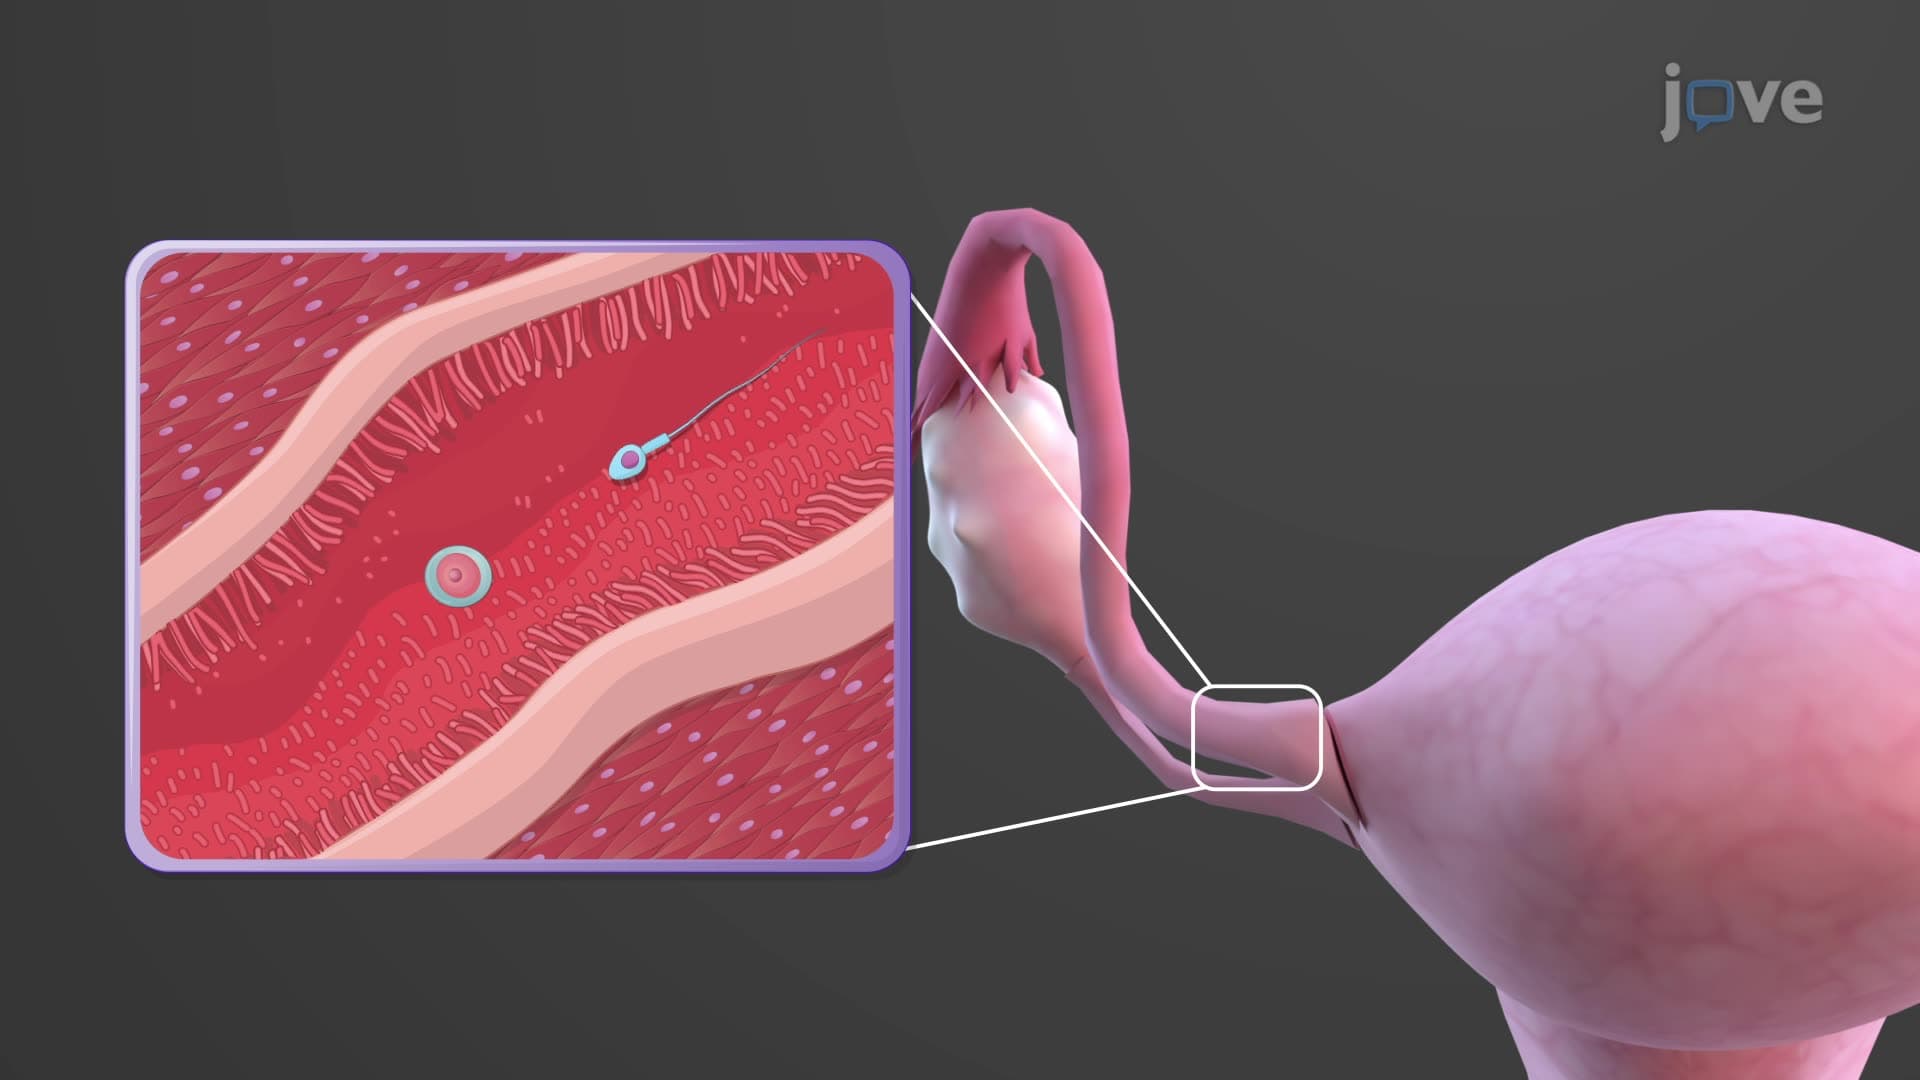
Uterine Tubes