Related Experiment Video
Updated: Mar 22, 2026
Deep Neuromuscular Blockade Leads to a Larger Intraabdominal Volume During Laparoscopy
Published on: June 25, 2013
Effects of pressure-controlled and volume-controlled ventilation on respiratory mechanics and systemic stress
Oznur Sen1, Tarik Umutoglu2, Nurdan Aydın1
1Department of Anesthesiology and Reanimation, Ministry of Health Haseki Training and Research Hospital, Istanbul, Turkey.

Abstract:
Pressure-controlled ventilation (PCV) is less frequently employed in general anesthesia. With its high and decelerating inspiratory flow, PCV has faster tidal volume delivery and different gas distribution. The same tidal volume setting, delivered by PCV versus volume-controlled ventilation (VCV), will result in a lower peak airway pressure and reduced risk of barotrauma. We hypothesized that PCV instead of VCV during laparoscopic surgery could achieve lower airway pressures and reduce the systemic stress response. Forty ASA I-II patients were randomly selected to receive either the PCV (Group PC, n = 20) or VCV (Group VC, n = 20) during laparoscopic cholecystectomy. Blood sampling was made for baseline arterial blood gases (ABG), cortisol, insulin, and glucose levels. General anesthesia with sevoflurane and fentanyl was employed to all patients. After anesthesia induction and endotracheal intubation, patients in Group PC were given pressure support to form 8 mL/kg tidal volume and patients in Group VC was maintained at 8 mL/kg tidal volume calculated using predicted body weight. All patients were maintained with 5 cmH2O positive-end expiratory pressure (PEEP). Respiratory parameters were recorded before and 30 min after pneumoperitonium. Assessment of ABG and sampling for cortisol, insulin and glucose levels were repeated 30 min after pneumoperitonium and 60 min after extubation. The P-peak levels observed before (18.9 ± 3.8 versus 15 ± 2.2 cmH2O) and during (23.3 ± 3.8 versus 20.1 ± 2.9 cmH2O) pneumoperitoneum in Group VC were significantly higher. Postoperative partial arterial oxygen pressure (PaO2) values are higher (98 ± 12 versus 86 ± 11 mmHg) in Group PC. Arterial carbon dioxide pressure (PaCO2) values (41.8 ± 5.4 versus 36.7 ± 3.5 mmHg) during pneumoperitonium and post-operative mean cortisol and insulin levels were higher in Group VC. When compared to VCV mode, PCV mode may improve compliance during pneumoperitoneum, improve oxygenation and reduce stress response postoperatively and may be more appropriate in patients having laparoscopic surgery.

Related Concept Videos
 01:23
Mechanical Ventilation II: Invasive Ventilation
Negative-Pressure Ventilators
Negative-pressure ventilators create a vacuum around the chest or body to draw air into the lungs, simulating breathing. This method does not require an...
 01:26
Endoscopic Procedures IV: Sigmoidoscopy and Laproscopy
Sigmoidoscopy
Sigmoidoscopy is a diagnostic procedure that uses a flexible sigmoidoscope equipped with a light source and camera to examine the rectum and sigmoid colon. The procedure involves inserting the tube through the anus...
 01:26
Endoscopic Studies II: Thoracocentesis
Description
Excess pleural fluid or air may accumulate in some respiratory disorders in the thoracic cavity. To treat pleural effusion, a physician conducts thoracentesis by carefully piercing the chest wall and entering...
 01:24
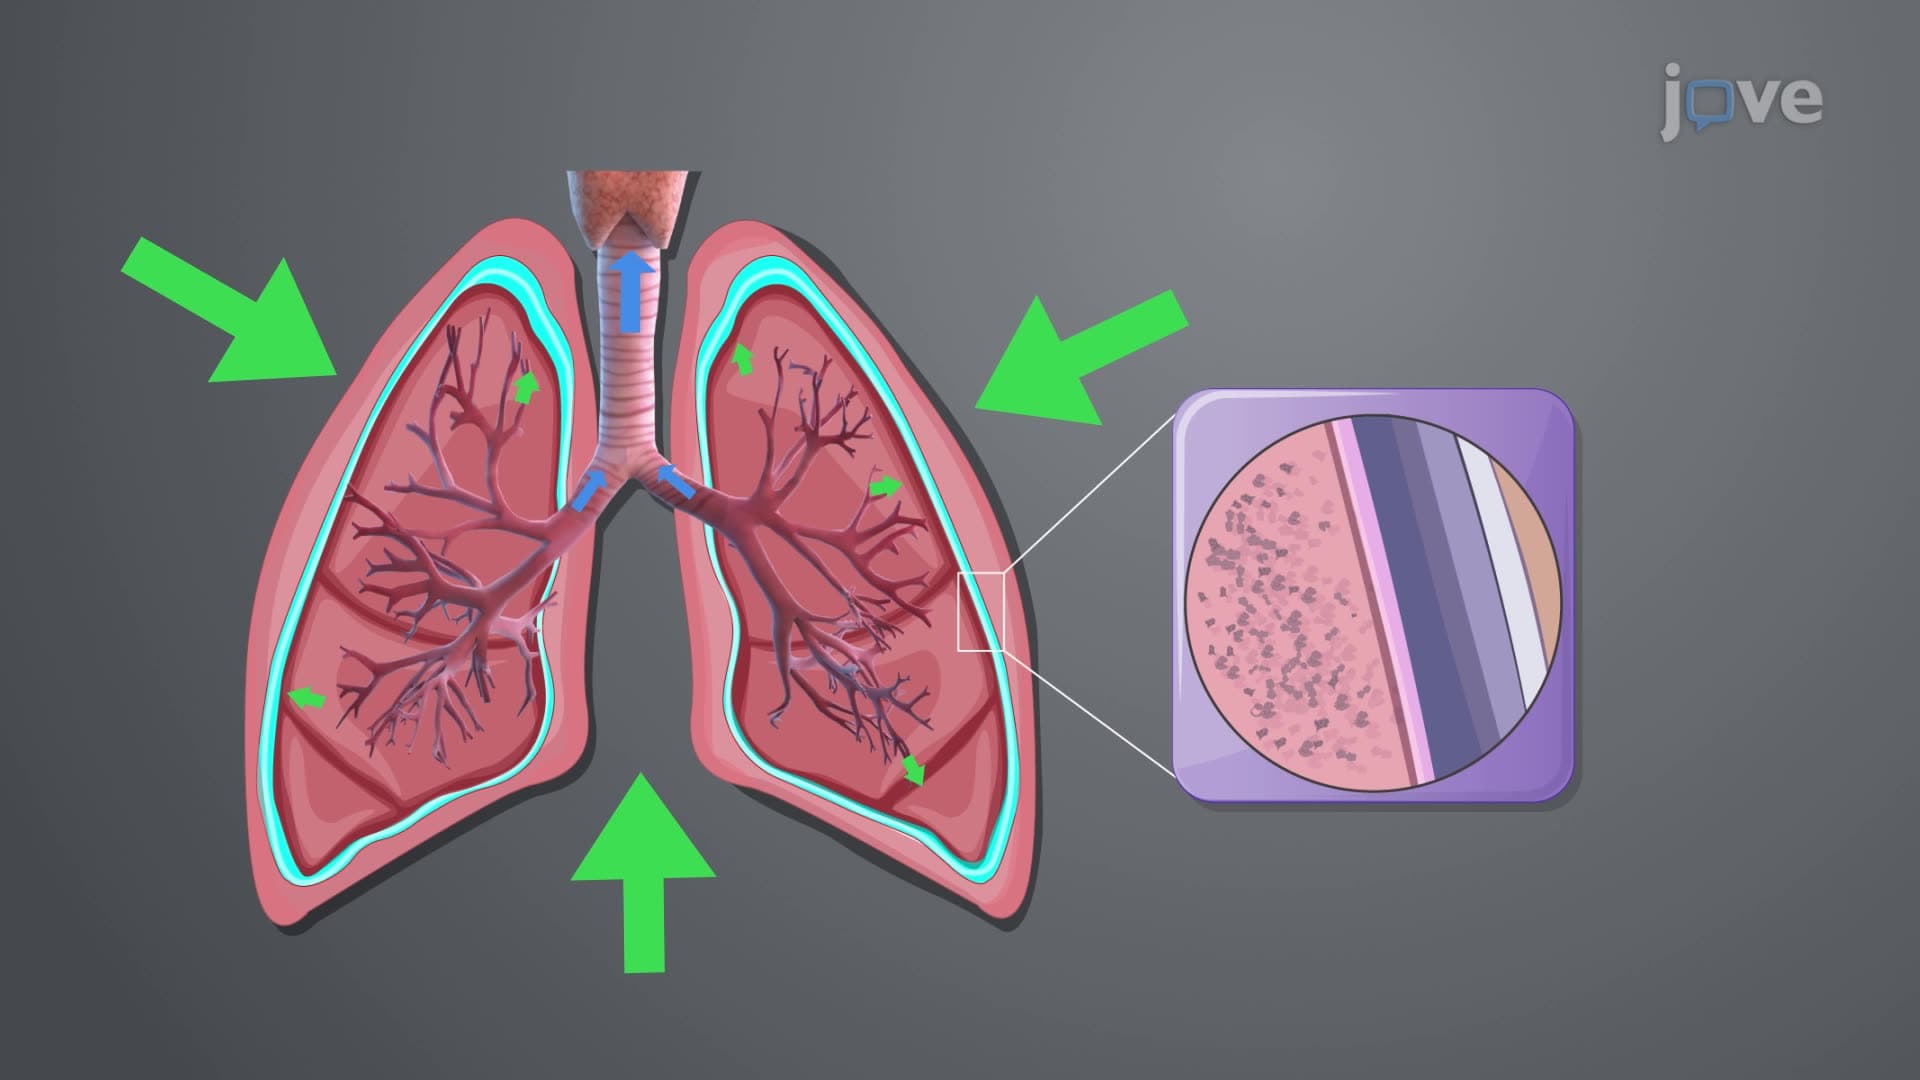
Pressure Relationships in Thoracic Cavity
Breathing Mechanisms
Both intra-alveolar and intrapleural pressures rely on specific lung properties. The ability to breathe—allowing air to enter the lungs...