Related Experiment Video
Updated: Mar 21, 2026

An Ivor Lewis Esophagectomy Designed to Minimize Anastomotic Complications and Optimize Conduit Function
Published on: April 17, 2020
Early Experience of Robot-Assisted Esophagectomy With Circular End-to-End Stapled Anastomosis
Jon O Wee1, Carlos E Bravo-Iñiguez1, Michael T Jaklitsch1
1Division of Thoracic Surgery, Department of Surgery, Brigham and Women's Hospital, Harvard Medical School, Boston, Massachusetts.

Background:
Surgical resection is a critical element in the treatment of esophageal cancer. Esophagectomy is technically challenging and is associated with high morbidity and mortality rates. Efforts to reduce these rates have spurred the adoption of minimally invasive techniques. This study describes a single-institution experience of robot-assisted esophagectomy with circular end-to-end stapled anastomosis.
Methods:
Between December 2013 and April 2015, a series of consecutive patients underwent robot-assisted Ivor Lewis esophagectomy with circular end-to-end anastomosis (RAILE-EEA) at a tertiary care center with curative intent. We retrospectively reviewed their electronic medical records using real-time prospectively collected data. The operative and postoperative outcomes were recorded.
Results:
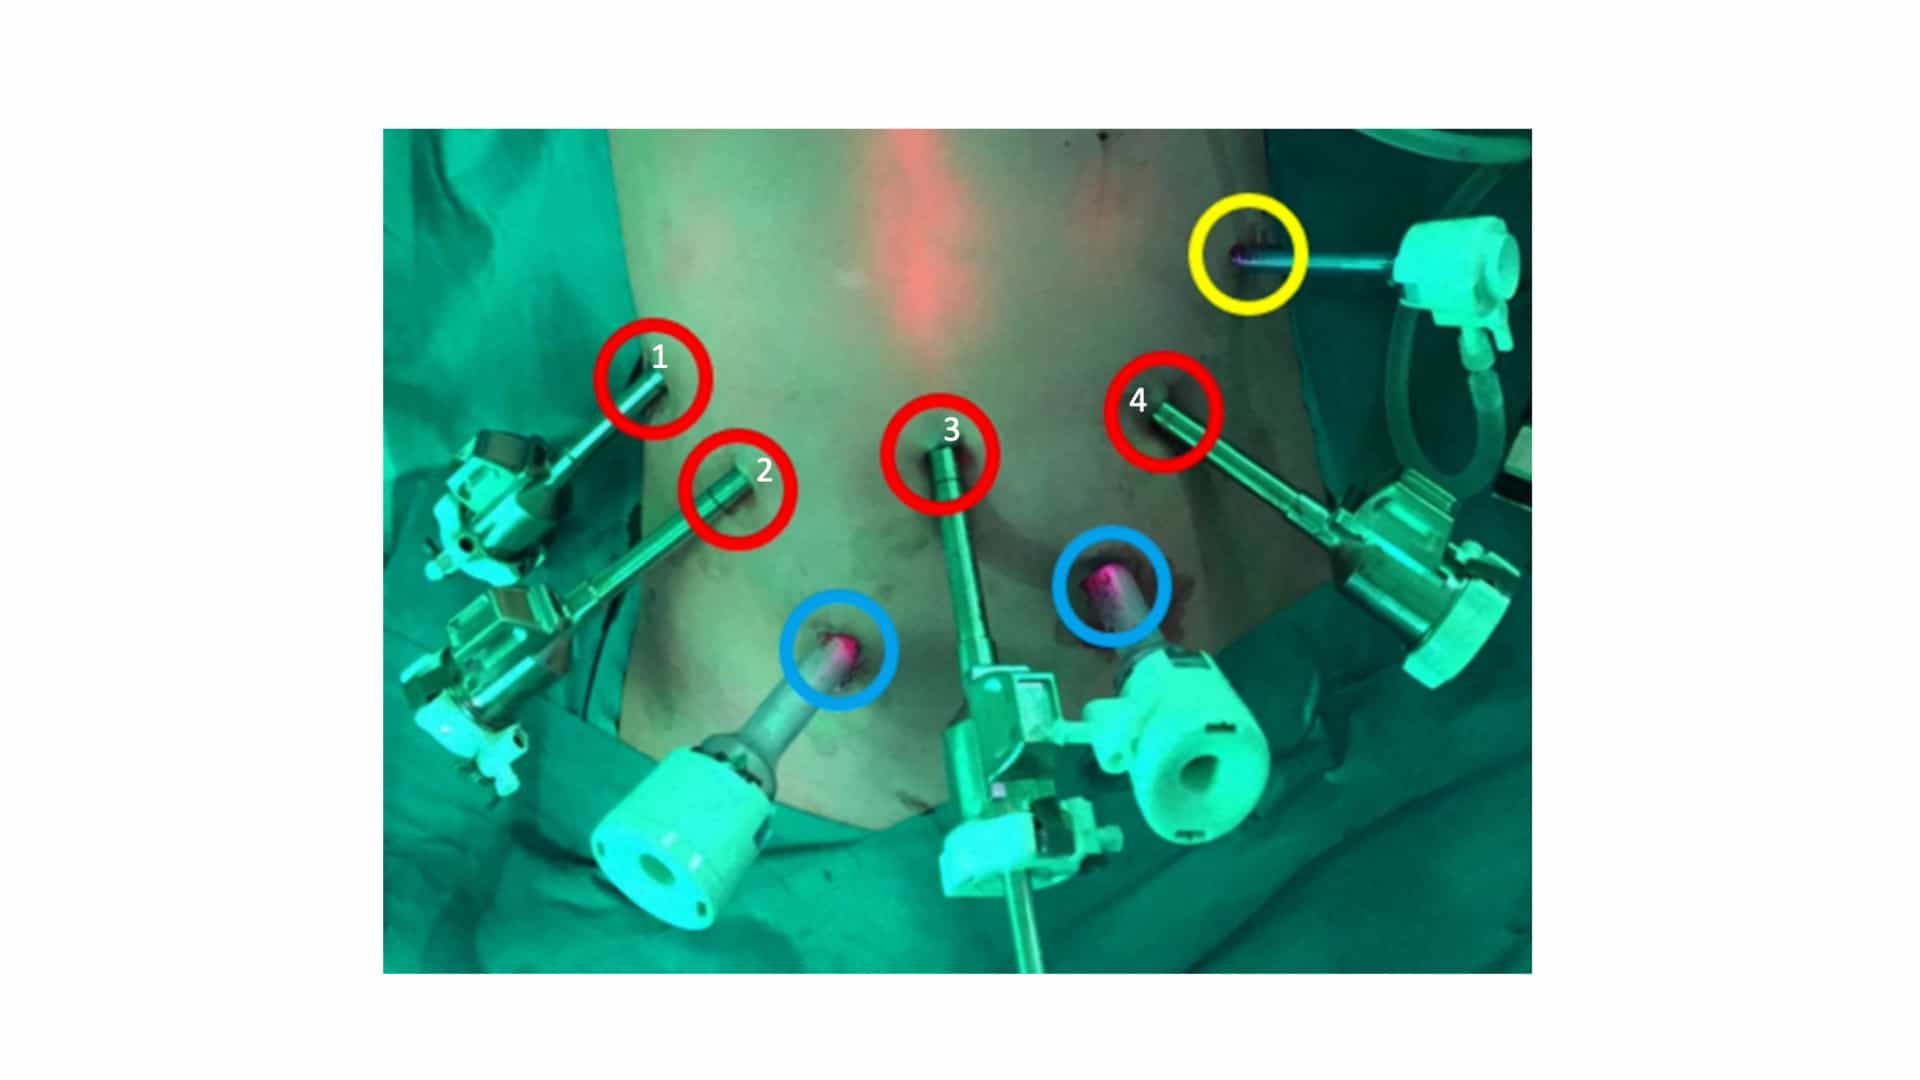
Twenty patients underwent RAILE-EEA during the study period. The abdominal mobilization was performed laparoscopically, and the thoracic portion was robotic. The median total operative time was 455 minutes (range, 318-765 minutes), the 90-day operative mortality was 0%, and morbidity was present in 11 of 20 patients (55%). Atrial fibrillation was the most common event and was observed in 3 patients (15%). There were no anastomotic leaks. The median estimated blood loss was 275 mL, and the conversion rate was 0%. Complete (R0) resection was achieved in all cases. The mean number of lymph nodes was 23.2 (± 2.26). The median follow-up time was 330 days (range, 108-600 days), and the overall 1-year survival was 84%.
Conclusions:
RAILE-EEA in our institution suggests a safe, effective, and reproducible alternative with satisfactory postoperative outcomes for the treatment of esophageal cancer. It provided good local control, adequate lymphadenectomy, low morbidity, and low 90-day operative mortality.