
Frequency and Outcomes of Postrandomization Atrial Tachyarrhythmias in the Resynchronization/Defibrillation in
Stephen B Wilton1, Derek V Exner2, D George Wyse2
1From the Libin Cardiovascular Institute of Alberta, University of Calgary, Calgary, Alberta, Canada (S.B.W., D.V.E., D.G.W.); University of Ottawa Heart Institute, University of Ottawa, Ottawa, Ontario, Canada (E.Y., G.W.); Department of Medicine, Western University, London, United Kingdom (A.S.L.T.); and Population Health Research Institute, McMaster University, Hamilton, Ontario, Canada (J.S.H.). sbwilton@ucalgary.ca.

Insights
Adding cardiac resynchronization therapy with a defibrillator (CRT-D) slightly increased the risk of atrial arrhythmias. However, these arrhythmias did not impact the primary outcome but were linked to increased heart failure hospitalizations.
Area of Science:
- Cardiology
- Electrophysiology
- Heart Failure Management
Background:
- The impact of cardiac resynchronization therapy with a defibrillator (CRT-D) on atrial tachyarrhythmias (AF/AT) is not fully understood.
- It remains unclear if AF/AT influences the benefits derived from CRT-D therapy.
Purpose of the Study:
- To investigate whether CRT-D implantation affects the incidence of post-randomization AF/AT.
- To determine if AF/AT occurrence modulates the effectiveness of CRT-D in patients with heart failure.
Main Methods:
- Analysis of 972 participants from the Resynchronization/Defibrillation in Ambulatory Heart Failure Trial (RAFT) randomized to CRT-D or non-resynchronization defibrillator.
- Prospective assessment of post-randomization AF/AT and utilization of Cox models to evaluate associations with the primary composite outcome (all-cause mortality or heart failure hospitalization).
Main Results:
- Post-randomization AF/AT developed in 50.3% of CRT-D recipients versus 45.3% of defibrillator-only recipients (HR, 1.20; P=0.045).
- AF/AT did not significantly affect the primary composite outcome but was associated with a borderline decreased risk of mortality and an increased risk of heart failure hospitalization.
Conclusions:
- Nearly half of RAFT participants developed AF/AT post-randomization, with a slightly higher risk in the CRT-D group.
- Post-randomization AF/AT was linked to increased heart failure hospitalizations but not the primary composite outcome of mortality or heart failure hospitalization.
Background:
Whether adding cardiac resynchronization therapy (CRT-D) to an implanted cardioverter-defibrillator alters the risk of atrial fibrillation or other atrial tachyarrhythmias (AF/AT), or if postimplantation AF/AT modulate the benefits of CRT-D, remain unknown.
Methods And Results:
We studied 972 Resynchronization/Defibrillation in Ambulatory Heart Failure Trial (RAFT) participants without permanent AF, who were randomized to CRT-D (n=495) versus nonresynchronization defibrillator (implanted cardioverter-defibrillator; n=477) within the predefined stratum eligible for an atrial lead. Occurrence of postrandomization AF/AT was prospectively assessed, and Cox models were used to test the independent association between the postrandomization AF/AT and the RAFT primary composite outcome of all-cause mortality or hospitalization for heart failure. Over 41 (±19) months, postrandomization AF/AT occurred in 216 (45.3%) patients randomized to implanted cardioverter-defibrillator and 249 (50.3%) randomized to CRT-D. After adjusting for competing risk of death, randomization to CRT-D increased risk of postrandomization AF/AT (hazard ratio, 1.20; 95% confidence interval, 1.00-1.42; P=0.045). Postrandomization AF/AT, which remained paroxysmal in 69.5%, did not reduce biventricular pacing percentage. In adjusted models, postrandomization AF/AT was not associated with the primary outcome (hazard ratio, 1.04; 95% confidence interval, 0.84-1.30). However, AF/AT was associated with a borderline decreased risk of mortality (hazard ratio, 0.75; 95% confidence interval, 0.58-1.00) but increased risk of heart failure hospitalization (hazard ratio, 1.43; 95% confidence interval, 1.08-1.90).
Conclusions:
In RAFT, nearly half of the patients developed postrandomization AF/AT, and those randomized to CRT-D had borderline significant higher risk. Postrandomization AF/AT was associated with risk of heart failure hospitalization, but not with the primary composite outcome.
Clinical Trial Registration:
URL: http://www.clinicaltrials.gov. Unique identifier: NCT00251251.


Related Concept Videos
 01:29
Disturbances in Heart Rhythm
Arrhythmias are categorized by their speed, rhythm, and origin. A slow heart...
 01:25
Dysrhythmias VI: Management of Dysrhythmias
 01:28
Dysrhythmias II: Classification of Tachyarrhythmias
 01:28
Mechanism of Cardiac Arrhythmias
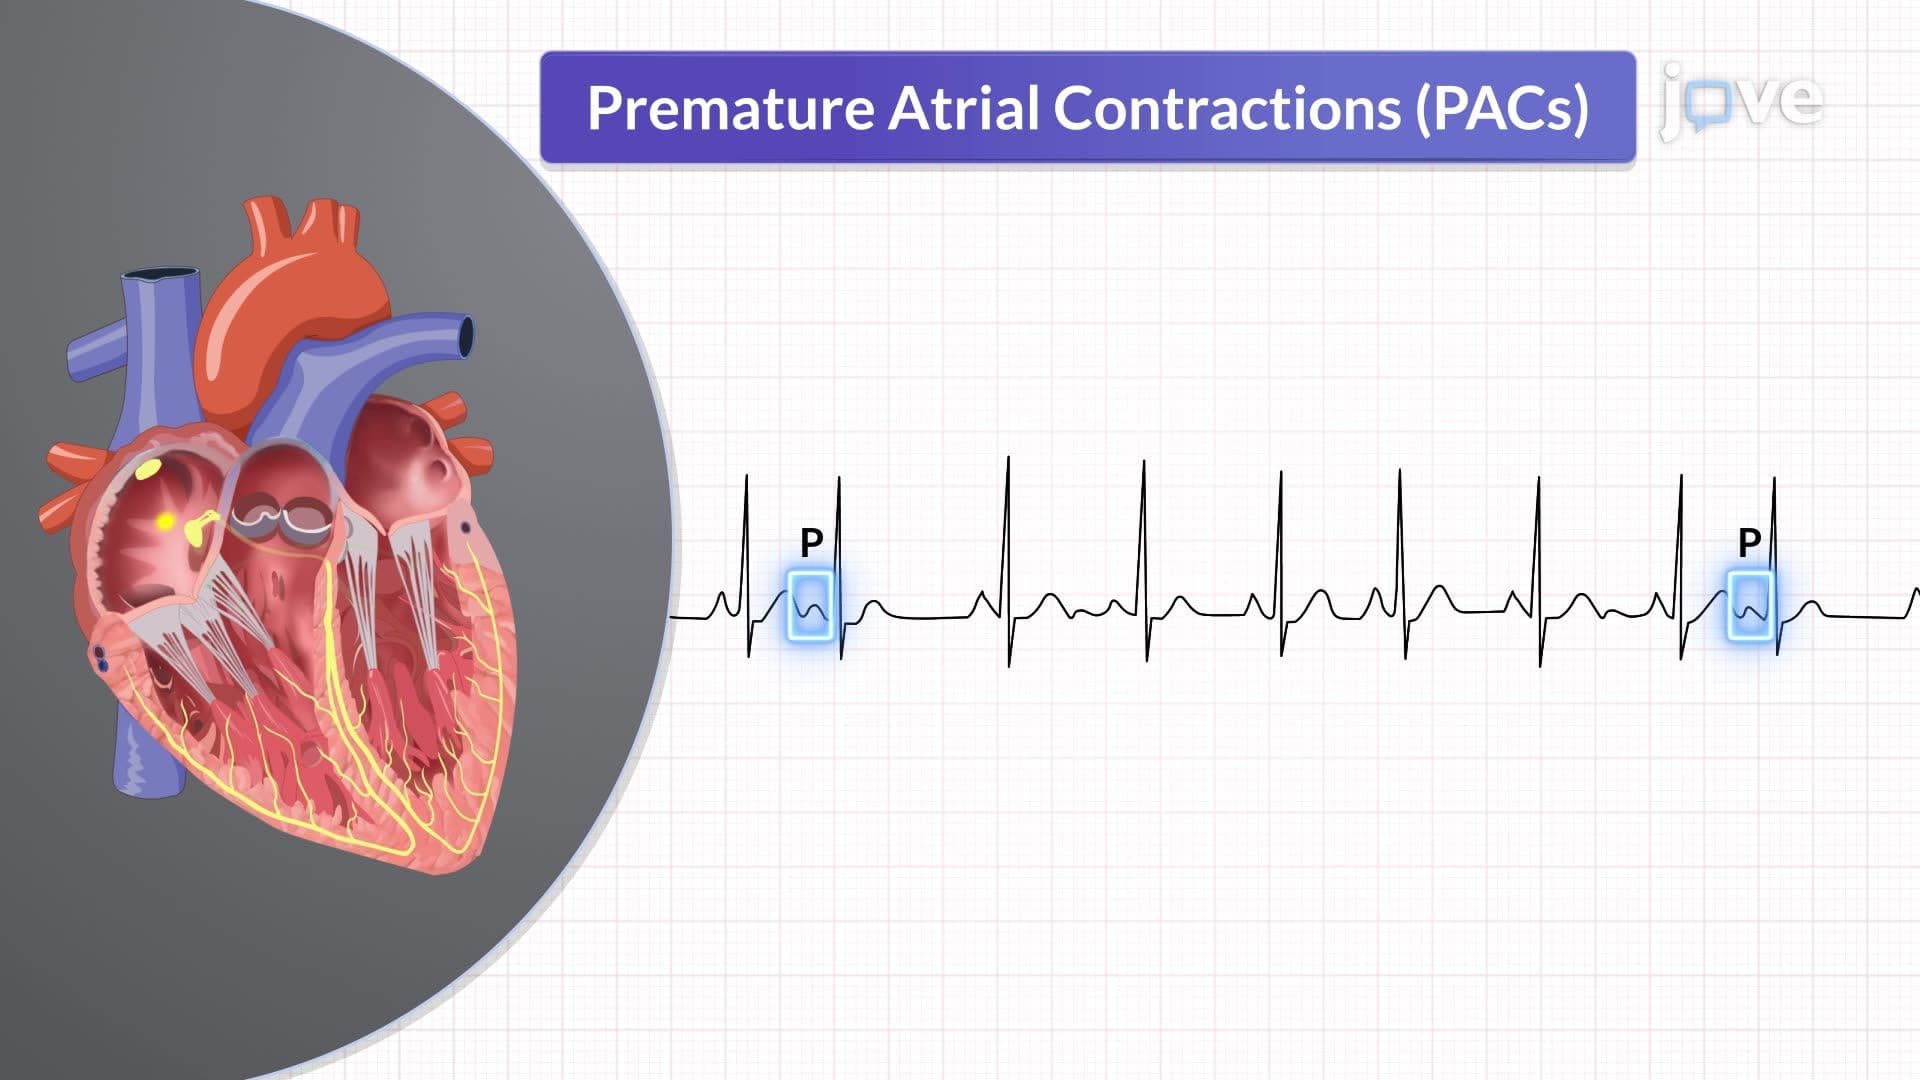 01:29
Dysrhythmias III: Characteristics of Dysrhythmias
 01:30
Pulse rhythm
Conversely, an irregular pulse pattern is termed dysrhythmia, stemming from disruptions in cardiac...