Related Experiment Video
Updated: Mar 21, 2026
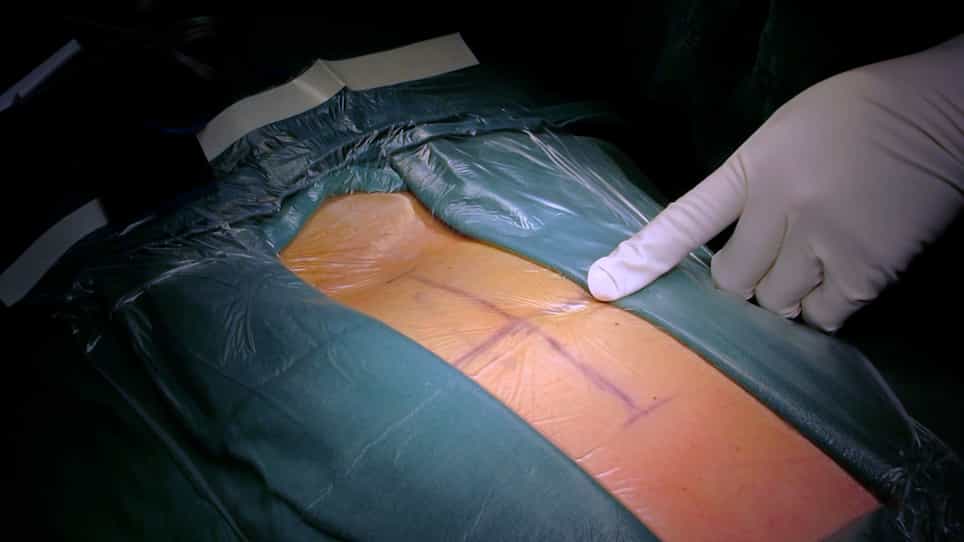

Modified Posterior Vertebral Column Resection for Patients with Thoracolumbar Kyphotic Deformity
Published on: September 16, 2022
Treatment of Early-Onset Spinal Deformity (EOSD) With VEPTR: A Challenge for the Final Correction Spondylodesis-A
Friederike Lattig1, Rita Taurman, Anna K Hell
1*Department Orthopädie, Universitäts-und Rehabilitationsklinik, Ulm†Universitätsmedizin Göttingen, Göttingen, Germany.

Study Design:
Case Series.
Objective:
To describe the post-VEPTR (vertical expandable prosthetic titanium rib) treatment changes in early-onset spinal deformity (EOSD), which may influence the final correction spondylodesis.
Summary Of Background Data:
The VEPTR device, originally developed for the treatment of congenital rib cage malformation, is nowadays more widely used in the treatment of EOSD. At present, only a few reports describe the possible complications that may occur with repeated lengthening procedures of the VEPTR, thereby making the final spondylodesis more complicated and less satisfactory.
Methods:
X-rays of 5 children treated for EOSD with 2 unilateral VEPTR (each rib to rib and rib to lumbar lamina) were analyzed for curve patterns and Cobb angles before, during, and at the end of VEPTR treatment, and after the final spondylodesis. Intraoperative observations during the spondylodesis, which influenced the possibilities of the curve correction, were documented.
Results:
All patients showed a marked decompensation of the frontal balance and a high degree of rigidity of the main curve and the compensatory curves after treatment with the VEPTR device. Because of this spontaneous autofusion of spinal segments, migration of the rib cradles and/or the laminar hook, and a change in the curve patterns, the final fusion had to be longer in all patients than the primary deformity would have intended.
Conclusions:
If an EOSD is treated with VEPTR, the curve progression and, in particular, the development of a high thoracic hyperkyphosis or rotation of the main curve should be critically observed. Autofusion of ribs and vertebral bodies may make the final correction spondylodesis even more challenging and risky for the patient and the end result less satisfactory.


