Related Experiment Video
Updated: Mar 20, 2026
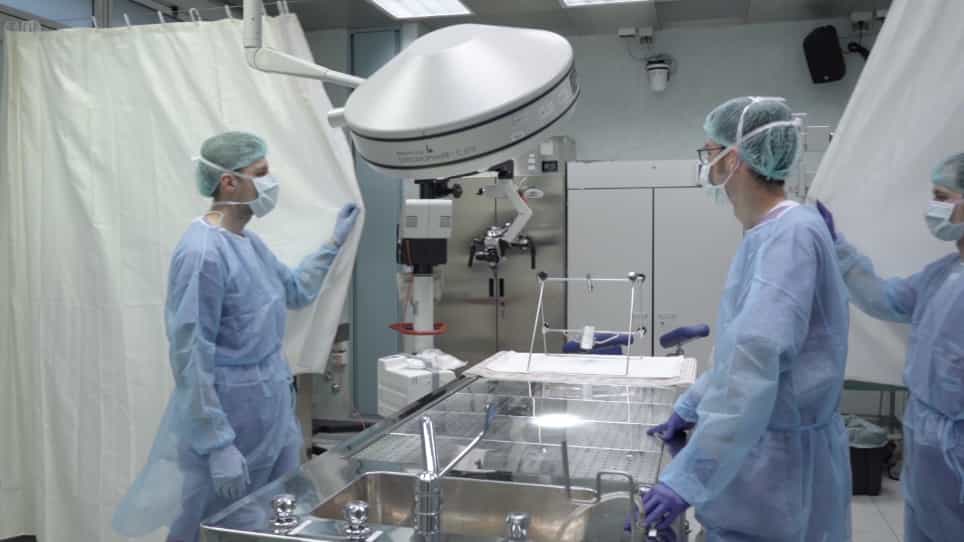

Learning Modern Laryngeal Surgery in a Dissection Laboratory
Published on: March 18, 2020
Management of severe congenital laryngeal webs - a 12 year review
L A de Trey1, K Lambercy2, P Monnier2
1Department of Otorhinolaryngology, Head and Neck Surgery, University Hospital (CHUV), Lausanne, Switzerland; Department of Otorhinolaryngology, Children's University Hospital Zurich, Switzerland.

Objective:
The aim of this study was to investigate respiratory and voice outcomes after open surgery for severe congenital laryngeal web.
Methods:
Included were all patients treated for severe congenital glottic web (Cohen type 3 and 4) between 2002 and 2014. Demographic data, symptoms, endoscopic findings, type of operation, outcome and complications were analyzed. Open surgery was performed with division of the web and enlargement of the subglottis by a laryngotracheal reconstruction or an extended partial cricotracheal resection.
Results:
Fourteen patients were included. Information on the pre-operative voice was available in 11 patients. Aphonia was present in 6 patients (55%), dysphonia was severe in 1 (9%), moderate in 2 (18%) and mild in 2 (18%). Median age at operation was 19.3 months. As a first line treatment, laryngotracheal reconstruction was performed in 12 patients, and an extended partial cricotracheal resection in 2. Median follow-up was 9.5 months. All patients were successfully decannulated in a median time of 4 months after first surgery. Voice was improved in 10/11 (91%). Post-operatively, 3 patients (27%) had good voice. Dysphonia was severe in 2 (18%), moderate in 3 (27%) and mild in 3 patients (27%).
Conclusion:
Open surgery for Cohen type 3 and 4 glottic web allowed establishing a patent airway with successful decannulation in all cases. Quality of voice was improved in 91%, however, voice results were variable. In our opinion a delicate operative technique described in the paper is important for optimal voice results.


Related Concept Videos
 01:26
Esophageal Strictures-II: Clinical Features and Management
Healthcare providers should gather a comprehensive medical history and conduct a physical examination for diagnosis. If esophageal stricture is...
 01:30
Cardiopulmonary Resuscitation V: Advanced Airway Management Techniques
 01:22
Trachea
Anatomical Features:
Location: About half of the trachea is situated in the neck, anterior to the esophagus, and extends from the larynx (at the level of...
 01:28
Esophageal Varices-II: Clinical Features and Management
In the initial assessment, a thorough review of the patient's medical history is vital to identify risk factors such as liver disease, alcohol...
 01:26
Mitral Stenosis III: Medical Management
 01:30
Esophageal Strictures-I: Introduction
Etiology
The primary cause of esophageal strictures is long-standing gastroesophageal reflux disease (GERD), accounting for about 70 to 80% of adult cases. Chronic acid reflux can lead to injury and scarring of the esophageal lining, culminating in...