The on- and off-target effects of morphine in acute coronary syndrome: A narrative review
Related Experiment Video
Updated: Mar 20, 2026

Assessment of Morphine-induced Hyperalgesia and Analgesic Tolerance in Mice Using Thermal and Mechanical Nociceptive Modalities
Published on: July 29, 2014
Cian P McCarthy1, Kieran V Mullins1, Sunjeet S Sidhu2
1Department of Medicine, University College Cork, Ireland.

With potent analgesic properties, perceived hemodynamic benefits and limited alternatives, morphine is the analgesic mainstay for patients with nitrate resistant chest pain due to acute Myocardial Infarction (MI). However, observational data suggest that morphine administration during MI may have negative consequences. While vomiting, hypotension and respiratory depression are established side effects, recent reports have demonstrated attenuated and delayed oral anti-platelet agent absorption, as well as suboptimal reperfusion after MI, all of which may translate into adverse cardiovascular outcomes. These data have resulted in reduced support for morphine in recent European and U.S. clinical practice guidelines for MI; despite the absence of any prospective randomized outcomes trials addressing this question. As such, randomized trials are now necessary to confirm whether or not morphine, which is administered in up to 30% of MI cases, causes adverse clinical outcomes in these patients. However, given that placebo-controlled randomized trial designs evaluating morphine in MI are limited by an ethical requirement for appropriate analgesia, alternative investigational approaches may be necessary. In this article we review the updated evidence for morphine in MI and outline novel strategies that may facilitate future investigation of this clinical dilemma.
With potent analgesic properties, perceived hemodynamic benefits and limited alternatives, morphine is the analgesic mainstay for patients with nitrate resistant chest pain due to acute Myocardial Infarction (MI). However, observational data suggest that morphine administration during MI may have negative consequences. While vomiting, hypotension and respiratory depression are established side effects, recent reports have demonstrated attenuated and delayed oral anti-platelet agent absorption, as well as suboptimal reperfusion after MI, all of which may translate into adverse cardiovascular outcomes. These data have resulted in reduced support for morphine in recent European and U.S. clinical practice guidelines for MI; despite the absence of any prospective randomized outcomes trials addressing this question. As such, randomized trials are now necessary to confirm whether or not morphine, which is administered in up to 30% of MI cases, causes adverse clinical outcomes in these patients. However, given that placebo-controlled randomized trial designs evaluating morphine in MI are limited by an ethical requirement for appropriate analgesia, alternative investigational approaches may be necessary. In this article we review the updated evidence for morphine in MI and outline novel strategies that may facilitate future investigation of this clinical dilemma.


Related Concept Videos
 01:25
Analgesia and Pain Management
 01:20
Opioid Analgesics: Morphine and Other Natural Cogeners
 01:15
Opioid Analgesics: Synthetic and Semisynthetic Opioids
 01:22
Opioid Receptors: Overview
 01:28
Acute Coronary Syndrome IV: Interprofessional Care
 01:25
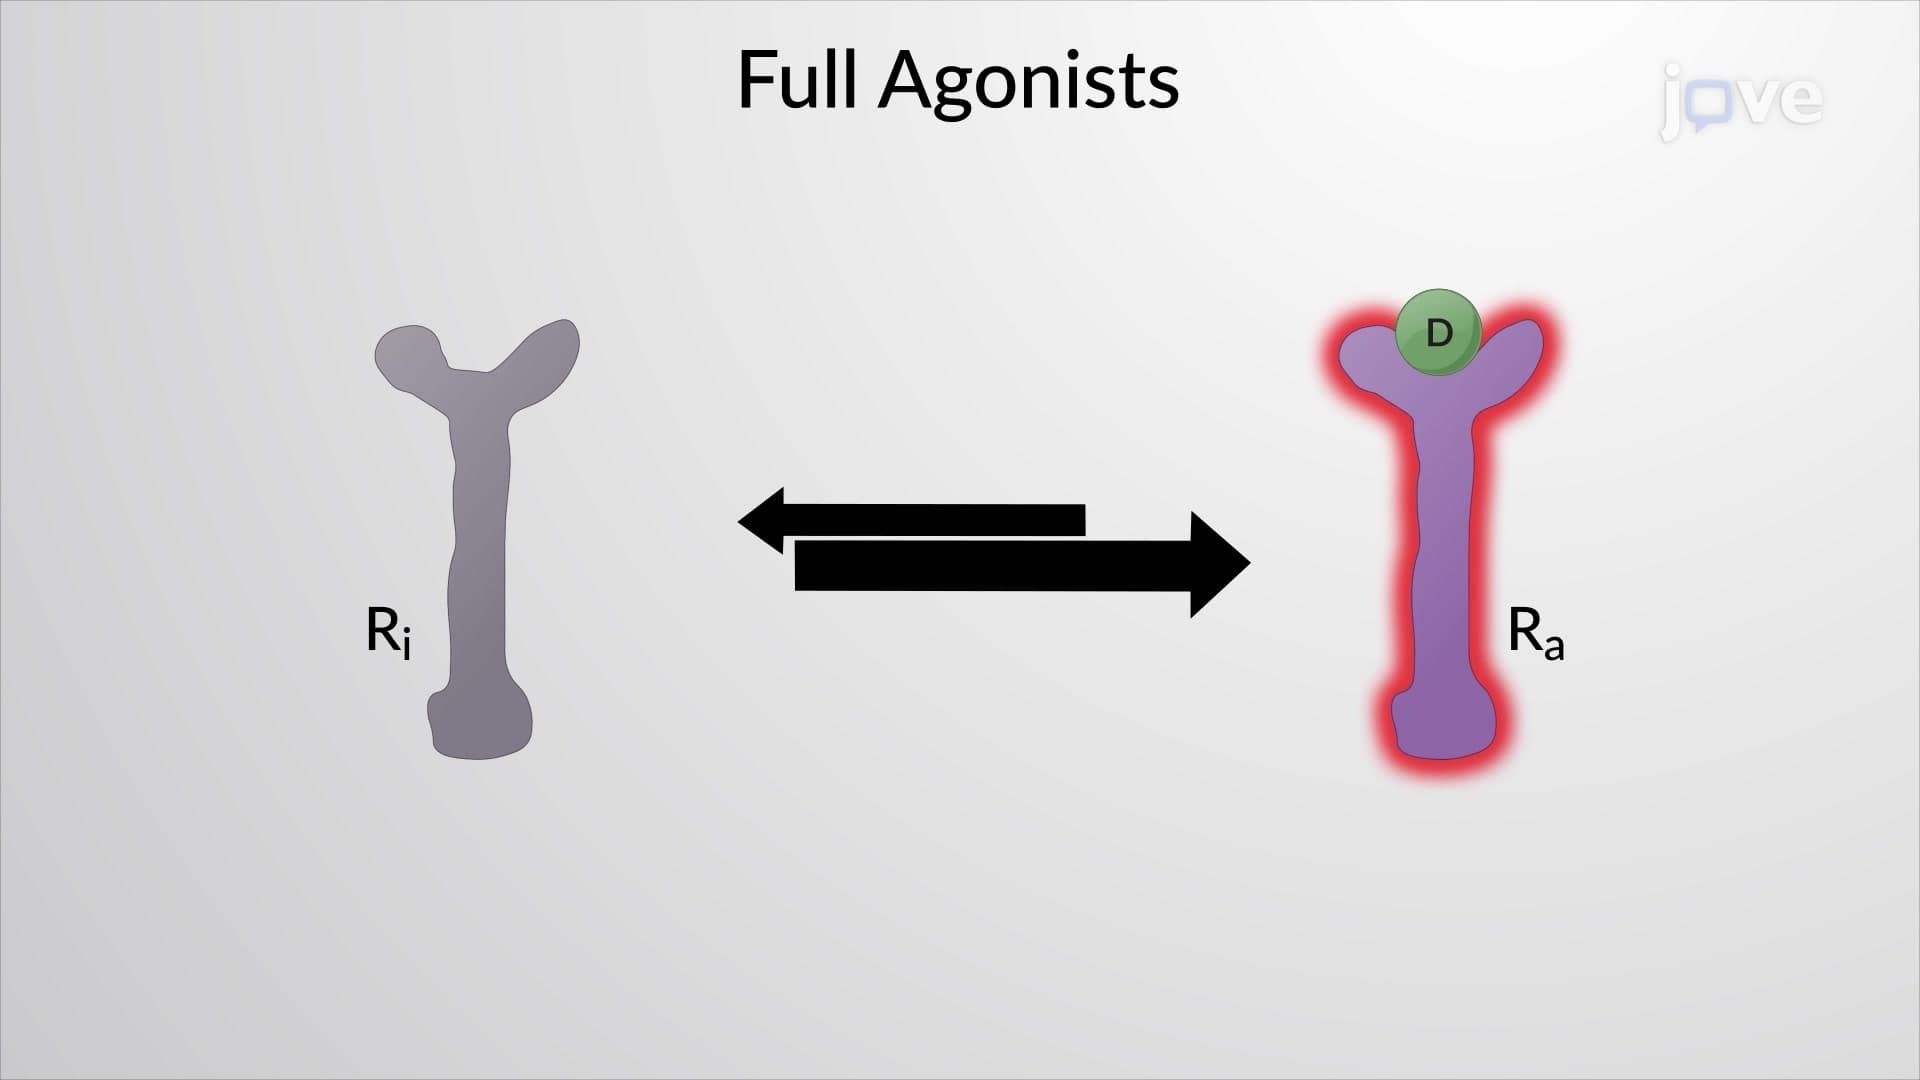
Drug-Receptor Interaction: Agonist
Agonists can bind to receptors in different ways. Some agonists bind directly to the receptor's active site, mimicking the endogenous...