Related Experiment Video
Updated: Jun 18, 2026


Homochronic Transplantation of Interneuron Precursors into Early Postnatal Mouse Brains
Published on: June 8, 2018
Long-term outcome in juvenile-onset mixed connective tissue disease: a nationwide Norwegian study
Siri Opsahl Hetlevik1, Berit Flatø1,2, Marite Rygg3,4
1Department of Rheumatology, Oslo University Hospital, Rikshospitalet, Oslo, Norway.

Objectives:
To describe the characteristics, outcome and predictive factors of juvenile mixed connective tissue disease (JMCTD) in a nationwide cohort of patients.
Methods:
We examined 55 patients with JMCTD after a mean disease duration of 16.2 years (SD 10.0). Patients were registered according to Kasukawa's criteria. Remission criteria were defined according to those for juvenile idiopathic arthritis, plus absence of cytopenia, myositis, progressive sclerodactyly, lung and oesophageal manifestations. Organ damage was assessed with the Systemic Lupus International Collaborating Clinics (SLICC)/American College of Rheumatology (ACR) Damage Index and the Juvenile Arthritis Damage Index (JADI). Medical records were reviewed for early predictors for outcome, which were assessed by multivariate logistic regression analyses.
Results:
Three patients developed systemic lupus erythematosus (SLE). Fifty-two patients had continuous JMCTD; the most common manifestations were: Raynaud (100%), arthritis (94%), puffy hands (77%) and pulmonary manifestations (58%). SLE-like, systemic sclerosis (SSc)-like and polymyositis (PM)-like findings were found in 98%, 77% and 48%, respectively. Over time, SLE-like and PM-like manifestations decreased, and SSc-like findings increased. At follow-up, 35 patients (67%) had active disease and 17 (33%) were in remission. In 34 patients (65%), SLICC or JADI≥1 assessments indicated organ damage. Active disease was associated with higher anti-ribonucleoprotein antibody titres at follow-up and positive rheumatoid factor (RF) at diagnosis and follow-up.
Conclusions:
Most patients with JMCTD had active disease and organ damage after a mean follow-up of 16.2 years. Active disease was associated with higher anti-ribonucleoprotein antibody levels and positive RF. The presence of RF at diagnosis predicted persistent disease activity.
More Related Videos


Related Concept Videos
 01:22
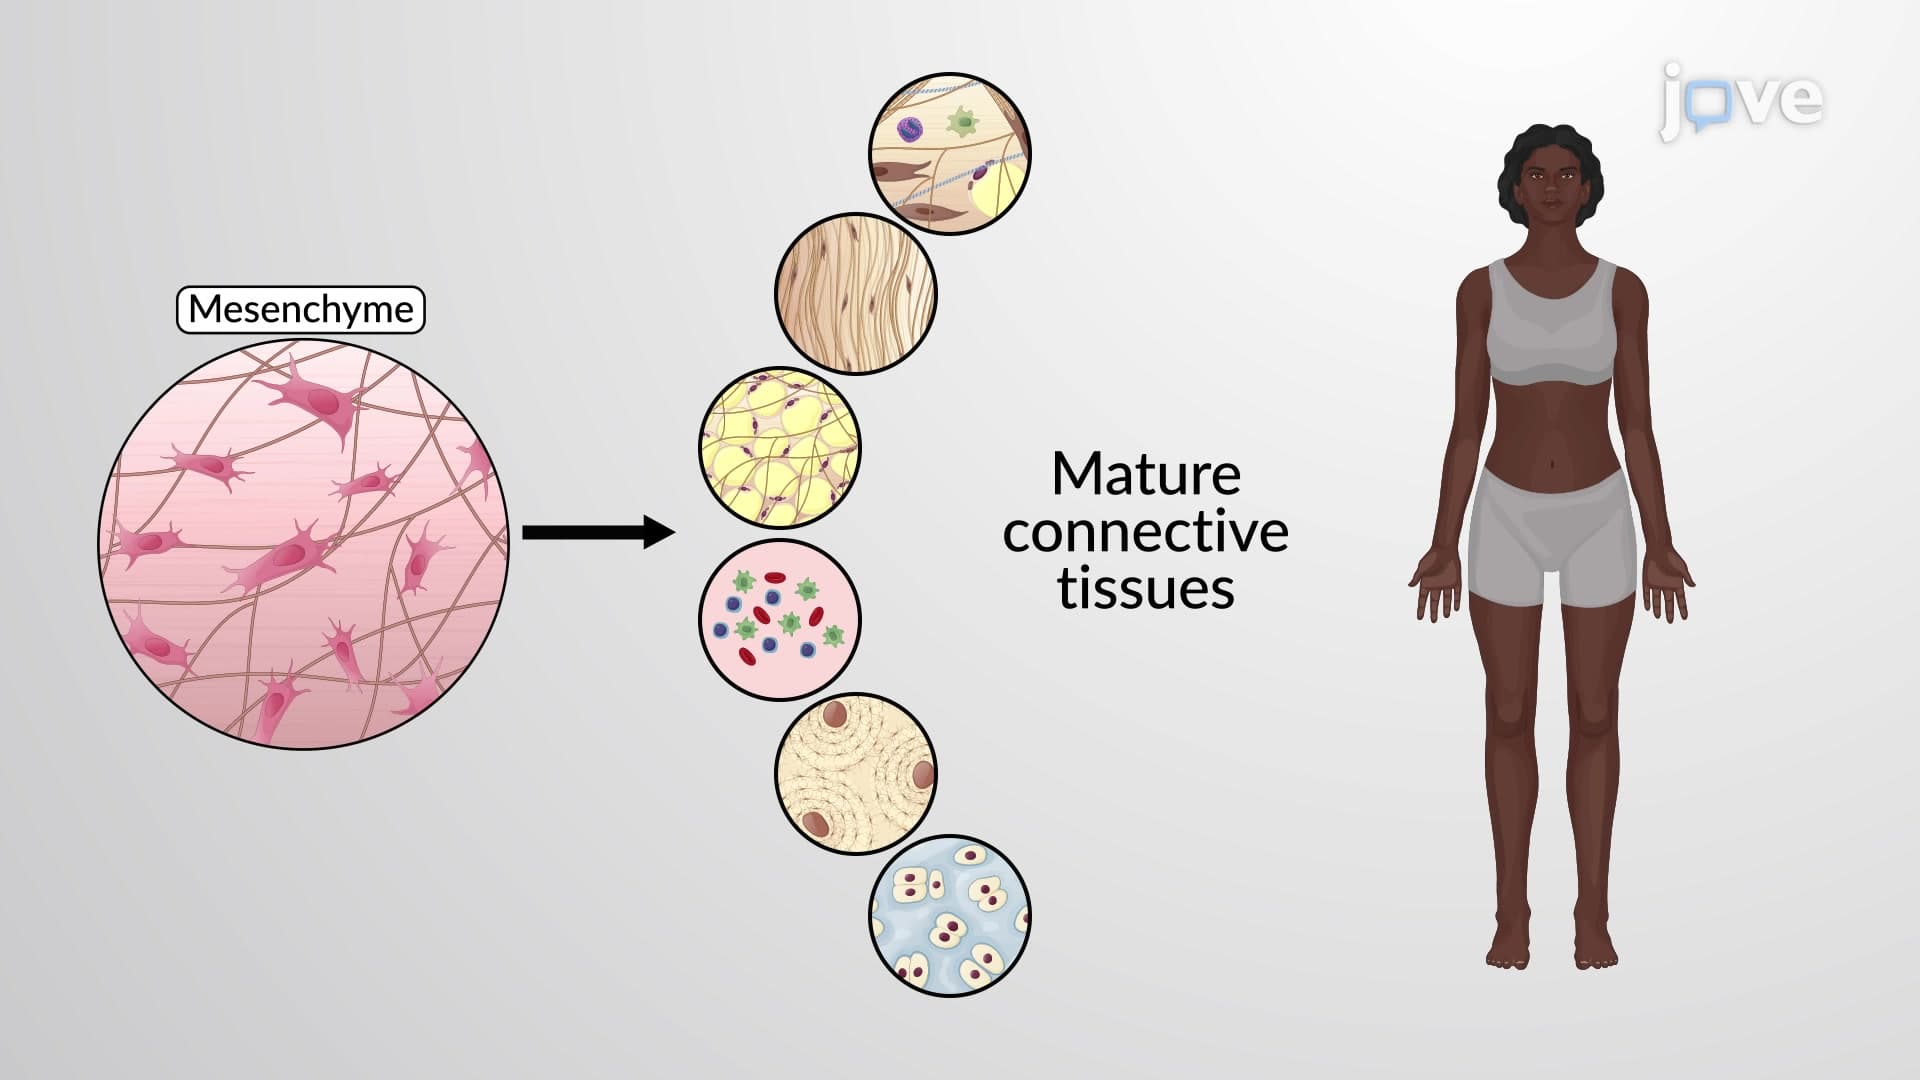
Connective Tissue Cell Types
Fat cells (adipocytes), smooth muscle cells (myoblasts), and bone cells (osteoblasts) are some connective tissue cell types. Some immune system cells...
 01:30
Classification of Connective Tissues
Connective Tissue Proper
Connective tissue proper is the most abundant class of connective tissues. As its name implies, it predominantly connects different tissues in the body. Depending on the cell types, ground substance, viscosity, and fiber types in the ECM, connective tissue proper is further categorized into loose and dense.
 01:26
Loose Connective Tissue
Adipose Tissue
Adipose tissue consists primarily of fat storage cells called adipocytes and little extracellular matrix. A large number of capillaries present within adipose tissue allow rapid mobilization of lipid molecules. White adipose tissue is...
 01:29
Bone Disorders
Bone deposition is also affected by the levels of sex hormones like estrogen and testosterone that promote osteoblast activity and bone matrix synthesis. When the level of these hormones decreases due to aging, it causes a reduction in bone deposition. As a result, bone resorption by osteoclasts...
 01:22
Rheumatic Heart Disease II: Clinical Manifestations and Diagnostic Studies
 01:26
Nephrotic Syndrome II : Assessment and Medical Management