Related Experiment Video
Updated: Sep 28, 2026
Fundus Photography as a Convenient Tool to Study Microvascular Responses to Cardiovascular Disease Risk Factors in Epidemiological Studies
Published on: October 22, 2014
Retinal microvascular diameter, a hypertension-related trait, in ECG-gated vs. non-gated images analyzed by IVAN and
Fang-Fei Wei1, Zhen-Yu Zhang1, Thibault Petit1
1Studies Coordinating Centre, Research Unit Hypertension and Cardiovascular Epidemiology, KU Leuven Department of Cardiovascular Sciences, University of Leuven, Leuven, Belgium.

Abstract:
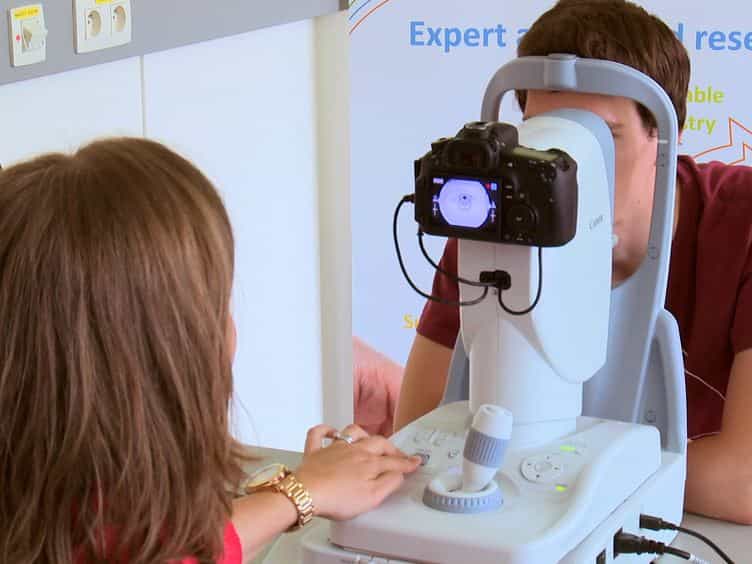
The diameters of the retinal microvasculature reflect intermediate target organ damage and predict adverse health outcomes. In view of the pulsatility of the cerebral blood flow and refinement of software used for off-line analysis, we assessed the repeatability of retinal microvascular diameters in ECG-gated vs. non-gated images using nonmydriatic retinal photographs (Canon Cr-DGi visualization system) postprocessed by IVAN (Vasculomatic ala Nicola, version 1.1) or SIVA (Singapore I Vessel Assessment, version 3.6). Using these algorithms, we determined the central retinal arteriolar (CRAE) and venular (CRVE) equivalents and their ratio (arteriole-to-venule ratio (AVR)). The estimates of CRAE (mean, 158.5 μm), CRVE (222.5 μm) and AVR (0.71) in 10 volunteers were unaffected (P⩾0.059) by ECG gating. We assessed intragrader repeatability by the Bland and Altman approach in 30 participants with non-gated images and 30 with ECG-gated photographs. Repeatability, which was expressed as the percentage of near maximal variability (4-s.d. range), did not improve with ECG gating. Using SIVA, CRAE and CRVE were systematically larger (P⩽0.031), and the AVR estimates were similar (P⩾0.15) compared with IVAN. The differences (IVAN-SIVA) averaged -5.4 μm for CRAE, -3.9 μm for CRVE and -0.012 for AVR in the non-gated images and -3.3 μm, -6.9 μm and 0.006, respectively, in the ECG-gated photographs. In conclusion, ECG gating does not affect estimates of the retinal microvascular diameters or improve intragrader repeatability. SIVA yields slightly but significantly larger estimates of the retinal arteriolar and venular diameters. Combining historical readings analyzed by IVAN with more recent readings by SIVA is possible only for AVR and is not recommended for either CRAE or CRVE.