Endovascular treatment of acute ischemic stroke
Related Experiment Video
Updated: Mar 17, 2026
Optimized Management of Endovascular Treatment for Acute Ischemic Stroke
Published on: January 18, 2018
Thabele Leslie-Mazwi1, James Rabinov1, Joshua A Hirsch1
1Neuroendovascular Service, Massachusetts General Hospital, Boston, MA, USA.

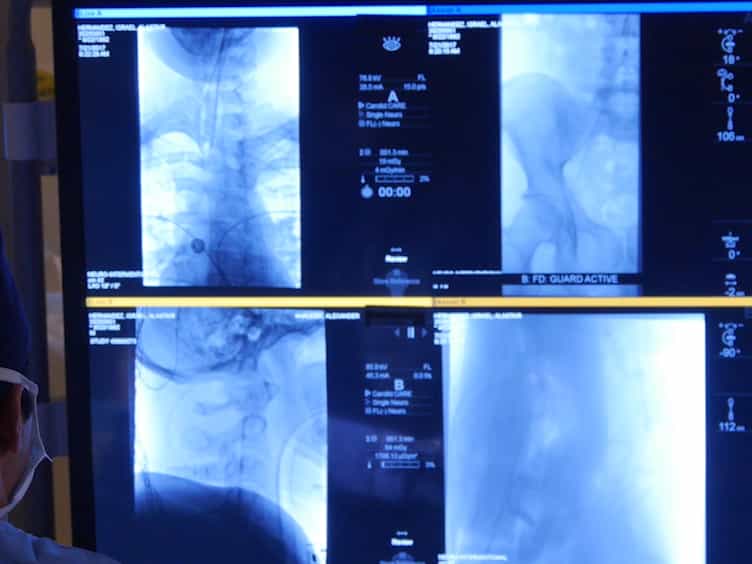
Endovascular thrombectomy is an effective treatment for major acute ischemic stroke syndromes caused by major anterior circulation artery occlusions (commonly referred to as large vessel occlusion) and is superior to intravenous thrombolysis and medical management. Treatment should occur as quickly as is reasonably possible. All patients with moderate to severe symptoms (National Institutes of Health stroke scale >8) and a treatable occlusion should be considered. The use of neuroimaging is critical to exclude hemorrhage and large ischemic cores. Very shortly after stroke onset (<3 hours) computed tomography (CT) and CT angiography provide sufficient information to proceed; diffusion magnetic resonance imaging (MRI) is less reliable during this early stage. After 3 hours from onset diffusion MRI is the most reliable method to define ischemic core size and should be used in centers that can offer it rapidly. Recanalization is highly effective with a stentriever or using a direct aspiration technique, with the patient awake or under conscious sedation rather than general anesthesia, if it may be performed safely. After thrombectomy the patient should be admitted to an intensive care setting and inpatient rehabilitation undertaken as soon as feasible. Patient outcomes should be assessed at 3 months, preferably using the modified Rankin score.
Endovascular thrombectomy is an effective treatment for major acute ischemic stroke syndromes caused by major anterior circulation artery occlusions (commonly referred to as large vessel occlusion) and is superior to intravenous thrombolysis and medical management. Treatment should occur as quickly as is reasonably possible. All patients with moderate to severe symptoms (National Institutes of Health stroke scale >8) and a treatable occlusion should be considered. The use of neuroimaging is critical to exclude hemorrhage and large ischemic cores. Very shortly after stroke onset (<3 hours) computed tomography (CT) and CT angiography provide sufficient information to proceed; diffusion magnetic resonance imaging (MRI) is less reliable during this early stage. After 3 hours from onset diffusion MRI is the most reliable method to define ischemic core size and should be used in centers that can offer it rapidly. Recanalization is highly effective with a stentriever or using a direct aspiration technique, with the patient awake or under conscious sedation rather than general anesthesia, if it may be performed safely. After thrombectomy the patient should be admitted to an intensive care setting and inpatient rehabilitation undertaken as soon as feasible. Patient outcomes should be assessed at 3 months, preferably using the modified Rankin score.

Related Concept Videos
 01:29
Venous Thrombosis III: Interprofessional Care
 01:27
Peripheral Artery Disease III: Interprofessional Care
 01:28
Acute Coronary Syndrome IV: Interprofessional Care
 01:29
Pulmonary Embolism II: Diagnostic Studies and Interprofessional Care