Related Experiment Video
Updated: Mar 16, 2026
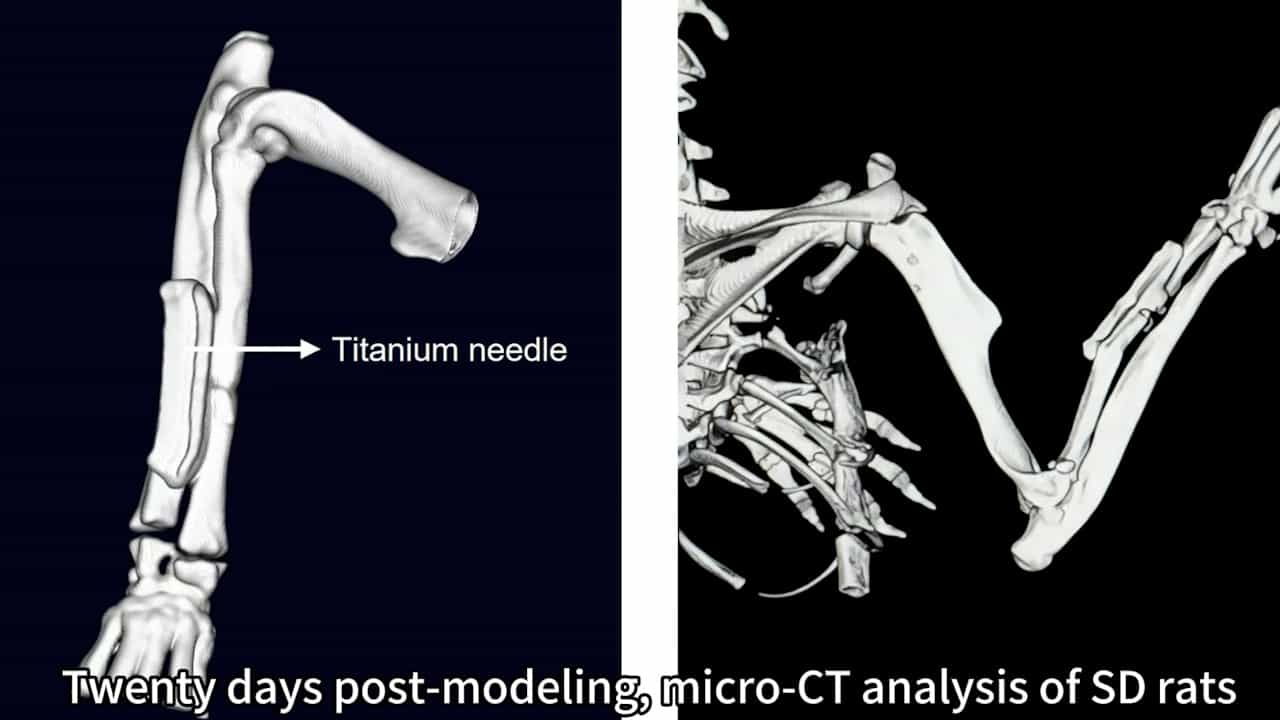
Development of a Novel Internal Fixation Model for Rat Radial Fractures: Fracture Healing Assessment and Dorsal Root Ganglion Isolation
Published on: March 13, 2026
Risk Factors for Deep Infection Following Plate Fixation of Proximal Tibial Fractures
Markus Parkkinen1, Rami Madanat2, Jan Lindahl3
1Department of Orthopaedics and Traumatology, University of Helsinki, Helsinki, Finland Helsinki University Hospital, Helsinki, Finland markus.parkkinen@hus.fi.

Background:
The risk factors are unclear for deep surgical site infection after plate fixation of proximal tibial fractures. The objective of this study was to identify the patient and surgical procedure-related risk factors for infection using established criteria for deep surgical site infection.
Methods:
A total of 655 proximal tibial fractures were treated with open reduction and plate fixation at our center between 2004 and 2013. We identified 34 patients with deep surgical site infection. A control group of 136 patients was randomly selected from the non-infected cohort. Potential risk factors for deep surgical site infection were identified by reviewing surgical, medical, and radiographic records. Independent risk factors for infection were identified from multivariable logistic regression analysis using a stepwise procedure.
Results:
The prevalence of deep surgical site infection was 5.2%, the mean age of affected patients was 55 years (range, 16 to 84 years), and 35% of patients were female. Twenty-eight of 34 deep infections were diagnosed within 2 months (acute onset), and only 6 infections were diagnosed >6 months after the index surgical procedure. Nine of the 28 acute-onset infections were treated with antibiotic therapy and debridement. Seventeen patients (50%) required muscle flap coverage, and 5 patients (15%) eventually required above-the-knee amputation. In the multivariable logistic regression analysis with odds ratios (ORs) and 95% confidence intervals (95% CIs), independent predictors of infection were patient age of ≥50 years (OR, 3.6 [95% CI, 1.3 to 10.1]); obesity, defined as a body mass index of ≥30 kg/m(2) (OR, 6.5 [95% CI, 2.2 to 18.9]); alcohol abuse (OR, 6.7 [95% CI, 2.4 to 19.2]); OTA/AO-type-C fracture (OR, 2.8 [95% CI, 1.1 to 7.5]); use of a temporary spanning external fixator (OR, 3.9 [95% CI, 1.4 to 11.1]); and a 4-compartment fasciotomy (OR, 4.5 [95% CI, 1.3 to 15.7]).
Conclusions:
There is high morbidity associated with deep surgical site infection in plated proximal tibial fractures. Patients who are ≥50 years of age, obese patients, those with a history of alcohol abuse, or those with an OTA/AO-type-C fracture are at high risk for infection. Performing a fasciotomy also increases the risk of deep infection and should be implemented with meticulous technique when deemed necessary.
Level Of Evidence:
Prognostic Level III. See Instructions for Authors for a complete description of levels of evidence.
More Related Videos
 06:53
A Rat Tibial Growth Plate Injury Model to Characterize Repair Mechanisms and Evaluate Growth Plate Regeneration Strategies
Published on: July 4, 2017
 04:41
Treatment with Locking Intramedullary Nailing for Intertrochanteric Fracture of the Femur Utilizing a New Awl with a Distal Positioner
Published on: June 6, 2025
Related Concept Videos
 01:26
Factors Affecting the Risk of Infection
The integrity and count of the white blood cells help the body resist pathogens and fight infection. When impaired, it reduces the body's resistance to pathogens. The acidic pH levels of the gastrointestinal, genitourinary tracts, and skin...
 01:27
Fractures: Bone Repair
Minor fractures with no bone displacement are treated by immobilizing the fractured bone using a cast or splint. However, in the case of fractures with displaced bones, the broken bones are repositioned before immobilization to ensure successful healing without deformation and loss of function. The realignment of fractured bone ends is performed through a process called reduction. If the...