Related Experiment Video
Updated: Mar 16, 2026


Creating Radio-cephalic Arteriovenous Fistula in the Forearm with a Modified No-Touch Technique
Published on: April 1, 2022
Radial Artery as a Coronary Artery Bypass Conduit: 20-Year Results
Mario Gaudino1, Paolo Tondi2, Umberto Benedetto3
1Department of Cardiovascular Sciences, Catholic University, Rome, Italy; Department of Cardiothoracic Surgery, Weill Cornell Medical College, New York, New York.

Background:
There is a lack of evidence for the choice of the second conduit in coronary surgery. The radial artery (RA) is a possible option, but few data on very-long-term outcomes exist.
Objectives:
This study describes 20-year results of RA grafts used for coronary artery bypass grafting and the effects of RA removal on forearm circulation.
Methods:
We report the results of the prospective 20-year follow-up of the first 100 consecutive patients who received the RA as a coronary bypass conduit at our institution.
Results:
Follow-up was 100% complete. There were 64 deaths, 23 (35.9%) from cardiovascular causes. Kaplan-Meier 20-year survival was 31%. Of the 36 survivors, 33 (91.6%) underwent RA graft control at a mean of 19.0 ± 2.5 years after surgery. The RA was found to be patent in 24 cases (84.8% patency). In the overall population, probability of graft failure at 20 years was 19.0 ± 0.2% for the left internal thoracic artery (ITA), 25.0 ± 0.2% for the RA, and 55.0 ± 0.2% for the saphenous vein (p = 0.002 for RA vs. saphenous vein, 0.11 for RA vs. ITA, and p < 0.001 for ITA vs. saphenous vein). Target vessel stenosis >90%, but not location of distal anastomosis, significantly influenced long-term RA graft patency. No patients reported hand or forearm symptoms. The ulnar artery diameter was increased in the operated arm (2.44 ± 0.43 mm vs. 2.01 ± 0.47 mm; p < 0.05) and correlated with the peak systolic velocity of the second palmar digital artery (Pearson coefficient: 0.621; p < 0.05).
Conclusions:
The 20-year patency rate of RA grafts is good, and not inferior to the ITA, especially when the conduit is used to graft a vessel with >90% stenosis. RA harvesting does not lead to hand or forearm symptoms, even at a very-long-term follow-up.
More Related Videos
 13:10
Direct Re-implantation of Left Coronary Artery into the Aorta in Adults with Anomalous Origin of Left Coronary Artery from the Pulmonary Artery ALCAPA
Published on: April 24, 2017
 05:31
Transradial Access Chemoembolization for Hepatocellular Carcinoma Patients
Published on: September 20, 2020
Related Concept Videos
 01:12
Arteries of the Upper Limbs
 01:21
Coronary Circulation
Coronary circulation begins at the base of the aorta, where two main arteries arise—the left and right coronary arteries. These arteries encircle the heart in the coronary sulcus and supply the...
 01:11
Assessment of radial pulse
The radial pulse, located at the wrist, is often the preferred site for assessing peripheral pulse because of its accessibility and dependability. The process of determining the radial pulse involves several steps:
 01:25
Assessment of apical radial pulse
The A-R pulse assessment involves simultaneous evaluation of the apical and radial pulses. When the apical and radial pulse rates vary, this assessment helps identify a pulse deficit.
Pre-Procedural Preparation
 01:10
The Arch of Aorta
Encircling the heart, the coronary arteries form a ring-like structure before...
 01:17
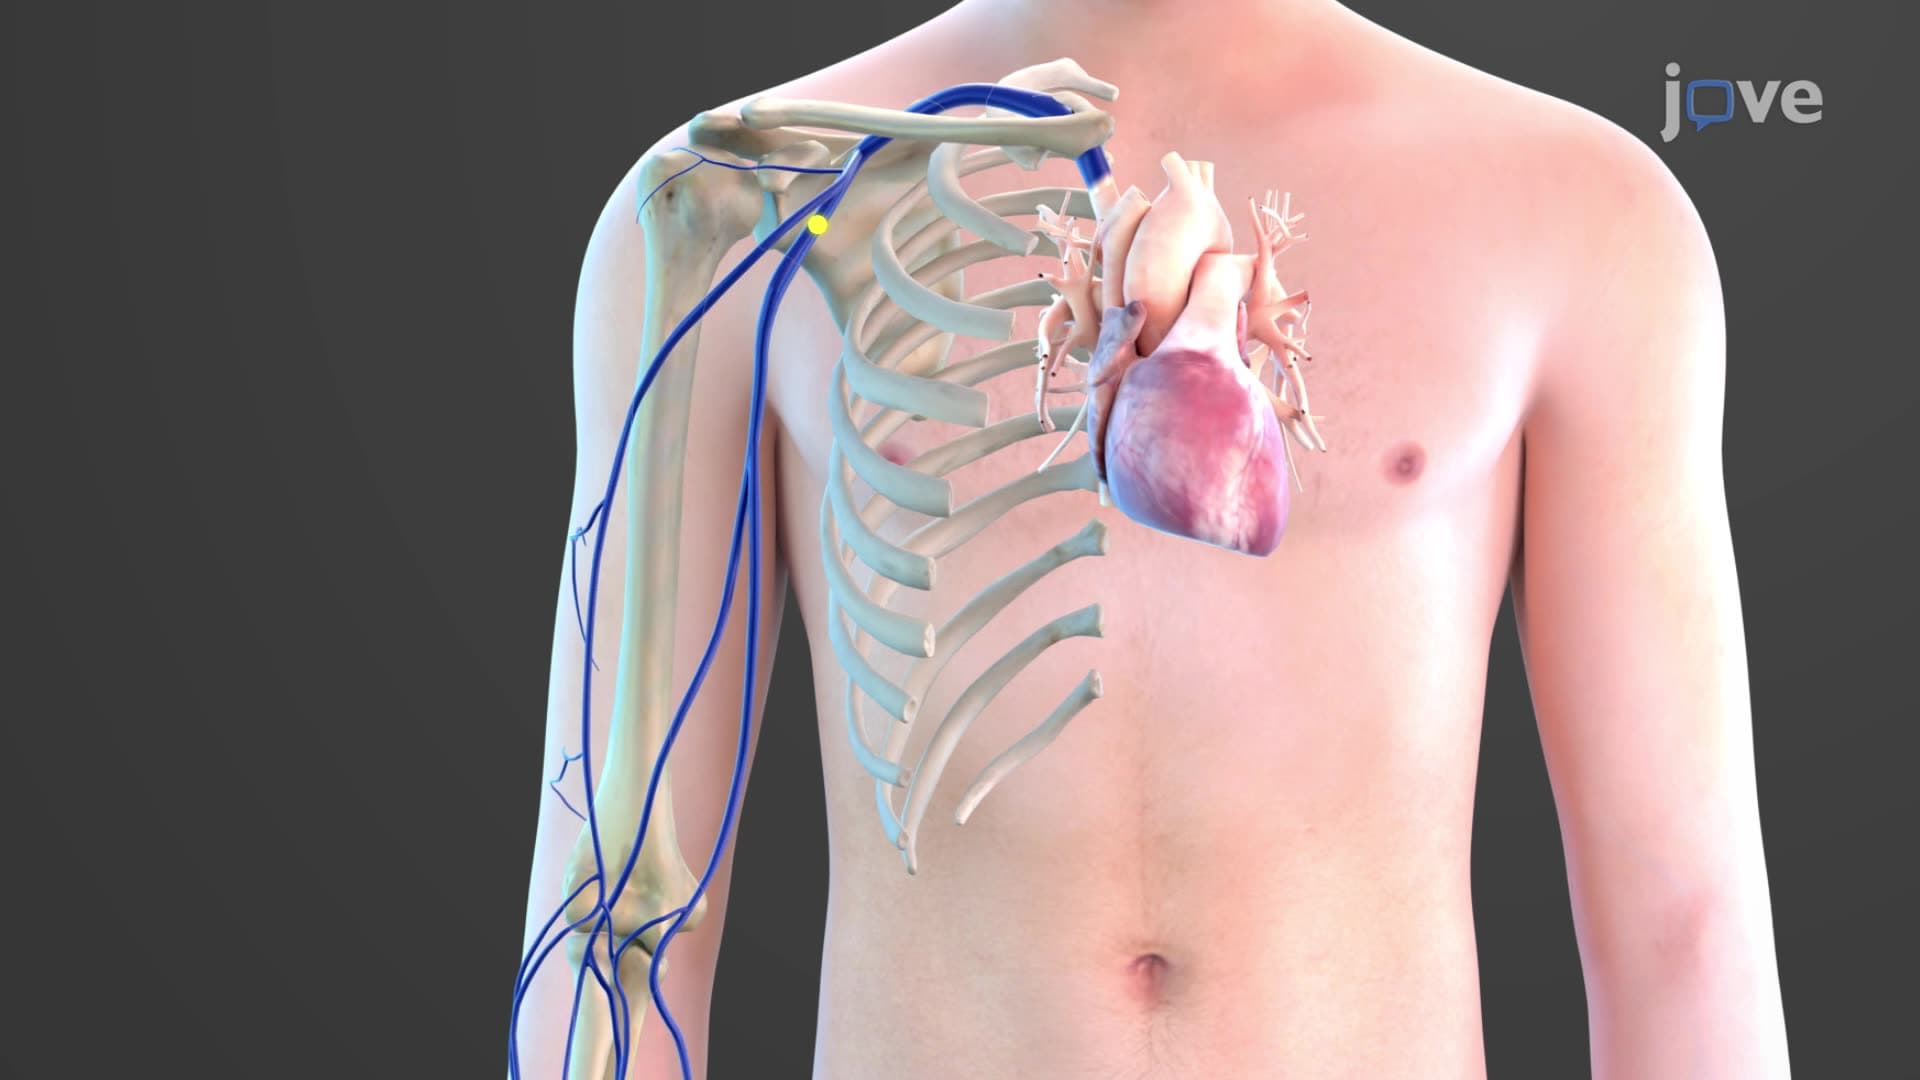
Veins of Upper Limbs
The deep venous system is primarily composed of the ulnar and radial veins. The ulnar vein, which drains the fingers through the superficial palmar venous arches, and the radial vein, which serves the palms via the deep palmar...