Related Experiment Video
Updated: Mar 16, 2026

Radiation Planning Assistant - A Streamlined, Fully Automated Radiotherapy Treatment Planning System
Published on: April 11, 2018
Making molehills out of a mountain: experience with a new scheduling strategy to diminish workload variations in
A Waters1, M Alizadeh2, C Filion2
1Université de Montréal, Montreal, QC;

Purpose:
A new scheduling strategy was implemented. Before implementation, treatments and planning computed tomography (ct) imaging were both scheduled at the same time. Maximal wait times for treatment are defined by the Quebec Ministry of Health's plan of action according to treatment aim and site. After implementation, patients requiring rapid treatment (priorities 0-3) continued to have their treatments scheduled at the same time as their planning ct; treatments for priority 4 (P4) patients were scheduled only after the treatment plan was approved. That approach aims to compensate for unexpected increases in planning workload by relocating less delay-sensitive cases to other time slots. We evaluated the impact on the patient experience, workload in various sectors, the care team's perception of care delivery, access to care, and the department's efficiency in terms of hours worked per treatment delivered.
Methods:
Three periods were defined for analysis: the pre-transitional phase, for baseline evaluation; the transitional phase, during which there was an overlap in the way patients were being scheduled; and the post-transitional phase. Wait times were calculated from the date that patients were ready to treat to the date of their first treatment. Surveys were distributed to pre- and post-transitional phase patients. Care team members were asked to complete a survey evaluating their perception of how the change affected workload and patient care. Operational data were analyzed.
Results:
We observed a 24% increase in the number of treatments delivered in the post-transitional phase. Before implementation, priority 0-3 patients waited a mean of 7.9 days to begin treatments (n = 241); afterward, they waited 6.3 days (n = 340, p = 0.006). Before implementation, P4 patients waited a mean 15.1 days (n = 233); after implementation, they waited 16.1 days (n = 368, p = 0.22). Surveys showed that patients felt that the time it took to inform them of treatment appointments was acceptable in both phases. No significant change in overtime hours occurred in dosimetry (p = 0.7476) or globally (p = 0.4285) despite the increased number of treatments. However, departmental efficiency improved by 16% (p = 0.0001).
Conclusions:
This new scheduling strategy for P4 cases resulted in improved access to care for priority 0-3 patients. Departmental efficiency was improved, and overtime hours did not increase. Patient satisfaction remained high.

Related Concept Videos
 01:28
Dosage Regimens: Designs and Approaches
 01:21
Drug Accumulation During Multiple Dosing: Repetitive IV Injections
 01:25
Determination of Multiple Dosing Parameters: Loading and Maintenance Doses
 01:15
Chronopharmacokinetics: Circadian Rhythms and Influence on Drug Response
The time of drug administration is an important factor to consider, as it can influence the toxic dose of a drug. For example, a study conducted by Prins et al. in 1997 examined the effects of the timing of...
 01:24
Rational Dosage Regimen: Maintenance Dose and Loading Dose
In most cases, drugs are administered repetitively or infused continuously to maintain a steady-state concentration in the body. At a steady...
 01:01
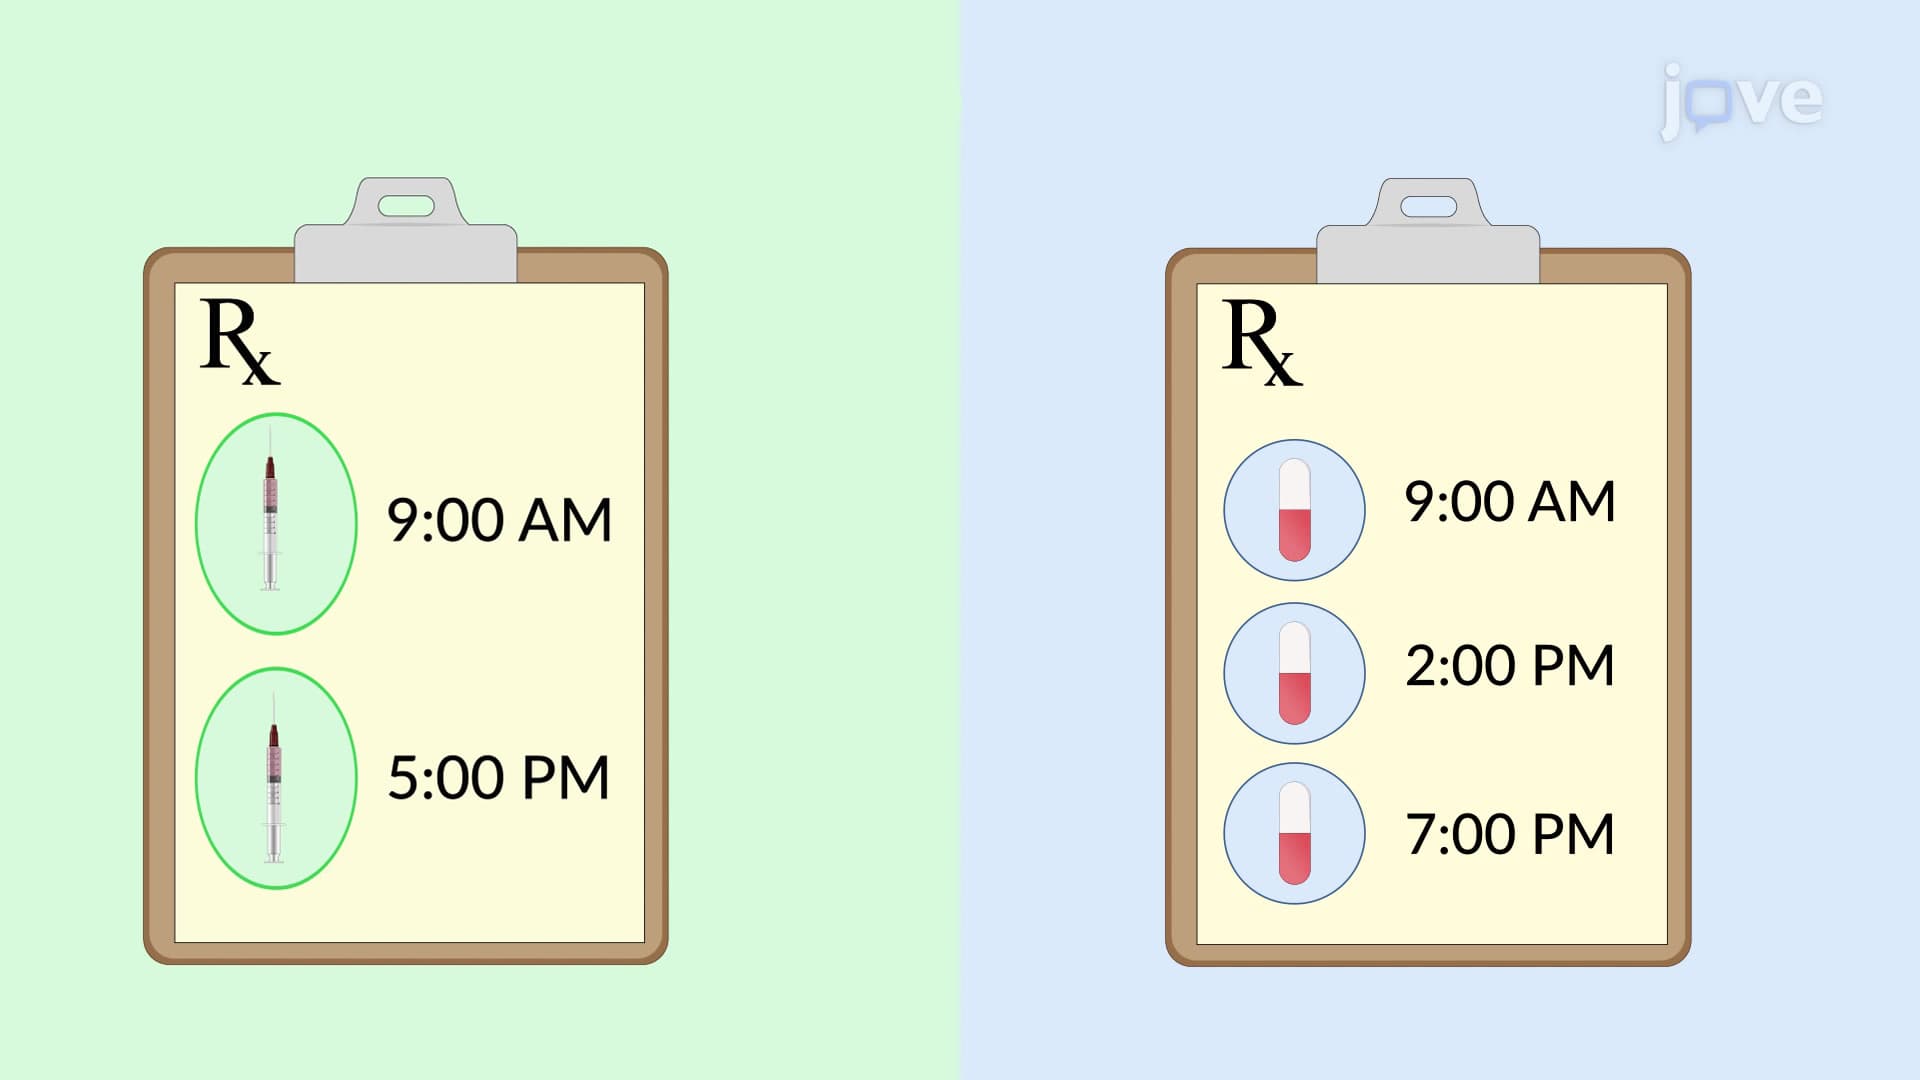
Dosage Regimen: Fixed Dose
Fixed-dose regimens can be used for various routes of administration, including intravenous (IV) injections and oral medications. For IV administration, a predetermined amount of the drug is...