Related Experiment Video
Updated: Mar 16, 2026
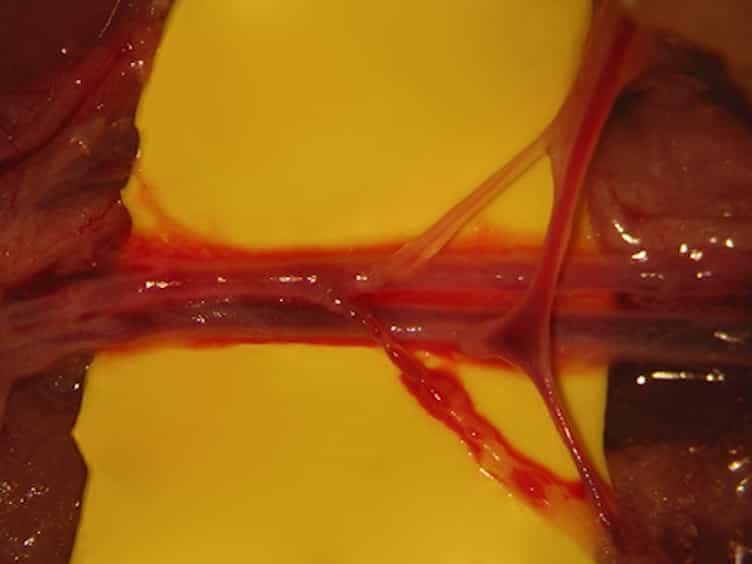

A Model of Free Tissue Transfer: The Rat Epigastric Free Flap
Published on: January 15, 2017
Predictors of Intraoperative Blood Transfusion in Free Tissue Transfer
Jonas Kolbenschlag1, Johanna Schneider2, Kamran Harati2
1Department of Plastic, Reconstructive and Esthetic Surgery, Handsurgery, Martin-Luther-Hospital, Berlin, Germany.

Background Free tissue transfer has become a safe and reliable procedure and is routinely used in a variety of settings. However, it is associated with lengthy operating times and a high potential for blood loss and consecutive red blood cell transfusions (RBCTs). Methods To assess the risk for RBCTs, we retrospectively identified 398 patients undergoing free tissue transfer between 2005 and 2014. Based on a multivariate model of risk factors and their respective odds ratio, a risk score was developed to predict the likelihood of the need for intraoperative RBCT. Results The median age at the time of operation was 51.3 ± 15 years, and 278 (70%) patients were male. The average body mass index was 25.9 ± 4 and the median ASA score was 2 (range: 1-4). Mean duration of surgery was 319.8 ± 108 minutes and mean duration of hospital stay was 45.8 ± 40 days. A total of 231 patients (58%) required perioperative RBCTs, all of which were allogenic. RBCTs were performed 0 to 48 hours preoperatively in 36 patients (11.3%), intraoperatively in 166 patients (41.7%), and 0 to 48 hours postoperatively in 125 patients (31.4%). The mean amount of overall RBCTs given was 2.5 ± 3.7 units and 1.1 ± 1.9 units for intraoperative transfusions. The following risk factors were statistically significant in the multivariate regression analysis and included in the risk score: age >60 years; a preoperative hemoglobin concentration of <11 g/dL; a preoperative platelet count of >400/nL; history of renal (RI) and cardial insufficiency (CI); defect localization on the proximal extremities, head and neck, or trunk; and the use of myocutaneous flaps. This score assessed the risk for RBCTs with a sensitivity of 77%, a specificity of 81%, and an AUC of the ROC curve of 0.86. Conclusion We were able to develop a risk score that allows for the assessment of RBCT likelihood. While most of the identified risk factors cannot be prevented or corrected, it still allows for improved patient counseling and can potentially reduce the number of ordered but not transfused RBCTs.
Background Free tissue transfer has become a safe and reliable procedure and is routinely used in a variety of settings. However, it is associated with lengthy operating times and a high potential for blood loss and consecutive red blood cell transfusions (RBCTs). Methods To assess the risk for RBCTs, we retrospectively identified 398 patients undergoing free tissue transfer between 2005 and 2014. Based on a multivariate model of risk factors and their respective odds ratio, a risk score was developed to predict the likelihood of the need for intraoperative RBCT. Results The median age at the time of operation was 51.3 ± 15 years, and 278 (70%) patients were male. The average body mass index was 25.9 ± 4 and the median ASA score was 2 (range: 1-4). Mean duration of surgery was 319.8 ± 108 minutes and mean duration of hospital stay was 45.8 ± 40 days. A total of 231 patients (58%) required perioperative RBCTs, all of which were allogenic. RBCTs were performed 0 to 48 hours preoperatively in 36 patients (11.3%), intraoperatively in 166 patients (41.7%), and 0 to 48 hours postoperatively in 125 patients (31.4%). The mean amount of overall RBCTs given was 2.5 ± 3.7 units and 1.1 ± 1.9 units for intraoperative transfusions. The following risk factors were statistically significant in the multivariate regression analysis and included in the risk score: age >60 years; a preoperative hemoglobin concentration of <11 g/dL; a preoperative platelet count of >400/nL; history of renal (RI) and cardial insufficiency (CI); defect localization on the proximal extremities, head and neck, or trunk; and the use of myocutaneous flaps. This score assessed the risk for RBCTs with a sensitivity of 77%, a specificity of 81%, and an AUC of the ROC curve of 0.86. Conclusion We were able to develop a risk score that allows for the assessment of RBCT likelihood. While most of the identified risk factors cannot be prevented or corrected, it still allows for improved patient counseling and can potentially reduce the number of ordered but not transfused RBCTs.
More Related Videos
Related Concept Videos
 01:15
Blood Transfusion
Blood Transfusion Overview
A blood transfusion is a medical procedure used to replace blood lost due to injury, surgery, or to treat conditions such as anemia or cancer. During a transfusion, donor blood is...
 02:45
Blood Transfusion and Agglutination
History
The history of blood transfusion dates back to the 17th century, when early attempts were made in animals. In 1818 James Blundell, a British doctor, performed the first successful human blood transfusion. Later in 1900, Karl...
 01:26
Kidney Transplant II: Surgical Procedure
 01:24
Tissue Transplantation
The Biology of Tissue Transplantation
The biology of tissue transplantation hinges on the Major Histocompatibility Complex (MHC) molecules. These molecules...
 01:28
Kidney Transplant I: Introduction