Primary ventriculoperitoneal shunting outcomes: a multicentre clinical audit for shunt infection and its risk factors
Related Experiment Video
Updated: Mar 15, 2026
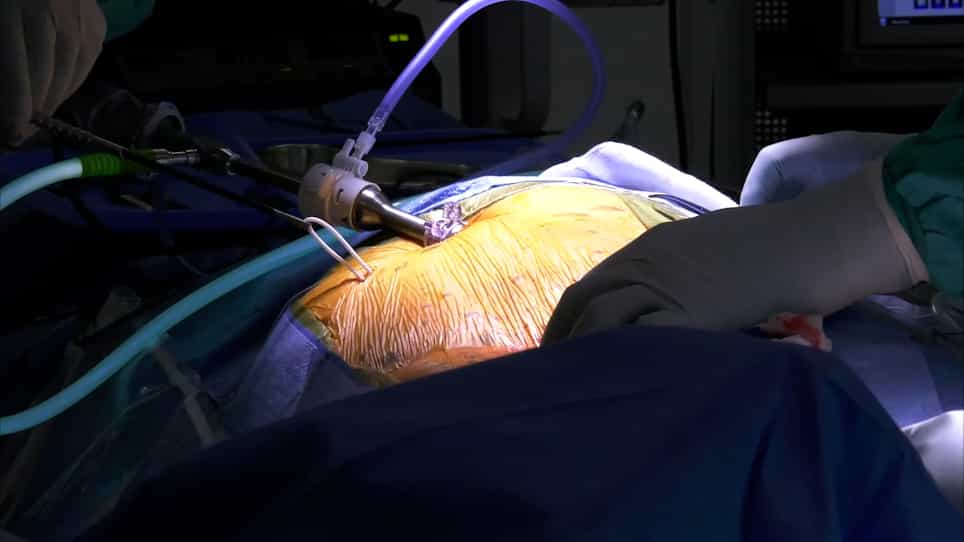
Neuronavigation and Laparoscopy Guided Ventriculoperitoneal Shunt Insertion for the Treatment of Hydrocephalus
Published on: October 14, 2022

Objectives:
To determine the frequency of primary ventriculoperitoneal shunt infection among patients treated at neurosurgical centres of the Hospital Authority and to identify underlying risk factors.
Methods:
This multicentre historical cohort study included consecutive patients who underwent primary ventriculoperitoneal shunting at a Hospital Authority neurosurgery centre from 1 January 2009 to 31 December 2011. The primary endpoint was shunt infection, defined as: (1) the presence of cerebrospinal fluid or shunt hardware culture that yielded the pathogenic micro-organism with associated compatible symptoms and signs of central nervous system infection or shunt malfunction; or (2) surgical incision site infection requiring shunt reinsertion (even in the absence of positive culture); or (3) intraperitoneal pseudocyst formation (even in the absence of positive culture). Secondary endpoints were shunt malfunction, defined as unsatisfactory cerebrospinal fluid drainage that required shunt reinsertion, and 30-day mortality.
Results:
A primary ventriculoperitoneal shunt was inserted in 538 patients during the study period. The mean age of patients was 48 years (range, 13-88 years) with a male-to-female ratio of 1:1. Aneurysmal subarachnoid haemorrhage was the most common aetiology (n=169, 31%) followed by intracranial tumour (n=164, 30%), central nervous system infection (n=42, 8%), and traumatic brain injury (n=27, 5%). The mean operating time was 75 (standard deviation, 29) minutes. Shunt reinsertion and infection rates were 16% (n=87) and 7% (n=36), respectively. The most common cause for shunt reinsertion was malfunction followed by shunt infection. Independent predictors for shunt infection were: traumatic brain injury (adjusted odds ratio=6.2; 95% confidence interval, 2.3-16.8), emergency shunting (2.3; 1.0-5.1), and prophylactic vancomycin as the sole antibiotic (3.4; 1.1-11.0). The 30-day all-cause mortality was 6% and none were directly procedure-related.
Conclusions:
This is the first Hong Kong territory-wide review of infection in primary ventriculoperitoneal shunts. Although the ventriculoperitoneal shunt infection rate met international standards, there are areas of improvement such as vancomycin administration and the avoidance of scheduling the procedure as an emergency.
Related Concept Videos
 01:26
Factors Affecting the Risk of Infection
The integrity and count of the white blood cells help the body resist pathogens and fight infection. When impaired, it reduces the body's resistance to pathogens. The acidic pH levels of the gastrointestinal, genitourinary tracts, and skin...
 01:22
Healthcare Associated Infections II: Preventive Measures
The best practices for preventing healthcare-associated infections include hand hygiene, patient risk...
 01:26
Healthcare Associated Infections I: Iatrogenic, Exogenic and Endogenic
HAIs significantly increase the cost of health care. Extended stays in healthcare institutions, increased disability, increased costs of medications, including specialized antibiotics, and prolonged recovery times add to the patient's expenses and the healthcare institution and funding bodies.
 01:29
Endocarditis IV: Nursing Management
 01:30
Urinary Tract Infection III: Diagnostic Studies and Interprofessional Care
 01:25
Endocarditis I: Introduction