Related Experiment Video
Updated: Mar 15, 2026
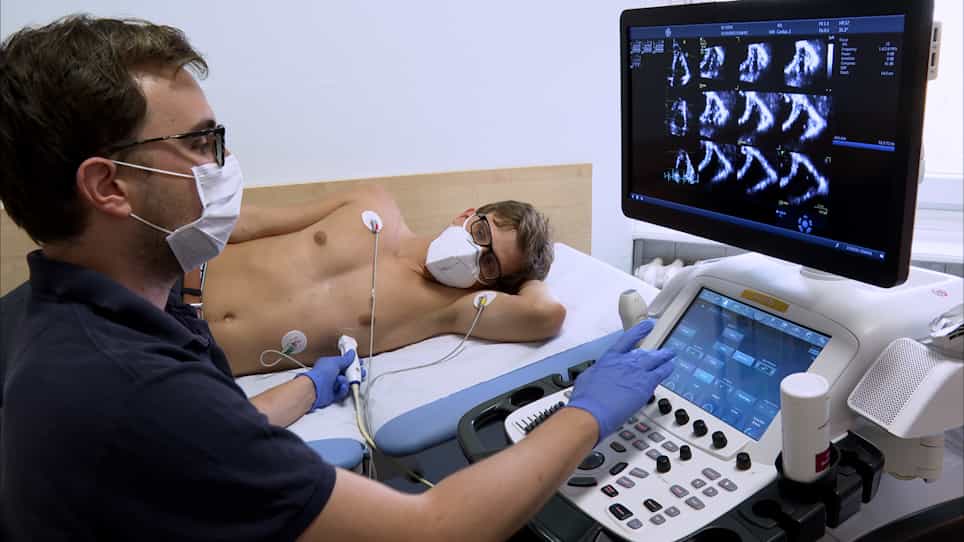

Morphological and Functional Assessment of the Right Ventricle Using 3D Echocardiography
Published on: October 28, 2020
Double-Outlet Right Ventricle With Noncommitted Ventricular Septal Defect and 2 Adequate Ventricles: Is Anatomical
Olivier Villemain1, Damien Bonnet1, Lucile Houyel2
1Pediatric and Congenital Cardiology and Cardiac Surgery, M3C-Necker Enfants Malades, Université Paris Descartes, Sorbonne Paris Cité, Paris, France.

Abstract:
The management of double-outlet right ventricle associated with anatomically noncommitted ventricular septal defect constitutes a surgical challenge. The limits for, and the specific outcomes after anatomical vs univentricular repair still remain to be established. Between 1993 and 2011, 36 consecutive patients presenting with double-outlet right ventricle or noncommitted ventricular septal defect (21 inlet, 10 muscular, and 5 central perimembranous) and 2 adequately sized ventricles underwent surgical repair at 2 centers. Right ventricular outflow tract obstruction was present in 18 of 36 patients (50%). A total of 21 patients had undergone previous palliative procedures. Anatomical repair (group I) by means of intraventricular baffle construction was performed in 24 (associated right ventricular outflow tract reconstruction in 12 and arterial switch in 5) at a median age of 10.5 months. Ventricular septal defect was surgically enlarged in 12 (50%) patients. The remaining 12 patients underwent univentricular repair (group II). There were 4 hospital deaths (11%), all in group I (P = 0.30 vs group II). A total of 8 of 20 patients in group I survivors underwent 13 reoperations after a median delay of 24 months: subaortic stenosis was the main cause for reoperation in 6 of 8 patients. There was 1 late death in group I and 2 late deaths in group II. The median follow-up was 5.6 years (95% CI: 0.2-9.8). The 10- year actuarial survival rate and freedom from reoperation were 74.7 ± 5% and 58 ± 5% in group I and 71 ± 7% and 70 ± 7% in group II, respectively. At the last visit, all survivors were in New York Heart Association class I-II. Univariate analysis showed that atrioventricular septal defect and isolated mitral cleft were associated with death (P = 0.04) and need for reoperation (P = 0.038). In conclusion, anatomical repair, associated with substantial rates of mortality and need for reoperation, should be considered with caution. Associated atrioventricular septal defect and isolated mitral cleft were the only risk factors for mortality and reoperation.


