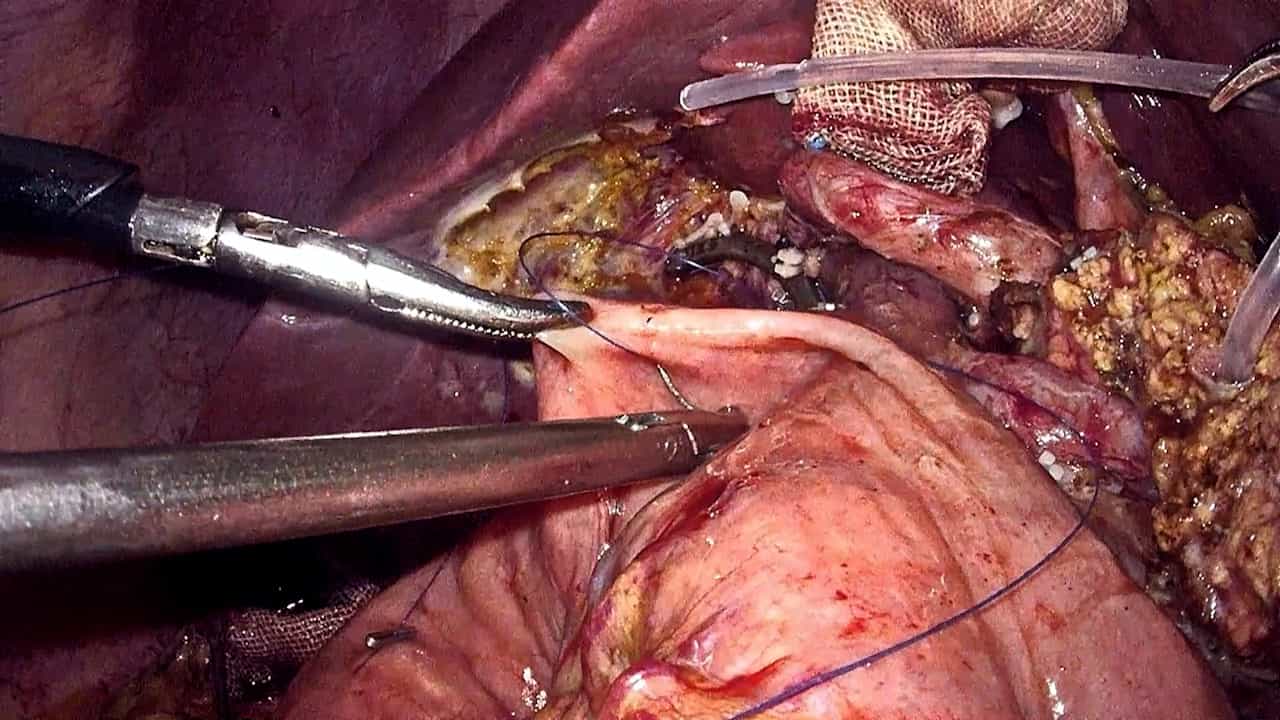
Mucous fistula refeeding decreases parenteral nutrition exposure in postsurgical premature neonates
Colin D Gause1, Madoka Hayashi2, Courtney Haney3
1Department of Pediatric Surgery, Johns Hopkins University School of Medicine, Baltimore, MD, United States.

Insights
Mucous fistula refeeding in premature neonates with bowel resection significantly reduces parenteral nutrition (PN) dependence and accelerates enteral feeding. This practice safely improves nutritional outcomes for neonates requiring ostomies.
Area of Science:
- Neonatal surgery
- Surgical nutrition
- Parenteral nutrition
Background:
- Premature neonates undergoing bowel resection and enterostomy often require parenteral nutrition (PN).
- PN can lead to cholestasis, a common complication in neonates.
- Mucous fistula refeeding offers a method to restore gastrointestinal continuity.
Purpose of the Study:
- To evaluate the impact of mucous fistula refeeding on nutritional intake in neonates.
- To assess the effect of refeeding on parenteral nutrition (PN) dependence.
- To determine the safety and efficacy of refeeding in preventing PN-associated hepatotoxicity.
Main Methods:
- Retrospective review of neonates who had bowel resection and enterostomy over two years.
- Comparison of patients who underwent mucous fistula refeeding (RF) versus those with only an ostomy (OST).
- Primary outcomes: time to goal enteral feeds and PN discontinuation; Secondary outcomes: PN-associated hepatotoxicity.
Main Results:
- Refeeding (RF) patients achieved goal enteral feeds significantly earlier than ostomy (OST) patients (median 28 vs. 43 days, p=0.03) and were weaned from PN sooner (median 25 vs. 41 days, p=0.04) during the interoperative period.
- Post-anastomosis, RF patients reached goal enteral feeds faster (median 7.5 vs. 20 days, p≤0.001) and were weaned from PN sooner (median 30.5 vs. 48 days, p=0.001).
- No significant differences in critical illness markers were observed between RF and OST groups.
Conclusions:
- Mucous fistula refeeding in neonates with ostomies leads to earlier achievement of enteral feeding goals and faster discontinuation of PN.
- Refeeding appears to be a safe and beneficial practice for improving nutritional outcomes in this patient population.
- Further prospective multicenter trials are warranted to confirm benefits and assess potential side effects in a broader patient cohort.
Background/Purpose:
Premature neonates can develop intraabdominal conditions requiring emergent bowel resection and enterostomy. Parenteral nutrition (PN) is often required, but results in cholestasis. Mucous fistula refeeding allows for functional restoration of continuity. We sought to determine the effect of refeeding on nutrition intake, PN dependence, and PN associated hepatotoxicity while evaluating the safety of this practice.
Methods:
A retrospective review of neonates who underwent bowel resection and small bowel enterostomy with or without mucous fistula over 2years was undertaken. Patients who underwent mucous fistula refeeding (RF) were compared to those who did not (OST). Primary outcomes included days from surgery to discontinuation of PN and goal enteral feeds, and total days on PN. Secondary outcomes were related to PN hepatotoxicity.
Results:
Thirteen RF and eleven OST were identified. There were no significant differences among markers of critical illness (p>0.20). In the interoperative period, RF patients reached goal enteral feeds earlier than OST patients (median 28 versus 43days; p=0.03) and were able to have PN discontinued earlier (median 25 versus 41days; p=0.04). Following anastomosis, the magnitude of effect was more pronounced, with RF patients reaching goal enteral feeds earlier than OST patients (median 7.5 versus 20days; p≤0.001) and having PN discontinued sooner (30.5 versus 48days; p=0.001).
Conclusions:
RF neonates reached goal feeds and were able to be weaned from PN sooner than OST patients. A prospective multicenter trial of refeeding is needed to define the benefits and potential side effects of refeeding in a larger patient population in varied care environments.

Related Concept Videos
 01:15
Enteral Nutrition II: Nasointestinal and Gastrostomy Feeding
Nasointestinal Feeding
Nasointestinal feeding involves placing a tube...
 01:26
Enteral Nutrition I: Orogastric and Nasogastric Feeding
Orogastric (OG) and nasogastric (NG) feeding are two standard methods used for enteral nutrition. Enteral nutrition is often preferred over...
 01:25
Peptic Ulcer Disease V: Surgical Management and Nursing Care
Surgical Interventions for Peptic Ulcer Disease
 01:27
Parentral Nutrition: Centeral and Peripheral Parental Nutrition
PN can be administered through two primary routes:
1. Central Parenteral Nutrition (CPN):
CPN involves delivering a high concentration of nutrients through a large vein. This is typically achieved using a Peripherally Inserted Central Catheter (PICC) or,...
 01:21
Inflammatory Bowel Disease V: Surgical Management
Here are some common surgical interventions for IBD:
 01:29
Suctioning the Nasopharyngeal Airway
Equipment Required